13.6. Approach
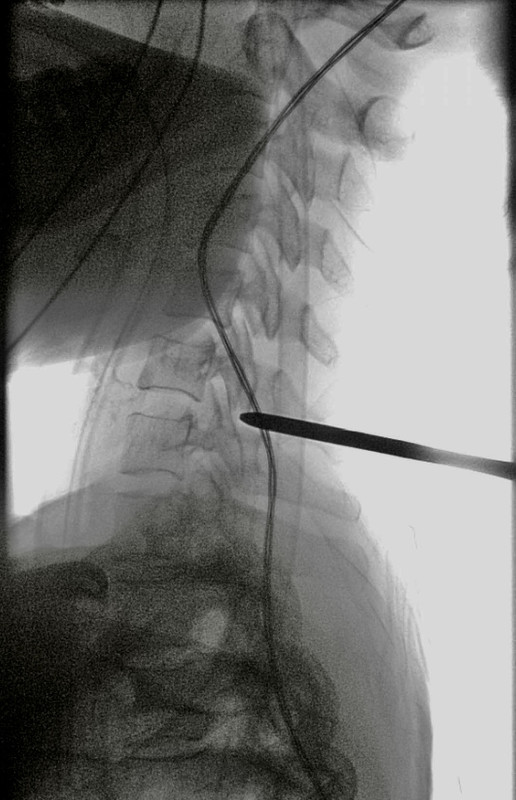
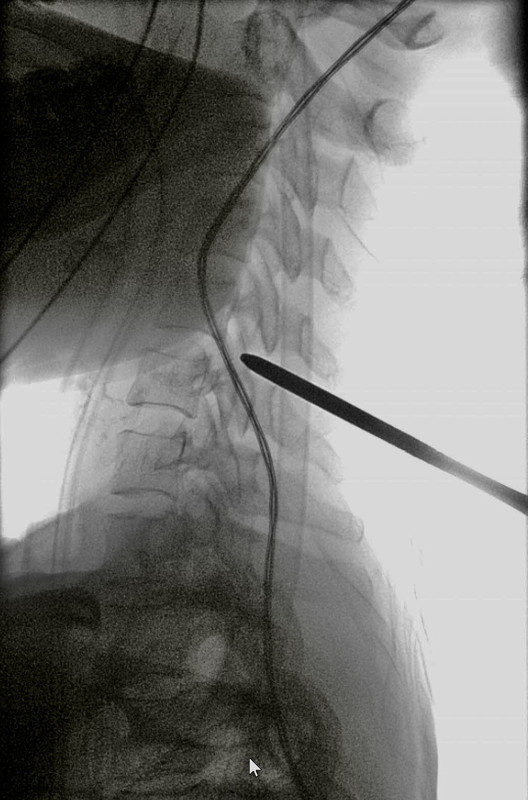
@ProfFishchenkoUsing the preoperative markings, we create the endoscopic and working portals. Through the endoscopic portal, we insert the first sequential dilator and check its position under C-arm guidance.
If a discrepancy from the planned level is detected, we stop, clarify the numbering, and adjust the direction of access cranially or caudally, with repeat radiological confirmation. Adjacent cervical levels are close together, so, when the anatomy permits, the direction can be changed through the existing incisions.
We insert the second dilator. By touch, we identify the posterior vertebral elements: the cranial and caudal laminae, base of the spinous process, and inferior articular process of the cranial vertebra. We replace the dilators with a trocar and recheck the bony landmarks. If there is any doubt about position, we obtain additional radiological imaging.
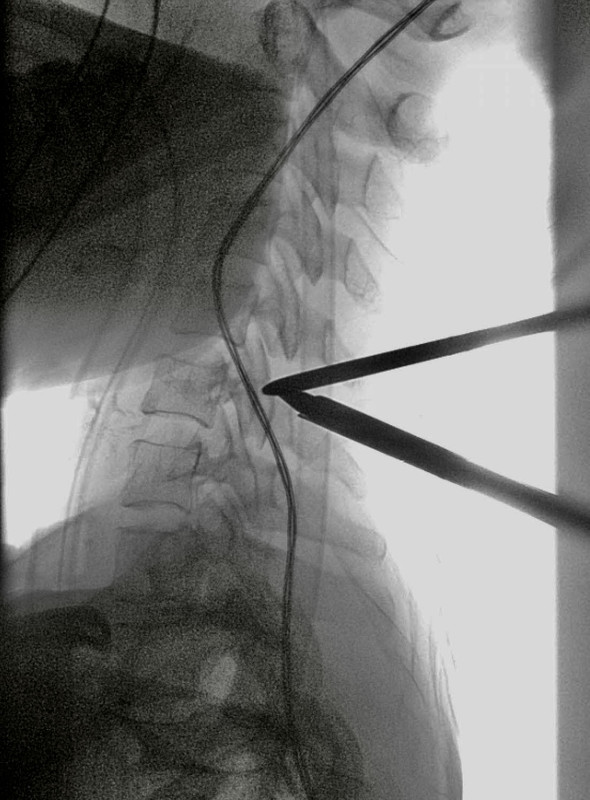
Through the working portal, we sequentially insert 2–3 dilators and establish triangulation with the trocar until “metal-to-metal” contact is felt. Under C-arm guidance, we confirm triangulation and the corresponding interlaminar level.
The short distance between cervical interlaminar spaces creates a risk of unnoticed displacement to an adjacent level. At the initial stage and after changing instrument direction, we therefore repeat radiological verification as needed.
For irrigation, we set the saline bag height to provide adequate flow without excessive pressure. We continuously maintain free outflow; we do not compensate for impaired outflow by raising the bags or increasing pressure.
⚠️ WARNING: Excessive saline pressure may cause excess fluid to enter the epidural space, with adverse consequences for the brain and optic nerves.
We replace the working portal dilators with a 5 mm RF electrode. Its working part must be clearly visible under endoscopic visualization. The main bony landmark is the vertebral lamina: we confirm its position by touch and sight.
We create the working space superficial to the ligamentum flavum, along the laminar surface, under endoscopic visualization. We do not advance instruments blindly or use force to enter beneath the ligamentum flavum. If landmarks are not visible, we stop manipulation and restore the view.
References
1. Jung SB, Kim N. Biportal endoscopic spine surgery for cervical disk herniation: a technical notes and preliminary report. Medicine (Baltimore). 2022;101(27):e29751. DOI: 10.1097/MD.0000000000029751.
2. Heo DH. Biportal endoscopic posterior cervical foraminotomy with discectomy for unilateral radicular arm pain due to cervical herniated disc. Neurosurg Focus Video. 2024;10(2):V12. DOI: 10.3171/2024.1.FOCVID23225.
3. Heo DH, Ha JS, Jang JW. Biportal endoscopic posterior cervical foraminotomy for adjacent 2-level foraminal lesions using a single approach (sliding technique). Neurospine. 2023;20(1):92–98. DOI: 10.14245/ns.2346144.072.
Previous section: 13.5. Radiological guidance
Next section: Endoscopic stage