13.7. Endoscopic stage
@ProfFishchenkoWe then use the electrode in coblation mode to expose the cranial and caudal laminae and the inferior articular process. After identifying the bony landmarks, we remove excess soft tissue over the ligamentum flavum with a shaver (Tomcat, Aggressive Plus) or the electrode in coblation mode under continuous endoscopic visualization. We clearly visualize the base of the spinous process, lamina, and inferior articular process of the cranial vertebra, as well as the lamina and base of the spinous process of the caudal vertebra.
We achieve hemostasis outside the spinal canal with a 5 mm RF electrode. After removal of the ligamentum flavum, we use only a 1.5 mm RF electrode.
At this stage, we clearly visualize the V-point — the anatomical zone formed by the cranial and caudal laminae and the medial edge of the articular process.
The position of the V-point within the operative field depends on the degree of neck flexion. This should be taken into account when correlating the preliminary marking with the bony landmarks after final patient positioning [4].
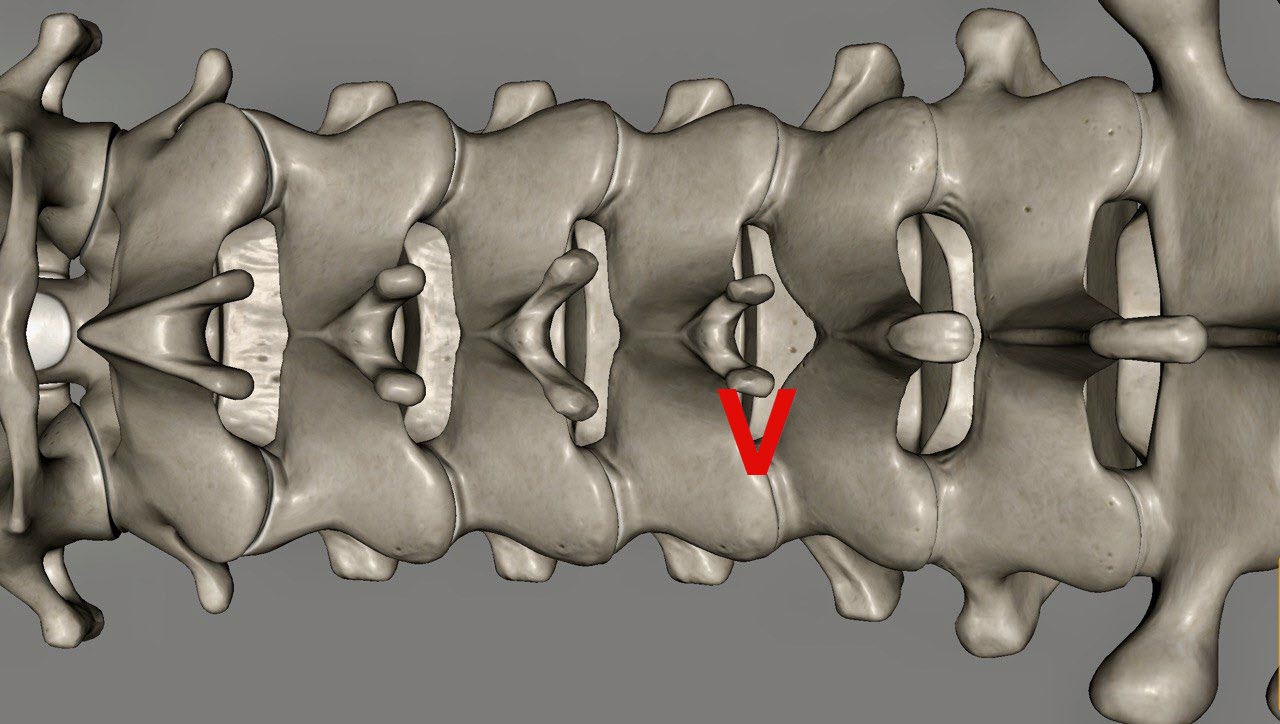
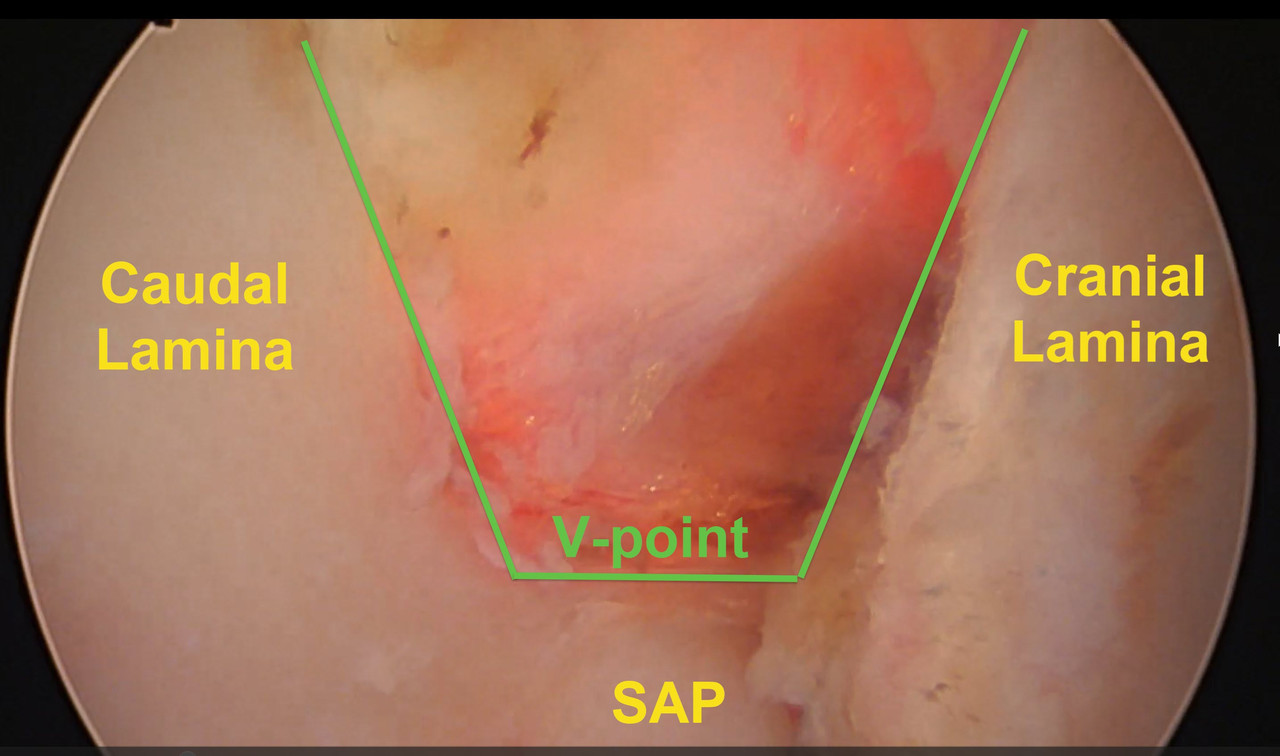
After clearly visualizing the bony landmarks, we obtain a fluoroscopic check to confirm the level. The C-arm can then be moved away; it must remain available if repeat imaging is needed.
Bone resection
The extent of bone resection for cervical intervertebral disc herniation removal is usually small — up to the attachments of the ligamentum flavum to the cranial and caudal laminae.
We perform bone resection with a 3 mm cutting burr. We begin with the lamina and inferior articular process of the cranial vertebra. We remove the outer cortical and cancellous layers of the lamina; at this stage, we preserve the inner cortical layer adjacent to the ligamentum flavum and spinal canal structures. We resect 5–6 mm of the medial portion of the inferior articular process. We clearly visualize the medial edge of the superior articular process of the caudal vertebra. We resect the outer cortical and cancellous layers of the cranial and caudal laminae over a length of 4–5 mm.
We perform further bone resection to the cranial and caudal attachments of the ligamentum flavum using 2 mm Kerrison punches. After identifying the cranial and caudal edges of the ligamentum flavum, we resect the medial portion of the superior articular process of the caudal vertebra. Resection of 4–5 mm is usually sufficient.
We begin removal of the ligamentum flavum at its caudal or cranial edge. Under endoscopic visualization, we carefully place the Kerrison punches beneath the ligament and remove it in stages.
Work within the spinal canal
In the cervical spine, beneath the ligamentum flavum is a membrane containing vessels and covering the dura mater. We create an opening in the membrane with a Caspar vascular hook, then remove it with 2 mm Kerrison punches.
After removal of the ligamentum flavum and hemostasis, the course of small superficial vessels running along the cervical nerve root may provide an additional visual cue for its identification. This feature is assessed together with the position of the medial pedicle border [4].
We manipulate the nerve root with particular care in the cervical spine.
⚠️ WARNING: Forceful nerve root retraction may cause persistent neuropathy.
We mobilize the nerve root by gently separating it from the pedicle with an elevator. After nerve root mobilization, we remove the herniation from beneath it with a Caspar vascular hook.
After herniation removal, we inspect the operative cavity and achieve final hemostasis.
We do not place a drain in the cervical spine.
We place one interrupted Vicryl 2-0 suture in each skin incision.
References
1. Heo DH. Biportal endoscopic posterior cervical foraminotomy with discectomy for unilateral radicular arm pain due to cervical herniated disc. Neurosurgical Focus: Video. 2024;10(2):V12.
2. Kim JY, et al. Anatomical importance between neural structure and bony landmark: clinical importance for posterior endoscopic cervical foraminotomy. Neurospine. 2021;18(1):139–146.
3. Kang MS, et al. Percutaneous full-endoscopic versus biportal endoscopic posterior cervical foraminotomy for unilateral cervical foraminal disc disease. Clinics in Orthopedic Surgery. 2022;14(4):539–547.
4. Song K.-S.D., Sun S.D., Kim D.H. Cervical Posterior: Foraminotomy and Discectomy. In: Unilateral Biportal Endoscopic Spine Surgery: Basic and Advanced Technique. Springer; 2022. P. 187–200; relevant passages: pp. 192, 199. Link to the book chapter.
Previous section: 13.6. Approach