4.6. Features of the L4–L5 level
@ProfFishchenkoPlanning the left-sided approach
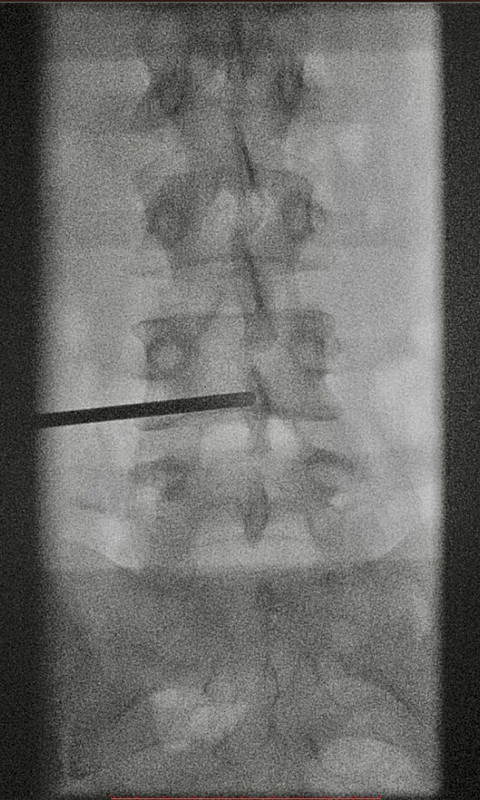
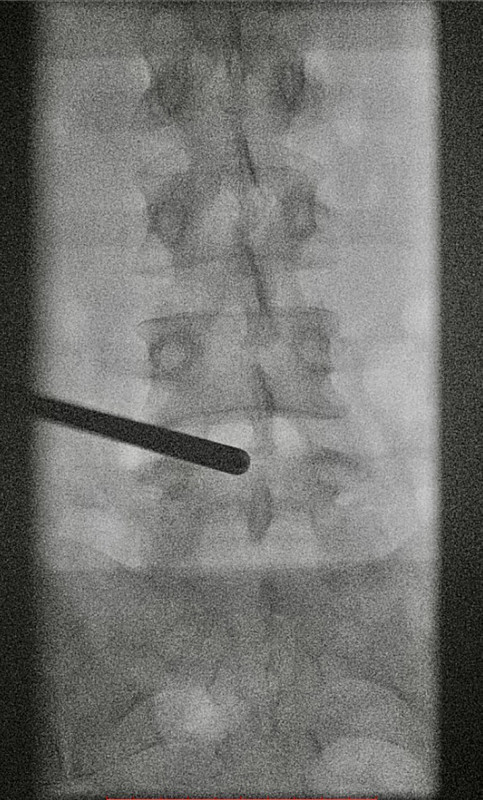
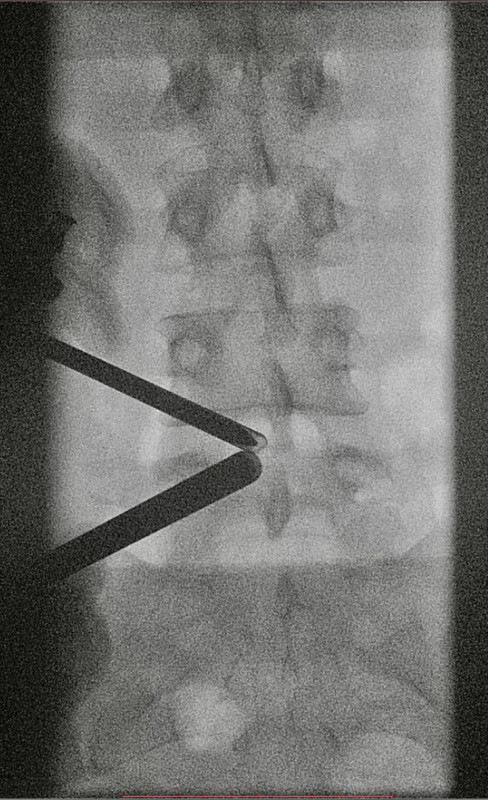
Figures 1–3 show the sequence of orientation and portal creation for a left-sided approach to the L4–L5 disc under C-arm guidance.
Anatomical features and extent of resection
The L4–L5 intervertebral disc lies slightly cranial to the corresponding interlaminar space. In most cases, I therefore perform additional bone resection of the lamina of the cranial L4 vertebra.
I determine the extent of resection according to the anatomy, herniation location, and need for adequate decompression while preserving the segment’s supporting structures as much as possible.
Layer-by-layer laminar resection
In my practice, I use a 5 mm cutting burr. I begin resection at the junction of the base of the spinous process and the L4 lamina and continue toward its inferior articular process (IAP). Resection of approximately 5–6 mm is usually sufficient.
I do not remove the full thickness of a thick lamina at once. I first thin the superficial layer — typically by approximately 3–5 mm — and then the middle layer, continuously monitoring the remaining bone thickness and anatomical landmarks.
I may remove the deep layer with 3 mm, 45° Kerrison punches, gently displacing the ligamentum flavum with the lower jaw under direct endoscopic visualization. Depending on the resection zone, working space, and proficiency with the technique, I also use a burr or osteotome. With each instrument, I maintain visual control and protection of neural structures. If visibility is lost, I stop resection until visualization is restored.
For L4–L5 disc herniation removal, it is usually unnecessary to reach the cranial attachment of the ligamentum flavum to the lamina.
Resection of the articular processes and ligamentum flavum
After cranial laminar resection, I move laterally to the L4 IAP. I perform limited resection, approximately 3–4 mm, to visualize the medial edge of the L5 superior articular process (SAP) from its tip to its base.
With 3 mm, 45° Kerrison punches, I perform a small resection of the SAP base — approximately 3 mm. With reverse 90° Kerrison punches or an osteotome, I perform limited resection of the distal lamina to the attachment of the ligamentum flavum.
After visualizing and mobilizing the distal edge of the ligamentum flavum, I enter the spinal canal. Limited resection of the lateral portion of the ligament adjacent to the SAP is usually sufficient for disc herniation removal.
Protection of the L5 nerve root
The L5 nerve root may lie directly beneath the ligamentum flavum. If needed, I perform additional SAP resection laterally to visualize the lateral edge of the nerve root, or carefully position the elevator lateral to it under direct endoscopic visualization.
I gently mobilize the nerve root only to the extent needed for safe access to the herniated fragment. Before removal, I clearly identify the herniation.
I perform the subsequent stages using the technique described in §4.5, “L5–S1 level”.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral biportal endoscopy for lumbar spinal stenosis and lumbar disc herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. doi:10.2106/JBJS.ST.22.00020.
2. Kim SK, Kang SS, Hong YH, Park SW, Lee SC. Clinical comparison of unilateral biportal endoscopic technique versus open microdiscectomy for single-level lumbar discectomy: a multicenter, retrospective analysis. J Orthop Surg Res. 2018;13(1):22. doi:10.1186/s13018-018-0725-1.
3. Soliman HM. Irrigation endoscopic discectomy: a novel percutaneous approach for lumbar disc prolapse. Eur Spine J. 2013;22(5):1037–1044. doi:10.1007/s00586-013-2701-0.
Previous section: 4.5. L5–S1 level
Next section: 4.7. Features of the L3–L4, L2–L3, and L1–L2 levels