4.5. L5–S1 level
@ProfFishchenkoBone resection and removal of the ligamentum flavum
To access the spinal canal and remove a disc herniation at L5–S1, I usually perform a small bone resection — approximately 3 mm — of the L5 inferior articular process (IAP), starting at the junction of the lamina and IAP. I determine the extent of resection according to the anatomy and the need to safely visualize the neural structures and herniated fragment while preserving supporting structures.
After resection of the IAP, I visualize the medial portion of the S1 superior articular process (SAP). Using 3 mm, 45° Kerrison punches, I perform a small resection of the SAP base; with reverse 90° Kerrison punches, I resect the distal part of the lamina to the attachment of the ligamentum flavum. If the lamina is thick, I first thin it with a burr. Instruments are used under direct endoscopic visualization.
After visualizing and mobilizing the distal edge of the ligamentum flavum, I enter the spinal canal. Limited resection of the lateral portion of the ligament adjacent to the SAP is usually sufficient for disc herniation removal.
Identification and mobilization of the S1 nerve root
The S1 nerve root may lie directly beneath the ligamentum flavum. If needed, I perform additional SAP resection laterally to visualize the lateral edge of the nerve root, or carefully position the elevator lateral to it under direct endoscopic visualization.
As a result of inflammation, the nerve root may be adherent to the disc or posterior longitudinal ligament. I gently mobilize the nerve root and dural sac, resting the elevator on the posterior surface of the vertebral body or disc. I perform adhesiolysis only to the extent needed for safe mobilization of neural structures and access to the herniated fragment. Before removal, I clearly identify the herniation.
Intracanal hemostasis
I maintain continuous irrigation and free fluid outflow. If bleeding impairs visibility, I perform targeted coagulation. I use a 1.5 mm RF electrode for intracanal vessels.
In my practice, I use the BONSS ARS600 generator with a disposable RF electrode. I do not activate ABLATE mode near the dura mater or nerve root; I perform coagulation at COAG 2. This is a setting level on the ARS600 scale, not a power value in watts.
I activate the electrode only under direct endoscopic visualization with continuous irrigation and free outflow. I orient the back of the electrode toward neural structures. I use a separate inactive instrument to protect and gently retract the nerve root. The activated RF electrode must contact only the tissue to be coagulated.
Nerve root retraction and herniation removal
If needed, I place a nerve root retractor under direct endoscopic visualization, held by the scrub nurse. Lumbar nerve roots are vulnerable to traction injury. I use the minimum necessary force for the minimum necessary time, release retraction periodically, and maintain direct visualization of neural structures throughout.
I avoid working in the axillary zone between the traversing nerve root and dural sac while retracting the nerve root laterally. Overstretching in this zone may cause postoperative paresthesias. I prefer gentle medial retraction of the nerve root together with the dural sac using an elevator or retractor.
If herniated material — an extrusion or sequestered fragment — has entered the spinal canal, I visualize it and remove it with a discotome. When the annulus fibrosus remains intact and access to the herniated material is needed, I perform annulotomy with an endoscopic annulotomy knife (Indian knife).
A scalpel or sharp probe may injure the nerve root and its sheaths, so I use them with particular care under direct visualization. If an annulotomy knife is unavailable, I create an opening with an elevator. If needed, I enlarge it with 3 mm, 45° Kerrison punches, then remove the herniated material using appropriately sized discotomes.
Disc curettage
For a free sequestered fragment that has lost continuity with the disc, with no visible annular defect, I remove the fragment without additional annulotomy.
After removing the herniated fragment, I determine the need for and extent of intradiscal exploration from the intraoperative findings. I use a shaver to remove remaining loose fragments within the disc.
Suction through the shaver’s working window may capture adjacent tissues and injure the nerve root or dural structures. I monitor the position of the working window and insertion depth even after the blade has entered the disc, preventing contact with neural structures.
Disc irrigation
Some surgeons use dedicated cannulas to irrigate the disc with pressurized saline to wash out loose nucleus pulposus fragments. The cannula is inserted into the disc cavity, connected to a 20–50 ml syringe via a Luer-Lock connection, and used to irrigate the disc, washing out loose fragments.

Coagulation of the edges of the annular defect
In my practice, after removal of the herniated fragment and, if needed, curettage and irrigation, I may treat the edges of the annular defect with an RF electrode with a 5 mm tip in coagulation mode. I use the BONSS ARS600 settings and the principles of neural protection described above. I avoid contact with neural structures and unnecessary thermal exposure.
Wound drainage
Before completing surgery, I recheck hemostasis with a reduced hydrostatic tamponade effect from irrigation. A drain does not replace meticulous hemostasis.
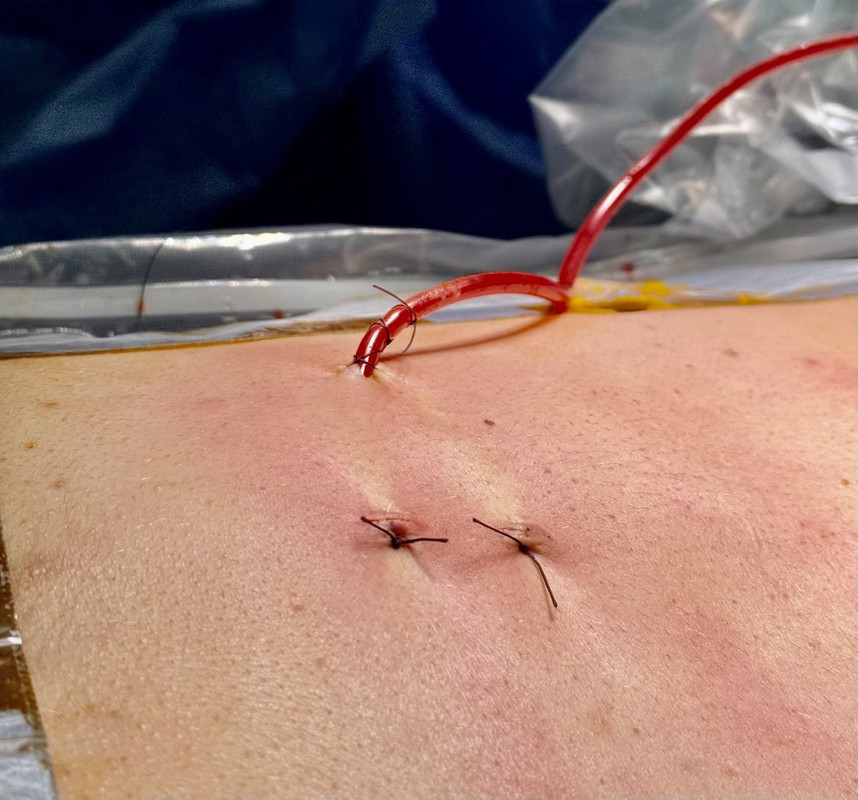
After lumbar BESS/UBE decompression and discectomy, I place a No. 15 drainage tube in my practice. I position it in the created operative cavity and bring it out through the working portal or a separate counterincision. I secure it to the skin with Vicryl 2-0 and connect it to a drainage system with a 300 or 500 ml reservoir.
I remove the drain the next day. If there are signs of drain-related irritation of neural structures, I remove it immediately. Irritation may result not only from contact between the tube and neural structures, but also from the negative pressure generated by the drainage system.
If pain is new or increasing, I assess the neurological status. Increasing pain, weakness, or bladder and bowel dysfunction require urgent exclusion of a compressive hematoma. Drain removal does not replace this assessment or the necessary treatment.
Wound closure
I place an interrupted Vicryl 2-0 skin suture at each portal. I do not routinely place subcutaneous sutures.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral biportal endoscopy for lumbar spinal stenosis and lumbar disc herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. doi:10.2106/JBJS.ST.22.00020.
2. Kim SK, Kang SS, Hong YH, Park SW, Lee SC. Clinical comparison of unilateral biportal endoscopic technique versus open microdiscectomy for single-level lumbar discectomy: a multicenter, retrospective analysis. J Orthop Surg Res. 2018;13(1):22. doi:10.1186/s13018-018-0725-1.
3. Soliman HM. Irrigation endoscopic discectomy: a novel percutaneous approach for lumbar disc prolapse. Eur Spine J. 2013;22(5):1037–1044. doi:10.1007/s00586-013-2701-0.
4. Choi CM. Biportal endoscopic spine surgery (BESS): considering merits and pitfalls. J Spine Surg. 2020;6(2):457–465. doi:10.21037/jss.2019.09.29.
5. Ahn DK, Lee JS, Shin WS, Kim S, Jung J. Postoperative spinal epidural hematoma in a biportal endoscopic spine surgery. Medicine (Baltimore). 2021;100(6):e24685. doi:10.1097/MD.0000000000024685.
Previous section: 4.4. Bone resection
Next section: 4.6. Features of the L4–L5 level