2.2. Planning
@ProfFishchenkoPrevious section: 2.1. Operating Room Layout
Patient positioning and blood pressure
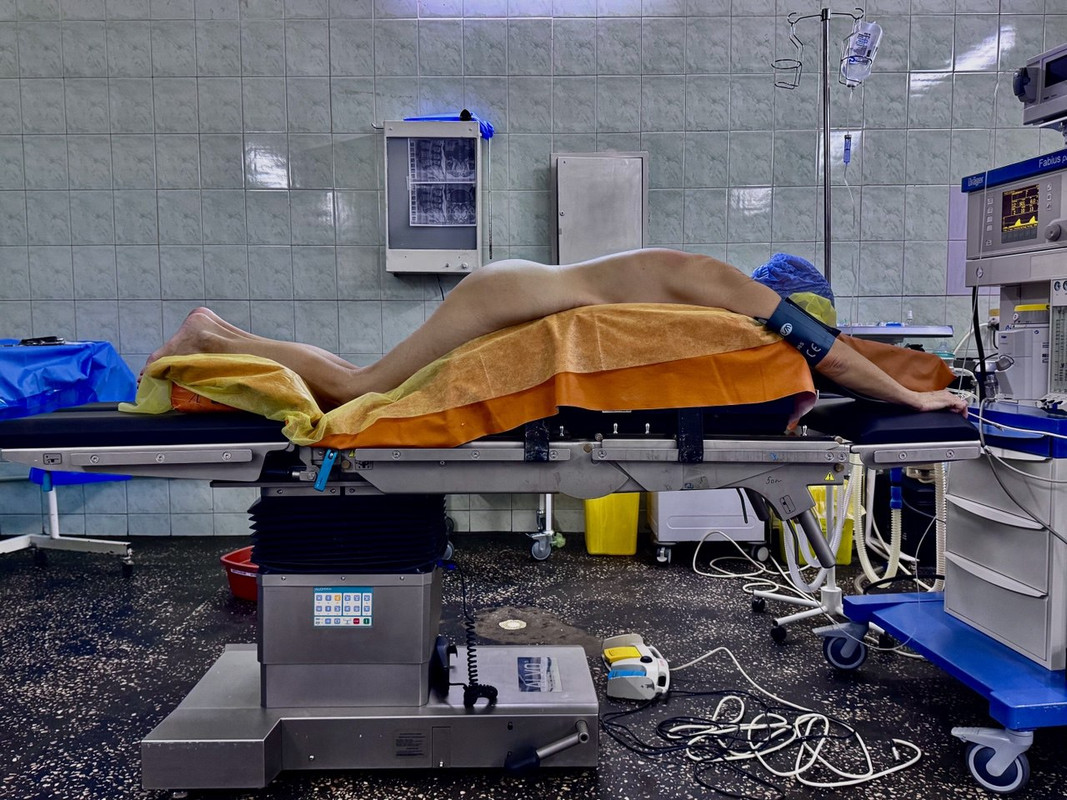
The patient is positioned prone on a radiolucent operating table. I use a Wilson frame to achieve sufficient flexion of the operative segment and widen the interlaminar space (Fig. 1). I position the chest and pelvis on supports so that the abdomen remains free from compression. I keep the head and neck in a neutral position, avoiding pressure on the eyes and maintaining access to the airway. I coordinate head and trunk positioning with the anesthesiologist, taking ventilation and venous drainage into account. After positioning, I recheck the arm position and protection of pressure points. I place soft supports under the knees and lower legs.
The anesthesiologist determines the target blood pressure based on baseline pressure, comorbidities, and organ perfusion. In my practice, a systolic pressure of approximately 100 mmHg may be acceptable depending on these factors.
Level confirmation and portal planning
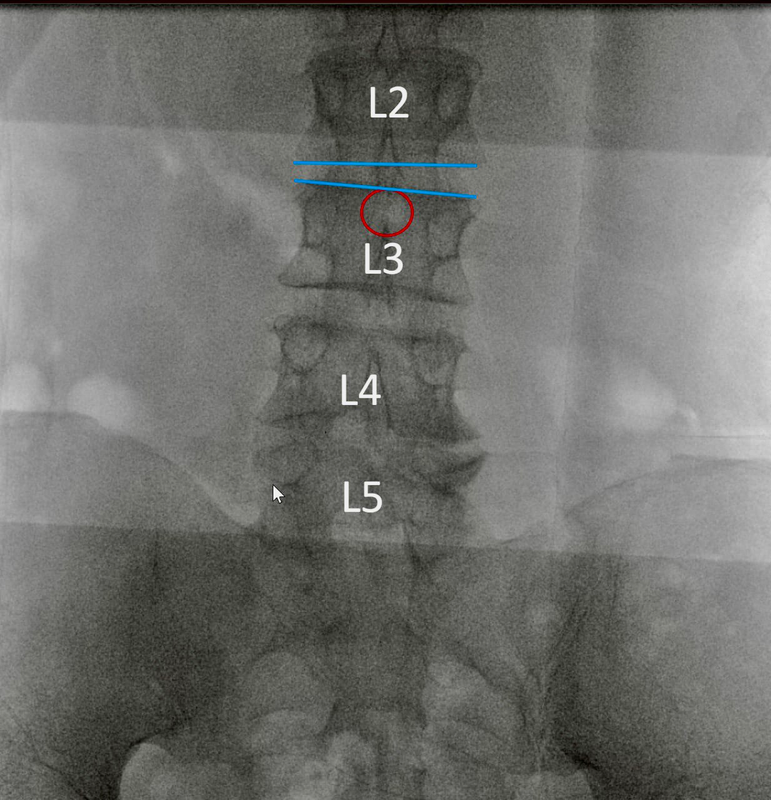
I correlate the operative level and side with the preoperative images. Before creating the portals, I confirm the level using the C-arm in the anteroposterior projection. I obtain lateral images when the level or instrument depth is uncertain, particularly in the presence of lumbarization, sacralization, or hyperlordosis. I do not restrict lateral imaging to the placement of the trocar and dilators.
I use the distances below during planning. I refine portal placement according to the patient's anatomy, target depth, and fluoroscopic findings. I hold the endoscope in my left hand.
Left-sided interlaminar approach
The fluoroscopic landmark is the interlaminar space at the relevant level. I mark the intervertebral disc level on the skin. I plan the cranial (endoscopic) portal immediately lateral to the spinous process at the level of the inferior edge of the cranial lamina. I place the caudal (working) portal approximately 2 cm caudally in patients with a slender or average build and 3–4 cm caudally in overweight patients, refining the distance according to anatomy and target depth. A diagram of the approach is shown in Fig. 3.
I anticipate the possibility of conversion before starting surgery, particularly while learning the technique. Longitudinal incisions facilitate extension of the approach, but conversion is not limited to simply connecting the skin incisions: the extent of exposure and the equipment required depend on the situation.
I prefer longitudinal skin incisions 7–10 mm in length.
I use the interlaminar space as the landmark when planning the approach. In the upper lumbar spine, it may lie substantially caudal to the corresponding intervertebral disc (Fig. 2).

Right-sided interlaminar approach
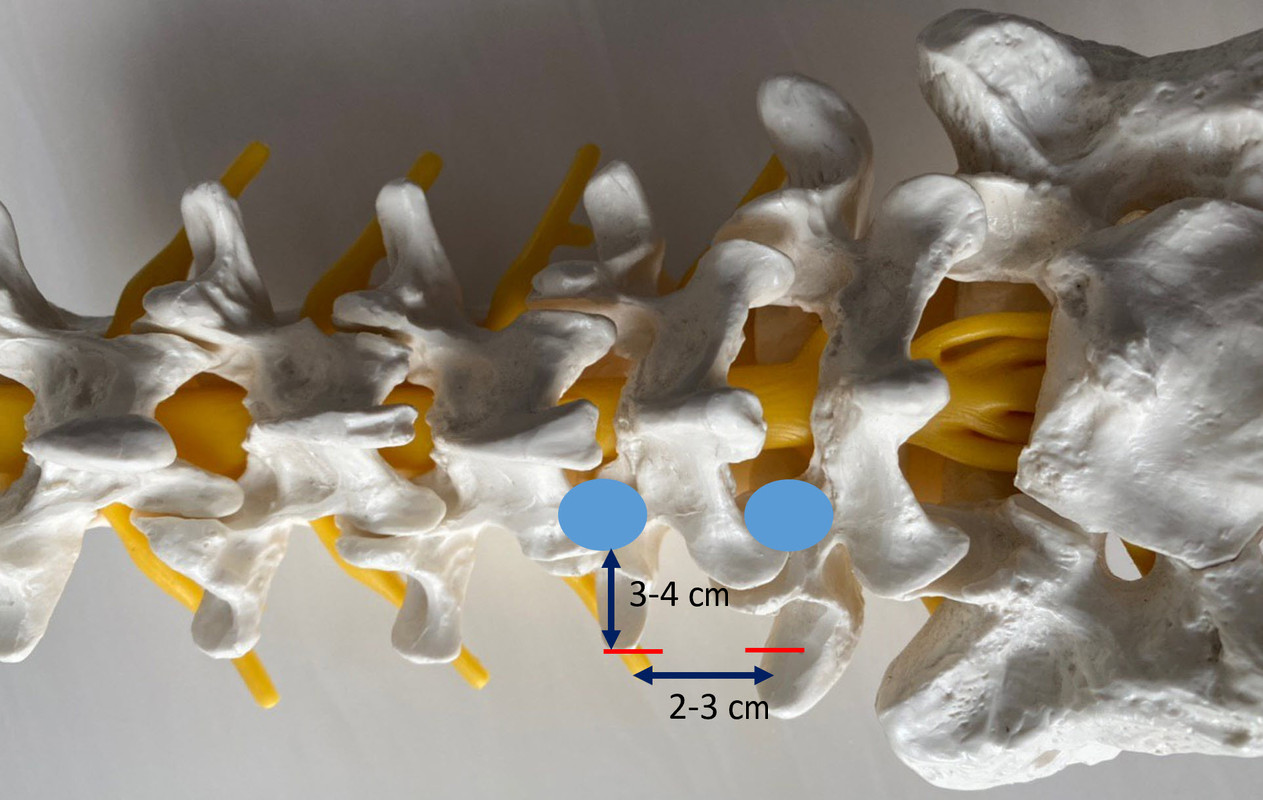
The fluoroscopic landmark is the interlaminar space at the relevant level. I mark the intervertebral disc level on the skin. I plan the caudal (endoscopic) portal immediately lateral to the spinous process at the level of the superior edge of the caudal lamina. I place the cranial (working) portal approximately 2 cm cranially in patients with a slender or average build and 3–4 cm cranially in overweight patients, refining the distance according to anatomy and target depth.
Posterolateral (paraspinal) approach
The fluoroscopic landmarks are the transverse processes of the adjacent vertebrae at the operative level. I mark the projections of the pedicles on the skin and draw a line along their lateral borders—the lateral pedicular line. From this line, I move approximately 3–5 cm laterally: 3–4 cm in patients with a slender build and 4–5 cm in overweight patients. I refine these distances according to individual anatomy and target depth. I plan the cranial portal at the level of the transverse process of the upper vertebra and the caudal portal at the level of the transverse process of the lower vertebra (Fig. 4).
I use the term “transforaminal” only when the working trajectory actually passes through the intervertebral foramen; it is not synonymous with every posterolateral approach.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral Biportal Endoscopy for Lumbar Spinal Stenosis and Lumbar Disc Herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. DOI: 10.2106/JBJS.ST.22.00020.
2. Zhang Q, Wei Y, Wen L, Tan C, Li X, Li B. An overview of lumbar anatomy with an emphasis on unilateral biportal endoscopic techniques: A review. Medicine (Baltimore). 2022;101(48):e31809. DOI: 10.1097/MD.0000000000031809.
3. Choi CM, Chung JT, Lee SJ, Choi DJ. How I do it? Biportal endoscopic spinal surgery (BESS) for treatment of lumbar spinal stenosis. Acta Neurochir (Wien). 2016;158(3):459–463. DOI: 10.1007/s00701-015-2670-7.
4. Saugel B, Fletcher N, Gan TJ, Grocott MPW, Myles PS, Sessler DI; POQI XI Workgroup. PeriOperative Quality Initiative (POQI) international consensus statement on perioperative arterial pressure management. Br J Anaesth. 2024;133(2):264–276. DOI: 10.1016/j.bja.2024.04.046.
5. Practice Advisory for Perioperative Visual Loss Associated with Spine Surgery 2019: An Updated Report by the American Society of Anesthesiologists Task Force on Perioperative Visual Loss, the North American Neuro-Ophthalmology Society, and the Society for Neuroscience in Anesthesiology and Critical Care. Anesthesiology. 2019;130(1):12–30. DOI: 10.1097/ALN.0000000000002503.
Previous section: 2.1. Operating Room Layout