2.1. Operating Room Layout
@ProfFishchenkoPrevious section: 1.10. Epidural anatomy in the endoscopic field
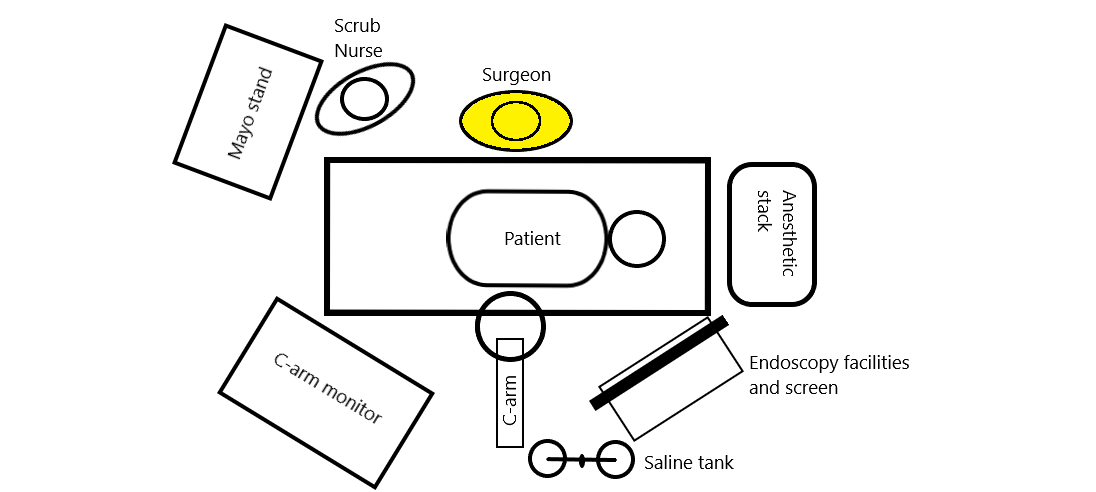
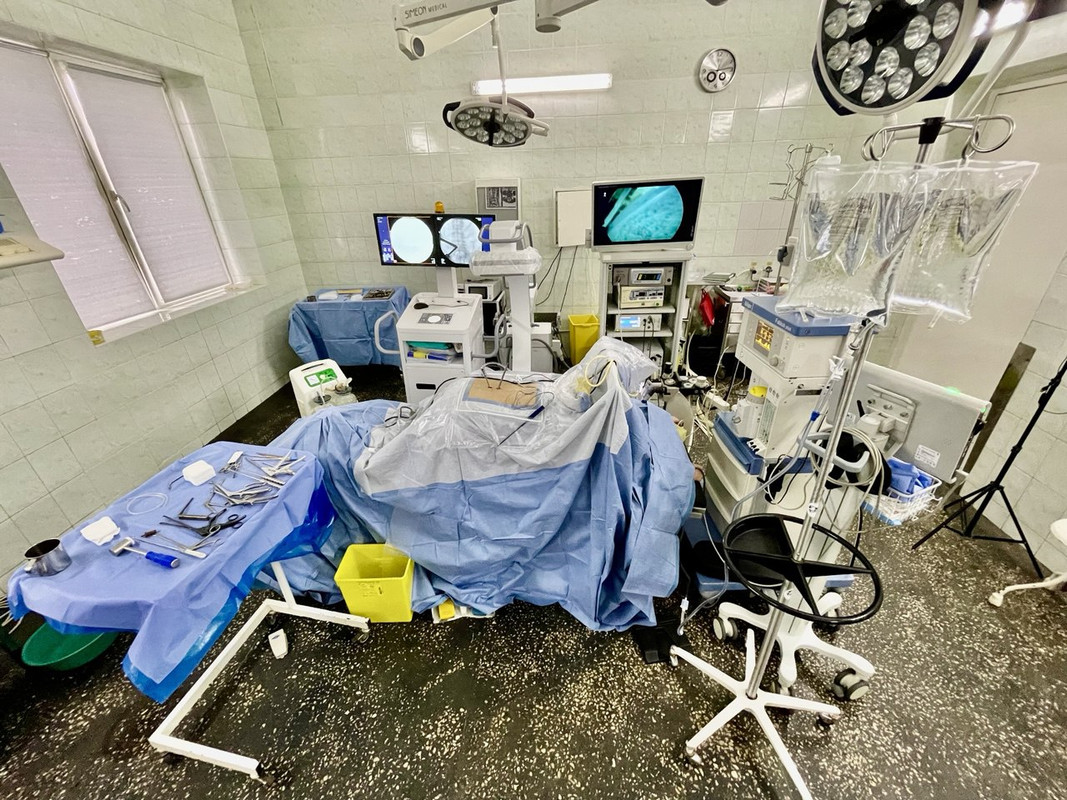
The operating room layout should provide a clear view of the monitors, unrestricted movement of the endoscope and instruments, and access to the patient for the C-arm and anesthesia team. Examples of equipment arrangements for left-sided and right-sided BESS/UBE approaches are shown below.
Left-sided approach
For a left-sided approach, the arrangement of equipment and personnel is shown in Fig. 1. I position the endoscopic monitor opposite me at a comfortable viewing height, leaving sufficient space for C-arm movement and access to the patient for the anesthesia team.
Right-sided approach
For a right-sided approach, I adapt the equipment arrangement while maintaining a comfortable line of sight to the monitors, freedom of manipulation, and access to the patient (Fig. 2).
Operating team workflow
In my practice, I perform BESS/UBE procedures without a dedicated surgical assistant. During certain maneuvers, the scrub nurse uses the surgical mallet or holds the nerve root retractor.
Height of the operative field and surgeon positioning
The operating table height should be adjusted to the surgeon's height and the level of the operative field. An excessively high field forces the surgeon to keep the shoulders elevated, increasing strain on the shoulder joints and causing rapid fatigue during prolonged manipulation. After positioning the patient, the surgeon should check that the endoscope and instruments can be used without having to raise the shoulders. If necessary, the table height is adjusted or a stable platform is provided for the surgeon [4].
Radiation protection during C-arm use
Before acquiring an X-ray image, the hands are moved out of the primary beam. For the anteroposterior view, the X-ray tube is positioned beneath the operating table. For the lateral view, the surgeon and other staff should stand on the detector side. During exposure, the distance from the patient is increased and a mobile protective screen is used whenever possible [5].
Images are acquired with brief exposures. The last-image-hold function is used for repeat viewing without further irradiation. Pulsed and low-dose modes are used when they provide adequate visualization of the anatomical landmarks [5].
Checks before starting surgery
• The endoscopic and fluoroscopic monitors are clearly visible without having to twist the torso.
• The path of the C-arm and access to the patient for the anesthesia team are unobstructed.
• The connections and function of the endoscopic equipment, burr system, RF generator, and foot pedals have been checked.
• For irrigation, I use gravity-fed saline without a pump; I check the inflow and the availability of free outflow.
• Cables, tubing, and foot pedals are positioned so that they do not obstruct work or staff movement; collection of irrigation fluid has been arranged.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral biportal endoscopy for lumbar spinal stenosis and lumbar disc herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. https://doi.org/10.2106/JBJS.ST.22.00020
2. Choi CM, Chung JT, Lee SJ, Choi DJ. How I do it? Biportal endoscopic spinal surgery (BESS) for treatment of lumbar spinal stenosis. Acta Neurochir (Wien). 2016;158(3):459–463. https://doi.org/10.1007/s00701-015-2670-7
3. Choi CM. Biportal endoscopic spine surgery (BESS): considering merits and pitfalls. J Spine Surg. 2020;6(2):457–465. https://doi.org/10.21037/jss.2019.09.29
4. Lee N., Heo D.H., Park C.K. Biportal Endoscopic Approach (Biportal Endoscopic Lumbar Discectomy). In: Advanced Techniques of Endoscopic Lumbar Spine Surgery. Springer; 2020. P. 123–136; relevant passage: pp. 133–134. Book chapter.
5. Liu X. Basic Principles of Unilateral Biportal Endoscopic Surgery: Intraoperative Radiation Exposure During UBE Procedures. In: Unilateral Biportal Endoscopy of the Spine: An Atlas of Surgical Techniques. Springer; 2022. P. 97–108; relevant passage: pp. 99–102. Book chapter.
Previous section: 1.10. Epidural anatomy in the endoscopic field