15.6. Approach
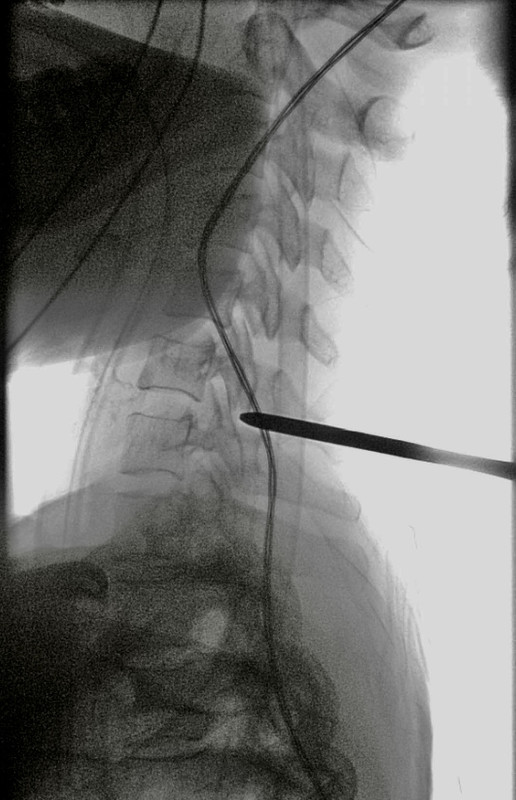
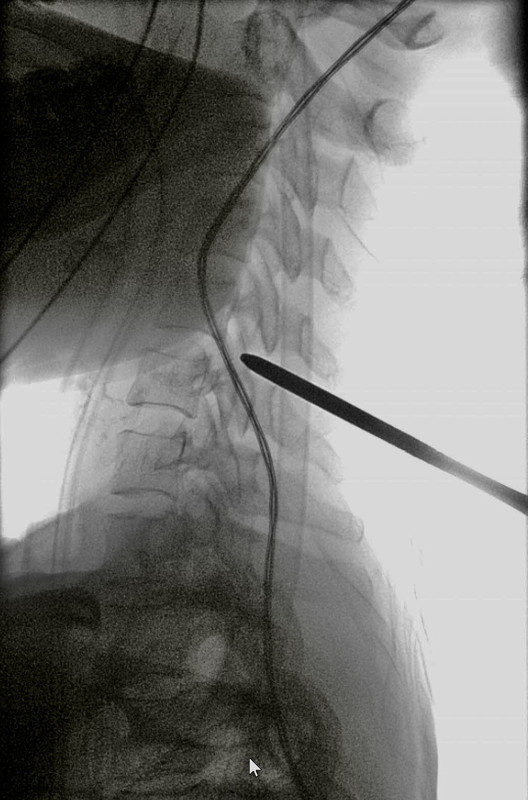
@ProfFishchenkoUsing the previously identified landmarks, we create access for the viewing and working portals. We insert the first sequential dilator into the viewing portal and check the level fluoroscopically.
If the dilator position does not match the planned level, we stop advancement, check vertebral numbering, and adjust the direction cranially or caudally with repeat fluoroscopic confirmation. Cervical anatomy may allow the same skin incisions to be used for an adjacent level.
We insert the second dilator. By touch, we identify the posterior bony vertebral elements: the cranial and caudal laminae, base of the spinous process, and inferior articular process of the cranial vertebra. We replace the dilators with a trocar and recheck the bony landmarks. If there is the slightest doubt about positioning, we perform fluoroscopic verification.
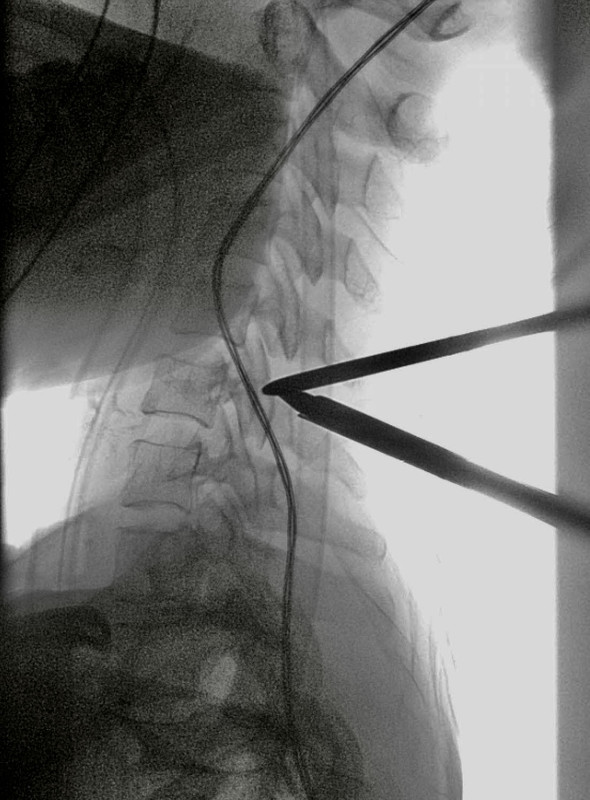
Through the second incision, we insert 2–3 sequential dilators, creating the working portal and triangulation with the trocar. We supplement the feeling of “metal-to-metal” contact with fluoroscopic verification of triangulation and the correct interlaminar level.
The short distance between adjacent cervical interlaminar spaces may lead to unintentional displacement to another level. At the start of surgery and after changing instrument direction, we repeat fluoroscopic verification as needed.
For gravity irrigation, we select the minimum sufficient saline bag height. We continuously maintain free outflow through the working portal. We address impaired outflow by checking the portal and system rather than increasing irrigation pressure.
⚠️ WARNING: Excessive saline pressure may cause excess fluid to enter the epidural space, with adverse consequences for the brain and optic nerves.
After removing the dilators, we insert a 5 mm RF electrode and visualize it with the endoscope. The main landmark is the vertebral lamina: we confirm its position by touch and sight.
We create the working space superficial to the ligamentum flavum, along the laminar surface, under continuous endoscopic visualization. We do not advance the instrument blindly or use force to enter beneath the ligamentum flavum. If the bony landmarks or instrument tip are not visible, we stop advancement and restore visualization.
References
1. Kim J, Heo DH, Lee DC, Chung HT. Biportal endoscopic unilateral laminotomy with bilateral decompression for the treatment of cervical spondylotic myelopathy. Acta Neurochirurgica. 2021;163(9):2537–2543.
2. Zhu C, et al. Unilateral biportal endoscopic laminectomy for treating cervical stenosis: a technical note and preliminary results. Medicina. 2023;59(2):305.
Previous section: 15.5. Radiological guidance