9.4. Bone Resection
@ProfFishchenkoIn this chapter, I describe central decompression combined with contralateral foraminal decompression. The sequence follows the technique for central stenosis: removal of the ligamentum flavum and bony overgrowth of the cranial and caudal laminae, with partial resection of the bases of the spinous processes and facet joints on both sides. We determine the extent of bone resection according to the structures causing compression and the visualization required.
Cranial Lamina and Ipsilateral Decompression
We begin bone resection using a 5 mm arthroscopic cutting burr at the junction of the base of the spinous process and the cranial vertebral lamina, then continue toward its inferior articular process. The cranial lamina is fairly wide, so we do not attempt to work across its entire surface immediately. We first remove the superficial 3–5 mm layer, then the middle layer. The deep layer can be removed with 3 mm, 45° Kerrison rongeurs, using the lower jaw to displace the ligamentum flavum that covers the spinal canal contents. With sufficient experience, we continue using the burr. The aim is to reach the cranial attachment of the ligamentum flavum to the lamina and visualize its free cranial edge.
After cranial laminar resection, we move laterally toward the inferior articular process. We resect 3–5 mm to visualize the medial border of the superior articular process (SAP) from its tip to its base.
Using 3 mm, 45° Kerrison rongeurs, we perform a small resection of the SAP base, approximately 3 mm. We preserve the ligamentum flavum at this stage because it covers the intracanal structures.
Caudal Lamina
Using a burr, we resect a superficial 4–5 mm layer of the caudal lamina from the base of the caudal spinous process to the SAP base. We remove the deep layer with reverse 90° Kerrison rongeurs up to the attachment of the ligamentum flavum. Its caudal edge usually attaches near the laminar border. Marked degenerative changes may require additional resection with the burr and Kerrison rongeurs. After visualizing and mobilizing the caudal edge of the ligament, we proceed to the next stage.
Crossing to the Contralateral Side
We identify the base of the cranial spinous process. Using an elevator, we bluntly detach the ligamentum flavum from it, pass the burr beneath the base of the process, and perform a partial resection. In my practice, I use a 5 mm burr; the reference extent of ventral surface resection remains approximately 4 mm, until the contralateral lamina is visualized. Burr diameter and resection depth are different measurements. The longitudinal space separating the ligamentum flavum into right and left portions serves as a landmark. If the ipsilateral portion obstructs the view, it can be removed at this stage.
Using an elevator, we bluntly detach the contralateral ligamentum flavum from the lamina. We do not insert the instrument deeply or attempt to detach the entire ligament in a single movement. We work gradually: mobilize a small area, resect bone, and repeat. We advance cranially and contralaterally. The aim is to mobilize the cranial edge of the contralateral ligamentum flavum and identify the inferior articular process of the cranial vertebra, the facet joint, and the superior articular process of the caudal vertebra.
If the base of the caudal spinous process obstructs further work, we detach the ligamentum flavum from it with an elevator and resect the bone with a burr. We similarly expose and partially resect the contralateral portion of the caudal lamina.
We clearly visualize the contralateral SAP from its base to its tip. Using 2–3 mm Kerrison rongeurs, we perform a small resection of its base. We bluntly detach the ligamentum flavum from the ventromedial SAP surface. If necessary, we resect its ventromedial portion with straight or curved 2–3 mm Kerrison rongeurs.
When possible, we preserve the ligamentum flavum until bone decompression is complete. If the ipsilateral portion was removed at an earlier stage, we continue working with the preserved contralateral portion.
Removal of the Ligamentum Flavum
We inspect the ligament around its perimeter, identify residual attachments to bone, and bluntly detach them with an elevator.
If the ipsilateral portion of the ligament remains intact, we begin removing it from the caudal edge. We carefully mobilize it away from neural structures using a curette, insert Kerrison rongeurs, and remove it in one fragment or in parts. We then proceed to the contralateral portion.
We identify the separation plane between the contralateral ligamentum flavum and the dura mater using a nonactivated dissector under direct visual guidance. We do not use an activated RF electrode to detach the ligament from neural structures.
If hemostasis is required, we use a 5 mm RF electrode in coagulation mode or a 1.5 mm electrode under video guidance, with continuous irrigation and free outflow. In my practice, we use COAG 2 on the BONSS ARS600 scale near neural structures — this is a setting level, not a value in watts. We restore clear visibility before continuing.
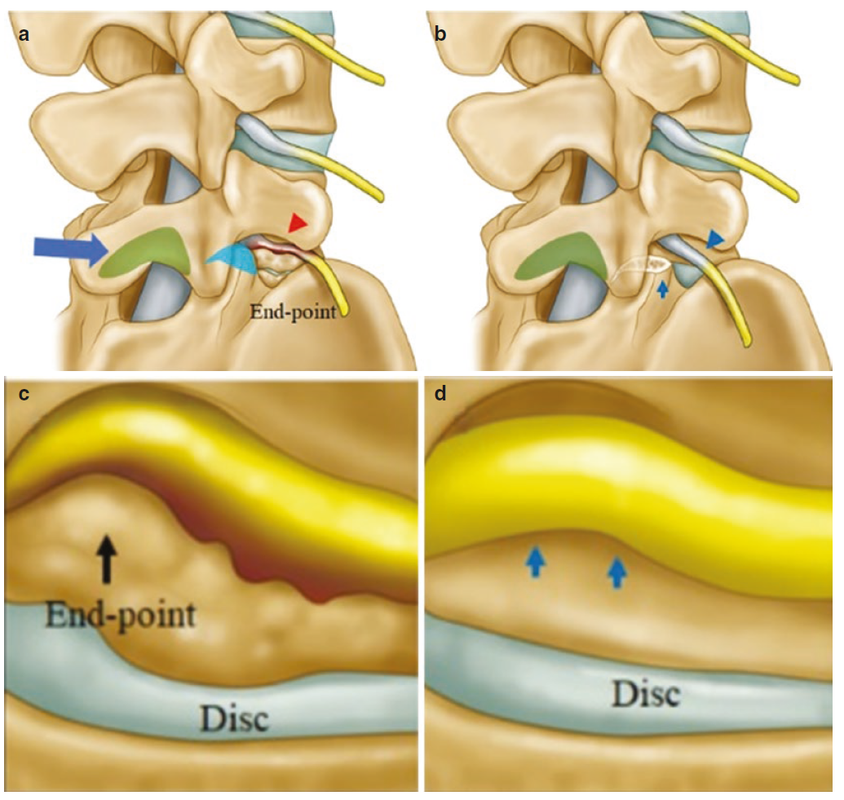
Foraminal Decompression
With the contralateral approach, the tip of the superior articular process (SAP) and the foraminal ligament serve as landmarks for the exiting nerve root. The ligament attaches in the region of the pedicle of the cranial vertebra and the SAP and covers the nerve root. Beneath it lies epidural fat, which guides identification of the neural structures [7].
When disc-space height is reduced and foraminal stenosis is present, the exiting nerve root may course immediately adjacent to the SAP tip. Before resecting the tip, the bony boundaries, the foraminal ligament attachments, and the position of the nerve root relative to the planned resection area should be identified [7].
After removing the ligamentum flavum, we clearly see the contralateral SAP. For foraminal decompression in the described technique, we resect up to 5 mm of its tip, corresponding to the osteotome width. We position a straight chisel vertically and separate the tip with light taps. We remove the fragment with an upturned rongeur. If ligaments retain it, we mobilize it toward the canal with a curette under visual guidance and remove it with rongeurs.
Assessment of decompression completeness
After completion of combined central and contralateral foraminal decompression, the dural sac, both lateral recesses, and the contralateral intervertebral foramen should be inspected in sequence. The inspection should cover all sites of compression identified during preoperative planning [6, 7].
In the lateral recesses, decompression of the caudally coursing nerve roots is checked; in the intervertebral foramen, decompression of the nerve root exiting at the operated level is assessed. For example, at L4–L5, bilateral lateral recess stenosis with concomitant contralateral foraminal stenosis requires assessment of both L5 nerve roots and the contralateral L4 nerve root [7].
Under direct endoscopic visualization, the space around the nerve roots at the sites of previous bony and ligamentous compression is carefully checked with a blunt probe, avoiding forceful traction. Particular attention is paid to residual edges of the ligamentum flavum and bony prominences. Dural sac pulsation is assessed together with the findings of endoscopic inspection and probing [6].
Completion of Surgery
We remove loose bone fragments and perform meticulous hemostasis. Under endoscopic video guidance, we introduce a No. 15 drain into the created cavity through the working portal, keeping it away from the exposed nerve, and secure it to the skin. In my practice, I remove it the next day, or immediately if neural structures are irritated. Irritation may result either from contact or from the negative pressure created by the drain. We do not place a drain after an intraoperative dural injury or during BELIF/UBE-LIF.
We close each skin incision with a single interrupted Vicryl 2-0 suture.
Source of the illustration — Springer publication
References
1. Yeung YK, Park CW, Jun SG, Park JH, Tse ACY. Comparative cohort study for expansion of lateral recess and facet joint injury after biportal endoscopic ipsilateral decompression and contralateral decompression. Asian Spine J. 2022;16(4):560-566. doi:10.31616/asj.2020.0656.
2. Akbary K, Kim JS, Park CW, Jun SG, Hwang JH. Biportal endoscopic decompression of exiting and traversing nerve roots through a single interlaminar window using a contralateral approach: technical feasibilities and morphometric changes of the lumbar canal and foramen. World Neurosurg. 2018;117:153-161. doi:10.1016/j.wneu.2018.05.111.
3. Tian D, Zhu B, Liu J, Chen L, Sun Y, Zhong H, et al. Contralateral inclinatory approach for decompression of the lateral recess and same-level foraminal lesions using unilateral biportal endoscopy: a technical report. Front Surg. 2022;9:959390. doi:10.3389/fsurg.2022.959390.
4. Heo DH, Park DY, Hong YH, Kim D, Kim JS. Temperature change of epidural space by radiofrequency use in biportal endoscopic lumbar surgery: safety evaluation of radiofrequency. Eur Spine J. 2023;32(8):2769-2775. doi:10.1007/s00586-023-07719-z.
5. Krzok G, Telfeian AE, Wagner R, Hofstetter CP, Iprenburg M. Contralateral facet-sparing sublaminar endoscopic foraminotomy for the treatment of lumbar lateral recess stenosis: technical note. J Spine Surg. 2017;3(2):260-266. doi:10.21037/jss.2017.06.11.
6. Yang H.-S., Heo D.H., Park J.-Y. Biportal Endoscopic Approach for Lumbar Central Stenosis. In: Advanced Techniques of Endoscopic Lumbar Spine Surgery. Springer; 2020. P. 45–54; relevant passage: pp. 49–50. Link to the book chapter.
7. Heo D.H., Jun S.G., Park C.W. Contralateral Sublaminar Approach for Lumbar Foraminal Stenosis Using Biportal Endoscopic Surgery. In: Advanced Techniques of Endoscopic Lumbar Spine Surgery. Springer; 2020. P. 83–90. Link to the book chapter.
Previous section: 9.3. Surgical Approach
Next section: Clinical Examples (with Video Explanation)