8.6. Specific Features of the Left-Sided L5–S1 Approach
@ProfFishchenkoPrevious section: Specific Features of the Right-Sided L5–S1 Approach
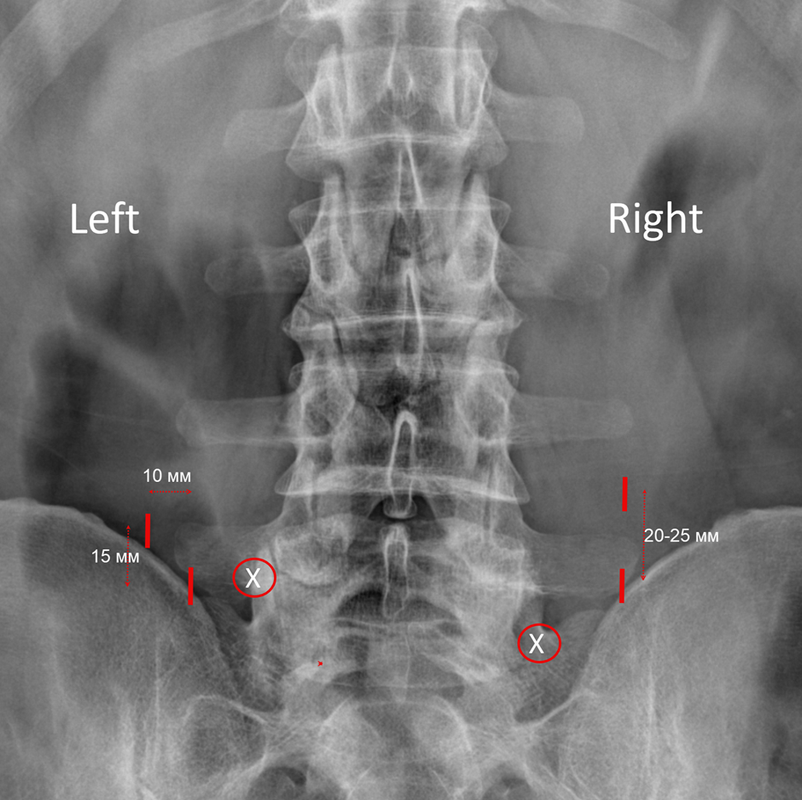
In my practice, I consider the left-sided L5–S1 approach the least comfortable for a right-handed surgeon. The iliac crest limits lateral displacement from the lateral pedicle line and instrument movement. We therefore plan the incisions correctly from the outset and create the endoscopic and working portals.
We plan the endoscopic portal incision over the edge of the slope of the iliac crest, at the level of the proximal border of the transverse process. From the center of this incision, we move 15 mm distally and 10 mm medially. The resulting point is the center of the working portal incision.
The instrument meeting point is the distal portion of the junction between the base of the transverse process and the lamina of L5.
References
1. Choi DJ, Kim JE, Jung JT, et al. Biportal endoscopic spine surgery for various foraminal lesions at the lumbosacral lesion. Asian Spine J. 2018;12(3):569–573. doi:10.4184/asj.2018.12.3.569.
2. Kim JE, Choi DJ. Unilateral biportal endoscopic spinal surgery using a 30° arthroscope for L5-S1 foraminal decompression. Clin Orthop Surg. 2018;10(4):508–512. doi:10.4055/cios.2018.10.4.508.
3. Ahn JS, Lee HJ, Choi DJ, Lee KY, Hwang SJ. Extraforaminal approach of biportal endoscopic spinal surgery: a new endoscopic technique for transforaminal decompression and discectomy. J Neurosurg Spine. 2018;28(5):492–498. doi:10.3171/2017.8.SPINE17771.
Next section: Clinical Examples (with Video Explanation)