8.3. Surgical Approach
@ProfFishchenkoPrevious section: Equipment and Instruments
During planning in my practice, I obtain CT in addition to MRI to clearly identify the structures compressing the nerve root. I plan their resection in advance: this helps optimize operating time and maintain orientation during surgery.
In my practice, I position the patient prone on a Wilson frame to provide lumbar flexion. We coordinate the position of the head and trunk with the anesthesiologist to maintain ventilation and venous outflow. We keep the head neutral and avoid pressure on the eyes and abdomen. The anesthesiologist determines the target blood pressure individually, considering baseline pressure, comorbidities, and organ perfusion. In my practice, a systolic pressure of approximately 100 mmHg may serve as a reference when clinically appropriate. We place soft pads beneath the knees and lower legs.
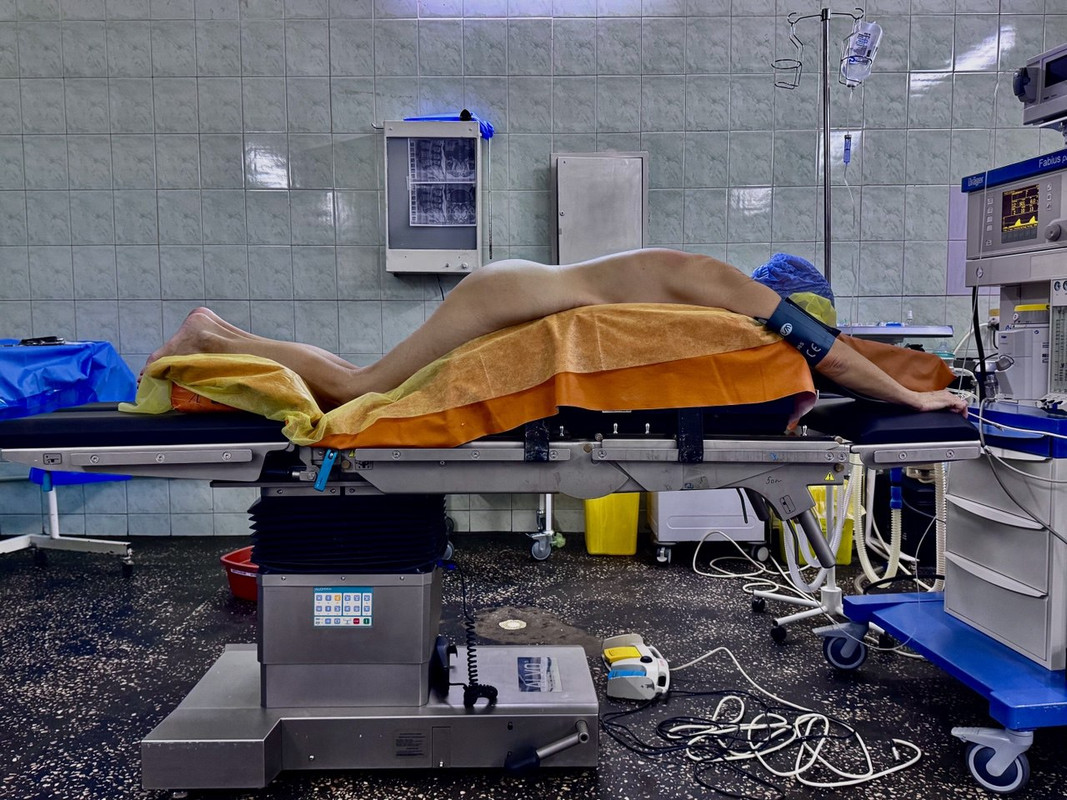
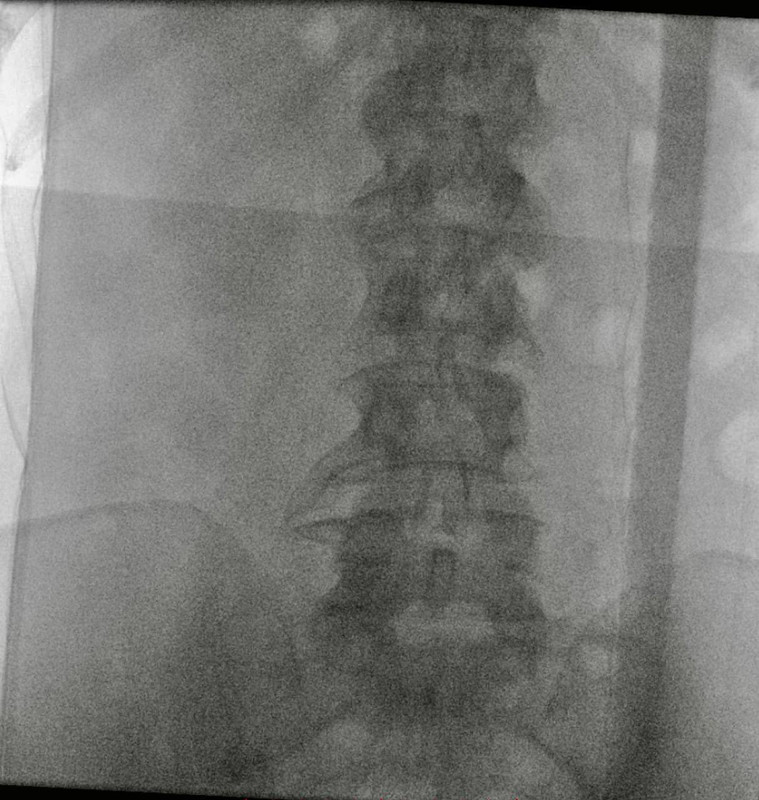
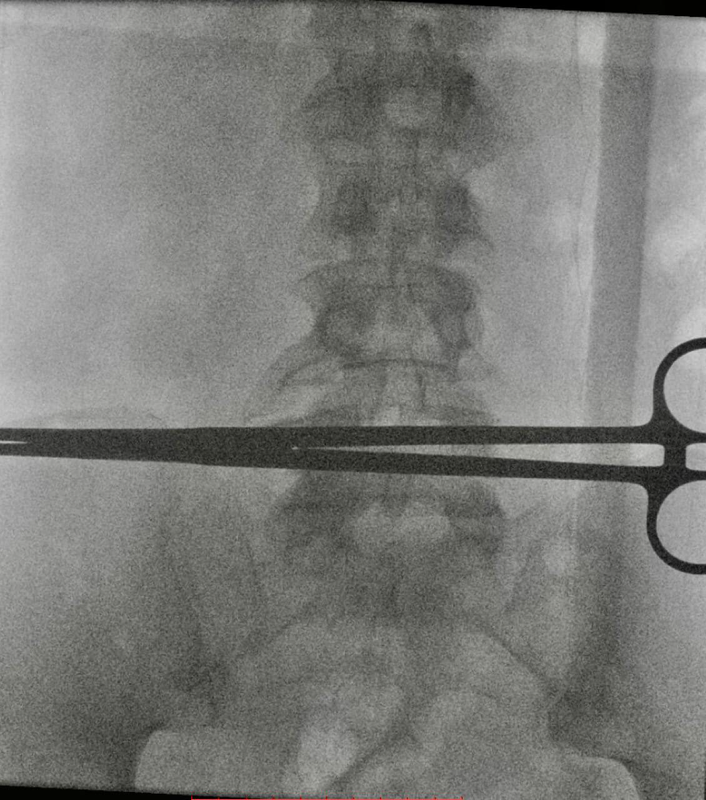
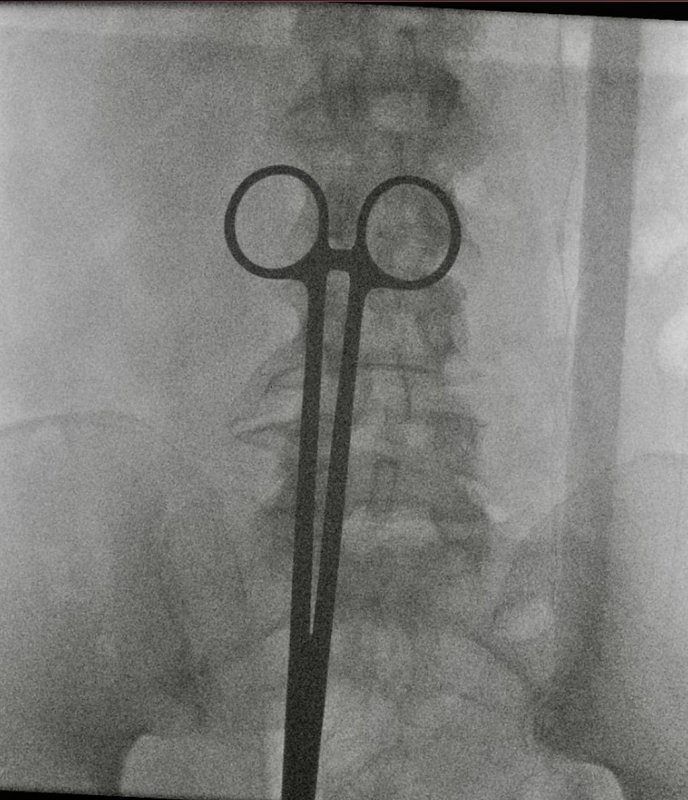
Before making the incision, we confirm the operative level using the C-arm and correlate vertebral numbering with the preoperative images. We obtain an anteroposterior image. We use a lateral view whenever there is doubt about the level or instrument depth, particularly in lumbarization, sacralization, or hyperlordosis. If necessary, we repeat the lateral check while placing the trocar and dilators.
Left-Sided Approach
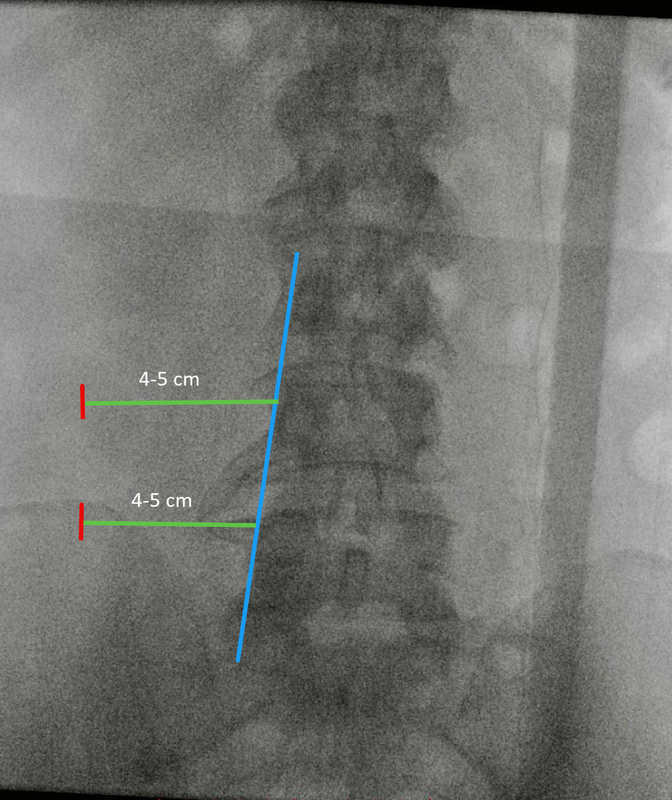
The radiographic landmarks are the transverse processes of the adjacent vertebrae at the required level. We mark the pedicles on the skin and draw a line between their lateral borders — the lateral pedicle line. We move 3–5 cm lateral to this line according to the patient's build: 3–4 cm in patients of slender build and 4–5 cm in overweight patients. We plan the proximal portal at the level of the transverse process of the cranial vertebra and the distal portal at the level of the transverse process of the caudal vertebra.
Right-Sided Approach
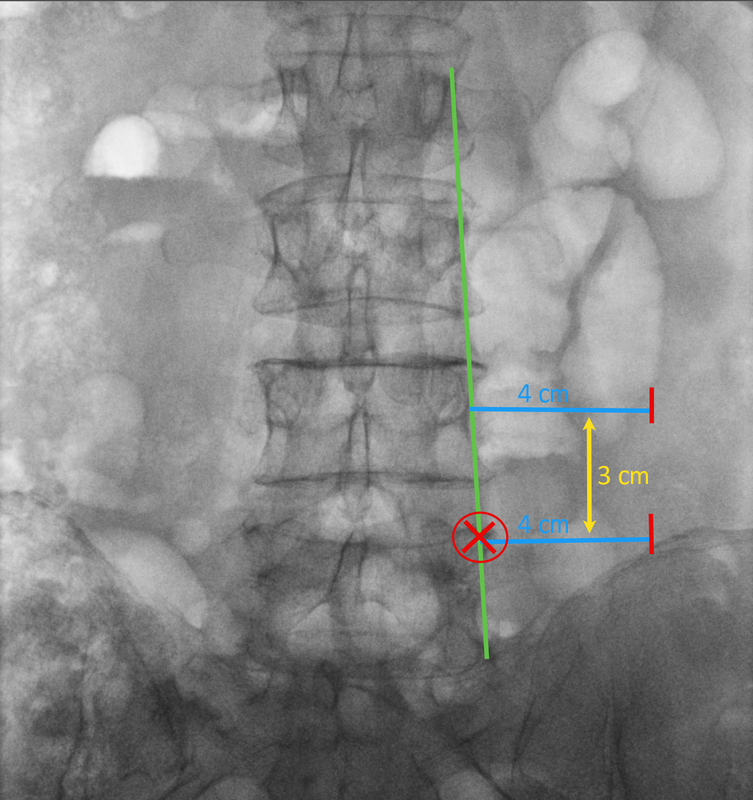
We perform right-sided marking according to the same principles. The radiographic landmarks are the transverse processes of the adjacent vertebrae at the required level. We mark the pedicles on the skin and draw a line between their lateral borders — the lateral pedicle line. We move 3–5 cm lateral to this line according to the patient's build: 3–4 cm in patients of slender build and 4–5 cm in overweight patients. We plan the proximal portal at the level of the transverse process of the cranial vertebra and the distal portal at the level of the transverse process of the caudal vertebra.
Endoscopic Portal
In my practice, I hold the endoscope in my left hand and instruments in my right. For the left-sided approach, we use the cranial portal for the endoscope and the caudal portal for instruments; their roles are reversed for the right-sided approach.
I prefer longitudinal skin incisions. We anticipate the possibility of conversion to microdiscectomy before surgery, particularly during training: longitudinal incisions are easier to join if needed.
We first create the endoscopic portal. Using a pointed scalpel, we incise the skin, subcutaneous fat, and the outer fascial layer of the longissimus muscle. We approach at an angle of 20–40° toward the base of the transverse process.
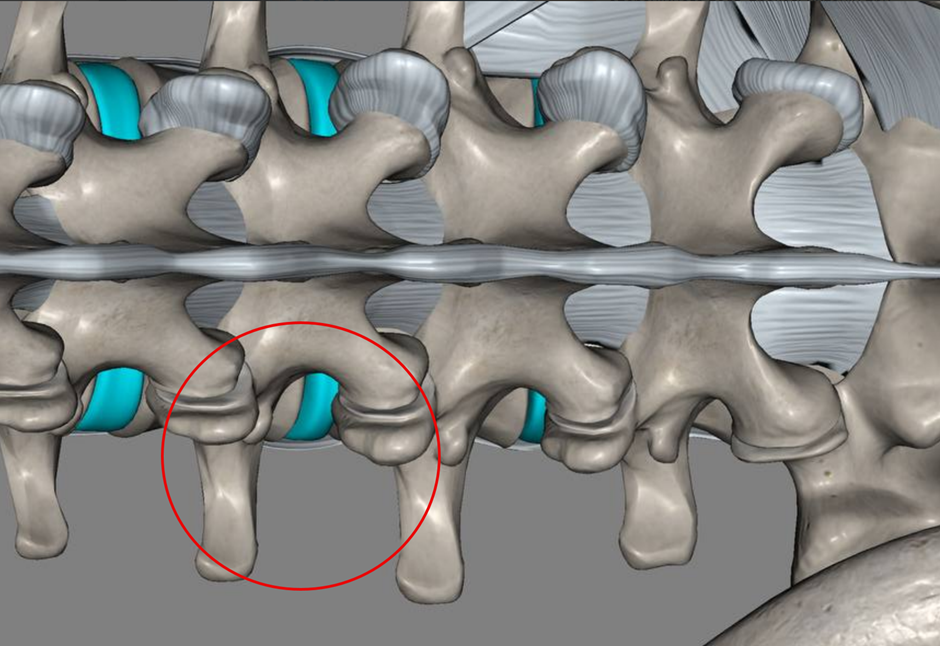
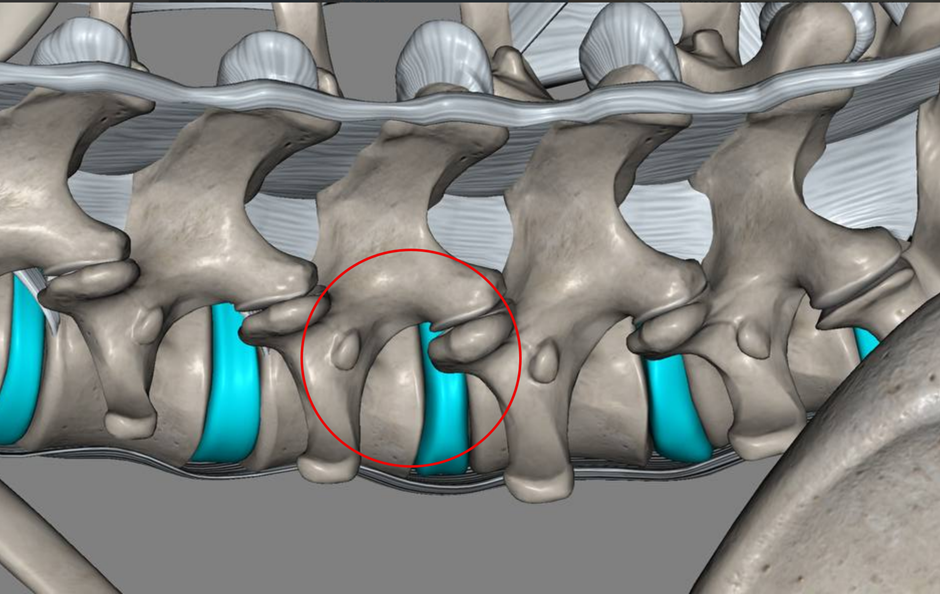
We introduce the first and second dilators through the opening, making contact with the junction of the lamina and the base of the transverse process. We dissect the muscles using dilators or dedicated muscle dissectors. By palpation, we identify the bony landmarks: the dorsal part of the base of the transverse process, the lateral part of the base of the superior articular process, the interarticular portion of the lamina (isthmus), the dorsolateral part of the base of the inferior articular process, and the dorsolateral part of the superior articular process.
Carefully, without advancing deeply into the paravertebral space, we identify the posterolateral surface of the posterior elements of the adjacent vertebrae. We remove the dilators and introduce a trocar into the created portal tract. We again palpate the bone and the slope between the dorsal part of the base of the transverse process and the lateral part of the base of the superior articular process.
Working Portal
Using a pointed scalpel, we incise the skin, subcutaneous fat, and the outer layer of the thoracolumbar fascia (fascia thoracolumbalis) at an angle of 20–40° toward the base of the transverse process. We rotate the scalpel 90° and make an additional transverse fascial incision. This creates a cruciate incision in the thoracolumbar fascia to improve fluid outflow.
We sequentially introduce three dilators through the opening. We again palpate the bone: the dorsal part of the base of the transverse process, the lateral part of the base of the superior articular process of the lower vertebra, and the lateral part of the inferior articular process of the upper vertebra. We bring the dilators together with the trocar passed through the endoscopic portal and confirm metal-to-metal contact by palpation. The meeting point is the isthmus of the upper vertebra.
At this stage, we obtain a lateral radiograph if necessary.
We replace the trocar stylet with the scope and camera. We replace the dilators with an RF electrode with a 5 mm working tip. We confirm its position under endoscopic video guidance. The meeting point is the isthmus of the upper vertebra.
The bony landmarks must be identified by palpation and confirmed visually. Bone itself provides the landmark and the safest zone. Reliable orientation is impossible without visualization of bone.
We then use the RF electrode in ablation mode to expose the distal border of the transverse process of the cranial vertebra, the isthmus, the inferior and superior articular processes, and the proximal part of the transverse process of the caudal vertebra. After identifying the bony landmarks, we remove excess soft tissue lateral to these structures with a shaver (Tomcat, Aggressive Plus, 5 mm) or continue ablation with the RF electrode.
At this stage, we clearly visualize the distal border of the transverse process of the cranial vertebra, the isthmus, the inferior and superior articular processes, and the proximal part of the transverse process of the caudal vertebra.
We advance deeper, carefully exposing the superior articular process of the caudal vertebra and its distal portion.
If instrument position is uncertain or bony landmarks are lost, we obtain anteroposterior and lateral radiographic checks before continuing.
Caution: Loss of Orientation
During the early stages of learning the technique, limited experience may lead to unintentional advancement deeper than the intervertebral foramen and ventrally along the vertebral body. This may injure a segmental artery and cause excessive fluid accumulation in the retroperitoneal space.
If orientation is lost, we do not continue advancing blindly: we clarify instrument position using radiographic checks in two views.
With limited experience, advancement may occur predominantly in a dorsal → ventral direction rather than a lateral → medial direction.
Hemostasis
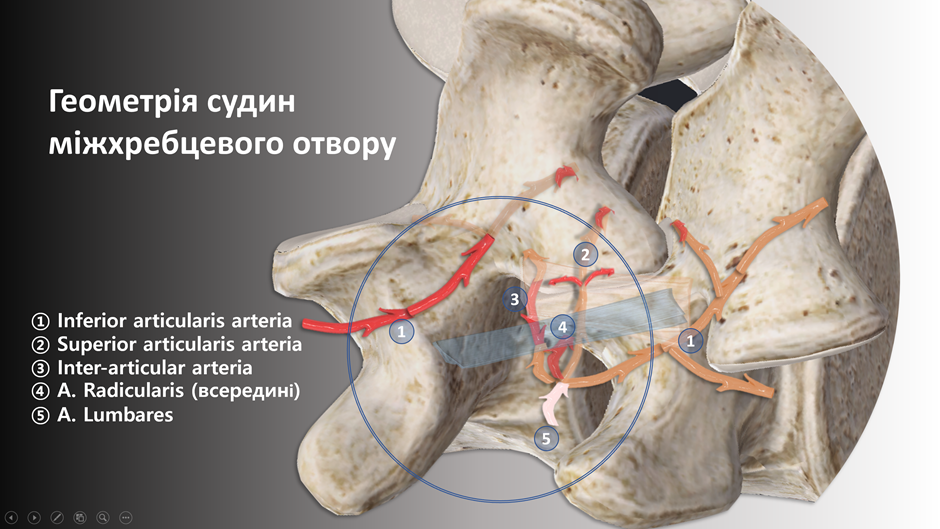
I identify five principal sites of potential bleeding:
1. The junction of the base of the transverse process and the base of the inferior articular process of the cranial vertebra.
2. The junction of the base of the transverse process and the base of the superior articular process of the caudal vertebra.
3. The area around the superior articular process.
4. The area near the tip of the superior articular process.
5. After ligament resection and nerve identification — the vascular network of the radicular artery accompanying the spinal nerve.
References
1. Ahn JS, Lee HJ, Choi DJ, Lee KY, Hwang SJ. Extraforaminal approach of biportal endoscopic spinal surgery: a new endoscopic technique for transforaminal decompression and discectomy. J Neurosurg Spine. 2018;28(5):492–498. doi:10.3171/2017.8.SPINE17771.
2. Choi DJ, Kim JE, Jung JT, et al. Biportal endoscopic spine surgery for various foraminal lesions at the lumbosacral lesion. Asian Spine J. 2018;12(3):569–573. doi:10.4184/asj.2018.12.3.569.
3. Saugel B, Fletcher N, Gan TJ, et al; POQI XI Workgroup. PeriOperative Quality Initiative (POQI) international consensus statement on perioperative arterial pressure management. Br J Anaesth. 2024;133(2):264–276. doi:10.1016/j.bja.2024.04.046.
4. American Society of Anesthesiologists Task Force on Perioperative Visual Loss, North American Neuro-Ophthalmology Society, Society for Neuroscience in Anesthesiology and Critical Care. Practice advisory for perioperative visual loss associated with spine surgery 2019. Anesthesiology. 2019;130(1):12–30. doi:10.1097/ALN.0000000000002503.
Next section: Nerve Identification