8.1. Indications and Contraindications
@ProfFishchenkoPrevious section: Foraminal Stenosis
Indications
I consider BESS/UBE decompression for symptomatic foraminal stenosis when the clinical presentation corresponds to the location of compression on MRI and radicular pain persistently limits function despite adequate nonoperative treatment, or when a significant or progressive neurological deficit is present. MRI evidence of foraminal narrowing alone is not an indication for surgery.
• Foraminal stenosis associated with facet joint hypertrophy.
• A calcified or ossified disc herniation with foraminal compression.
• Disc herniation combined with foraminal stenosis.
When segmental instability is also present, I assess the need for decompression with additional stabilization using an interbody cage and minimally invasive transpedicular fixation. Instability is not an independent indication for isolated foraminal decompression.
Contraindications and Limitations of Isolated BESS/UBE Decompression
These limitations concern the described decompression for degenerative stenosis, rather than every endoscopic procedure.
• General contraindications to the selected type of anesthesia.
• Segmental instability or deformity requiring stabilization or correction.
• Stenosis caused by a neoplastic process.
• Stenosis caused by an infectious process.

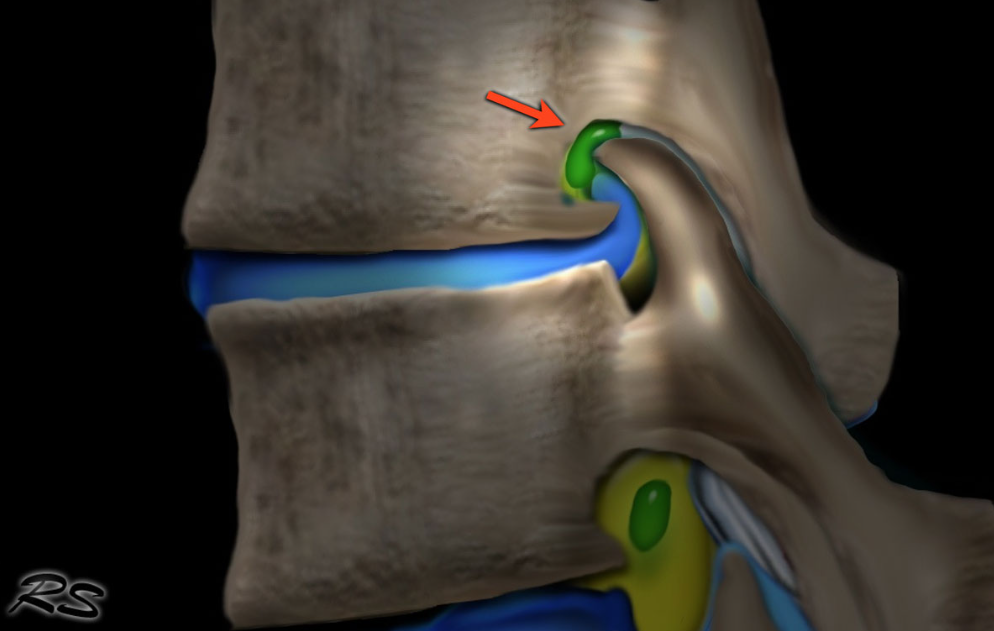
Source of Fig. 2 — The Radiology Assistant
Mechanism of Foraminal Compression and Selection of the Extent of Surgery
In foraminal stenosis, the exiting root and the extent of its compression from the entrance to the foramen to the extraforaminal region are identified. Sagittal and axial images are compared, and the perineural fat, root shape, and positions of osteophytes and the facet are assessed. Loss of the perineural fat space helps localize the narrowing; this finding is correlated with the clinical presentation. When choosing between foraminotomy and a procedure with stabilization, it is important to distinguish a local bony component from compression associated with substantial loss of disc height. In the presence of listhesis or rotation, the anatomy is clarified using standing radiographs and, if necessary, CT. Before surgery, it is determined whether the planned resection will completely release the root while preserving the supporting portion of the facet. If the target extends beyond the foramen, the corresponding component is planned separately.
References
1. Heo DH, Park DY, Hong HJ, Hong YH, Chung H. Indications, Contraindications, and Complications of Biportal Endoscopic Decompressive Surgery for the Treatment of Lumbar Stenosis: A Systematic Review. World Neurosurg. 2022;168:411–420. DOI: 10.1016/j.wneu.2022.09.023.
2. Sharif S, Shaikh Y, Bajamal AH, Costa F, Zileli M. Fusion Surgery for Lumbar Spinal Stenosis: WFNS Spine Committee Recommendations. World Neurosurg X. 2020;7:100077. DOI: 10.1016/j.wnsx.2020.100077.
3. Kim JE, Choi DJ, Park EJ. Clinical and Radiological Outcomes of Foraminal Decompression Using Unilateral Biportal Endoscopic Spine Surgery for Lumbar Foraminal Stenosis. Clin Orthop Surg. 2018;10(4):439–447. DOI: 10.4055/cios.2018.10.4.439.
Next section: Equipment and Instruments