5.9. Specific Features of the Left-sided Approach at L5–S1
@ProfFishchenkoIn my practice, I consider this approach the least convenient for a right-handed surgeon. The iliac crest may restrict lateral portal positioning and instrument manipulation. I therefore carefully plan the incisions for the endoscopic and working portals before starting the procedure.
On the fluoroscopic projection, I mark the endoscopic portal incision at the edge of the slope of the iliac crest, at the level of the proximal edge of the transverse process. From the center of this incision, I move 15 mm distally and 10 mm medially. The resulting point is the center of the planned working portal incision.
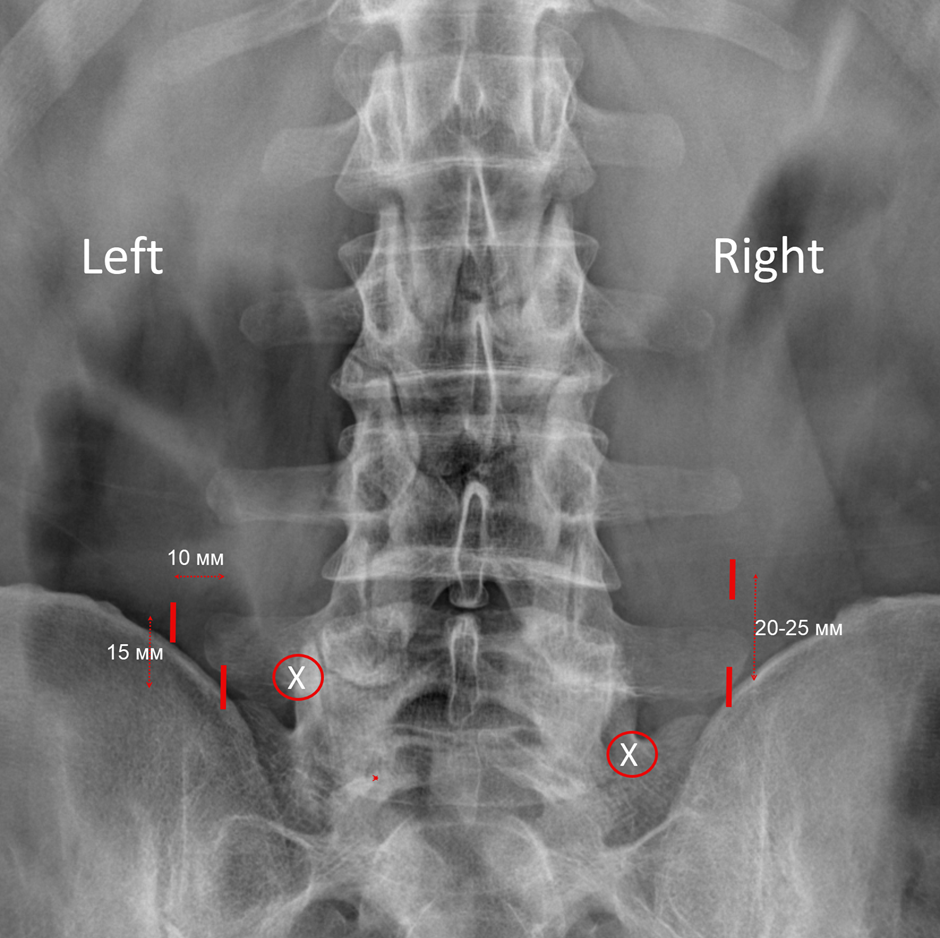
The triangulation point is the distal portion of the junction between the base of the transverse process and the L5 lamina.
References
1. Park JH, Jung JT, Lee SJ. How I do It: L5/S1 foraminal stenosis and far-lateral lumbar disc herniation with unilateral bi-portal endoscopy. Acta Neurochir (Wien). 2018;160(10):1899–1903. DOI: 10.1007/s00701-018-3630-9.
2. Choi DJ, Kim JE, Jung JT, et al. Biportal endoscopic spine surgery for various foraminal lesions at the lumbosacral lesion. Asian Spine J. 2018;12(3):569–573. DOI: 10.4184/asj.2018.12.3.569.
3. Ahn JS, Lee HJ, Choi DJ, Lee KY, Hwang SJ. Extraforaminal approach of biportal endoscopic spinal surgery: a new endoscopic technique for transforaminal decompression and discectomy. J Neurosurg Spine. 2018;28(5):492–498. DOI: 10.3171/2017.8.SPINE17771.
Previous section: 5.8. Specific Features of the Right-sided Approach at L5–S1
Next section: 5.10. Clinical Examples (Videos with Commentary)