4.3. Approach
@ProfFishchenkoPatient positioning and level identification
In my practice, for the BESS/UBE interlaminar approach, I position the patient prone on a Wilson frame with the lumbar spine flexed. This widens the interlaminar space and helps limit unnecessary bone resection. We coordinate head and trunk positioning with the anesthesiologist to maintain ventilation and venous outflow. We keep the head neutral and avoid pressure on the eyes and abdomen. The anesthesiologist determines the target arterial pressure individually, considering baseline pressure, comorbidities, and organ perfusion. In my practice, a systolic pressure of around 100 mmHg may serve as a guide when clinically appropriate. We place soft cushions under the knees and lower legs.
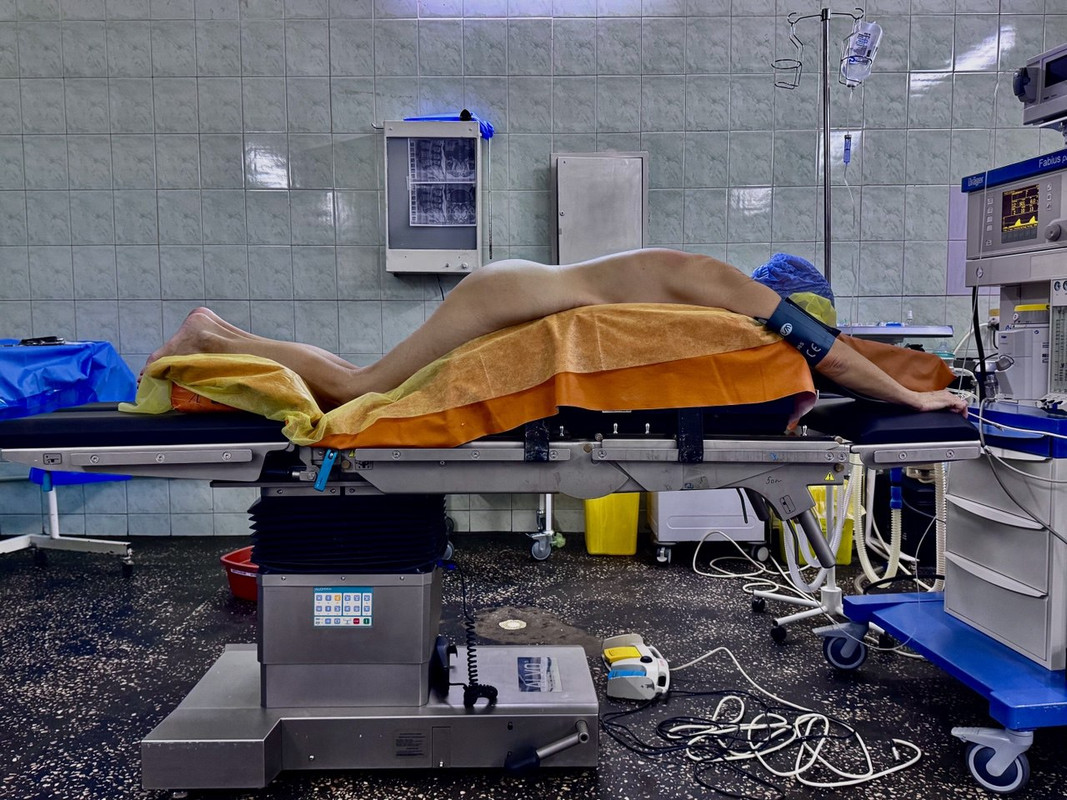
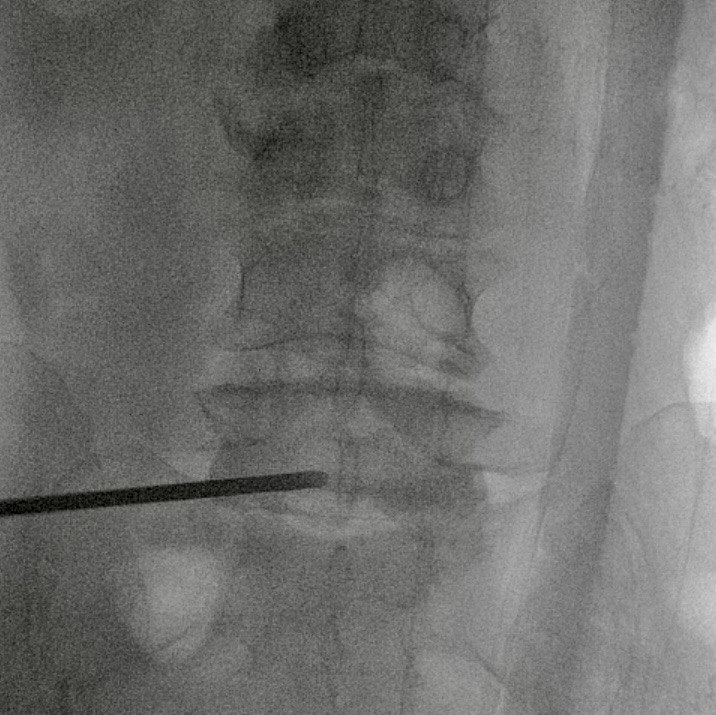
Before incision, we confirm the surgical level using the C-arm, correlating vertebral numbering with the preoperative images. We obtain an anteroposterior image. We use a lateral view whenever there is doubt about the level or instrument depth, especially in lumbarization, sacralization, or hyperlordosis. If needed, we repeat lateral imaging after placement of the trocar and dilators.
Left-sided approach
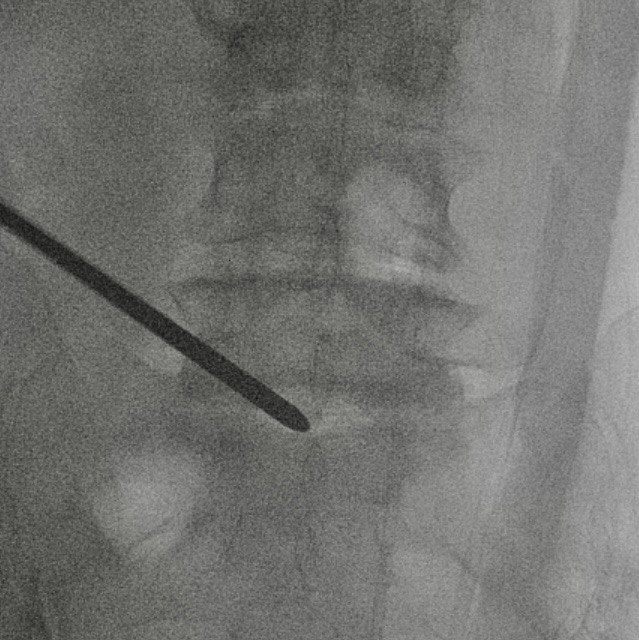
The radiological landmark is the interlaminar space at the corresponding level. We mark the intervertebral disc level on the skin. We plan the endoscopic (cranial) portal immediately lateral to the spinous process at the level of the cranial lamina. We position the working (caudal) portal 2 cm caudally in patients of slender or average build and 3–4 cm caudally in overweight patients.
Right-sided approach
The radiological landmark is the interlaminar space at the corresponding level. We mark the intervertebral disc level on the skin. We plan the endoscopic (caudal) portal immediately lateral to the spinous process at the level of the caudal lamina. We position the working (cranial) portal 2 cm cranially in patients of slender or average build and 3–4 cm cranially in overweight patients. I prefer longitudinal incisions 7–10 mm long.
We plan for possible conversion before starting surgery, especially during training. If needed, the longitudinal incisions can be joined and the approach extended for microsurgical or open discectomy.
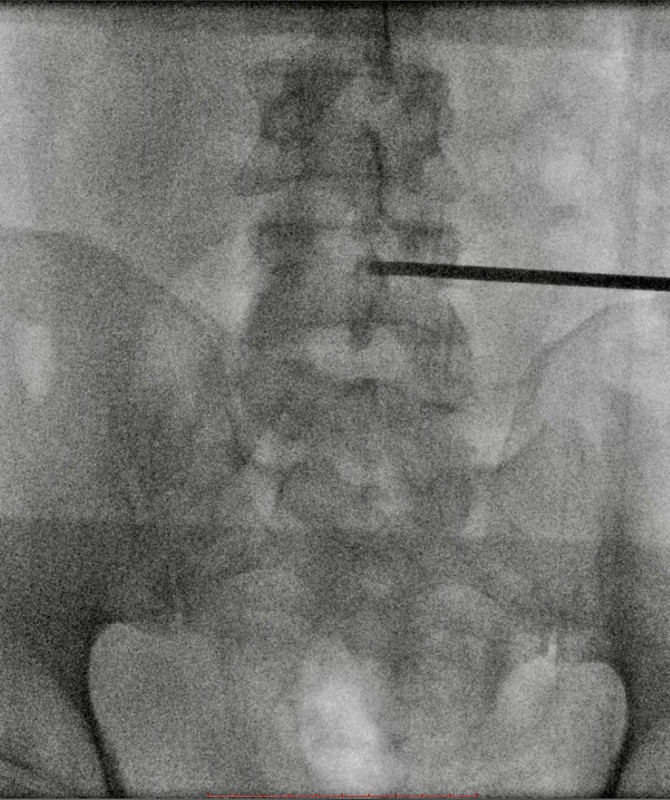
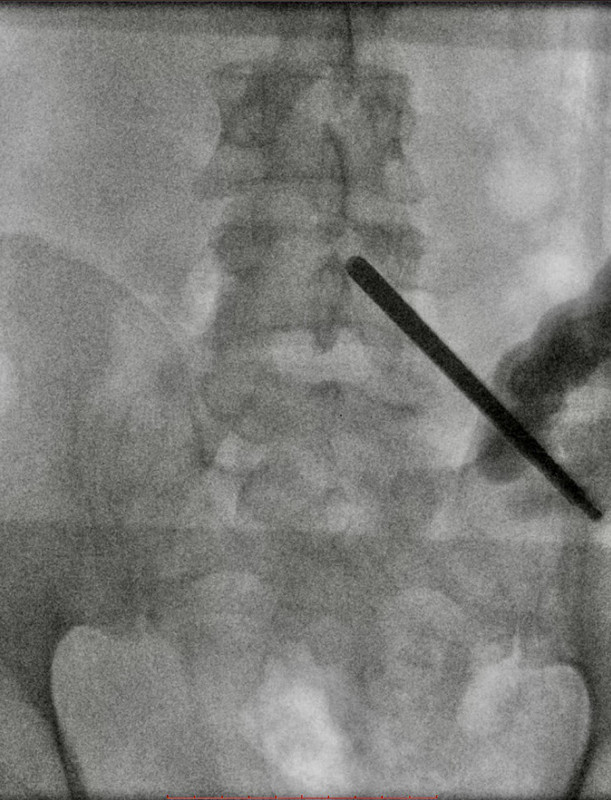
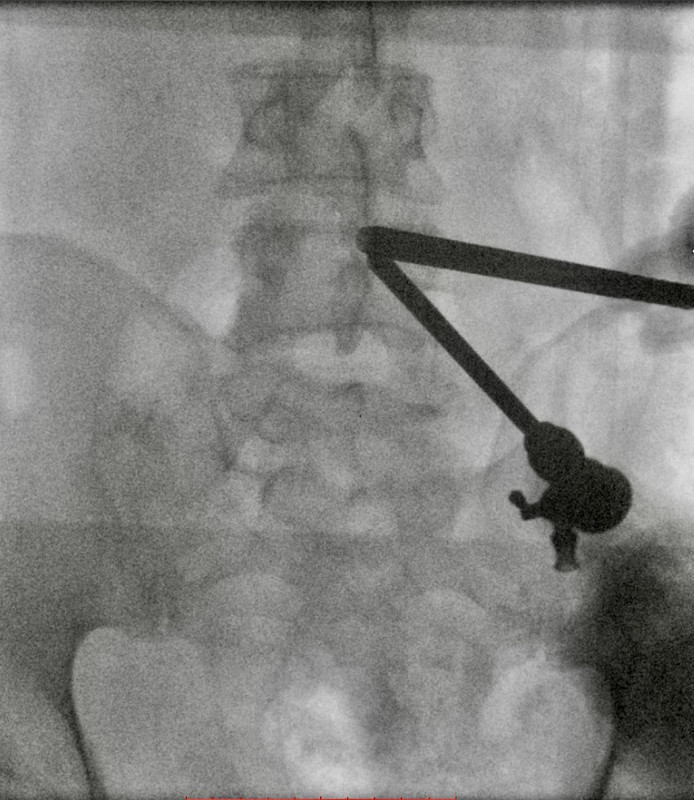
Endoscopic portal
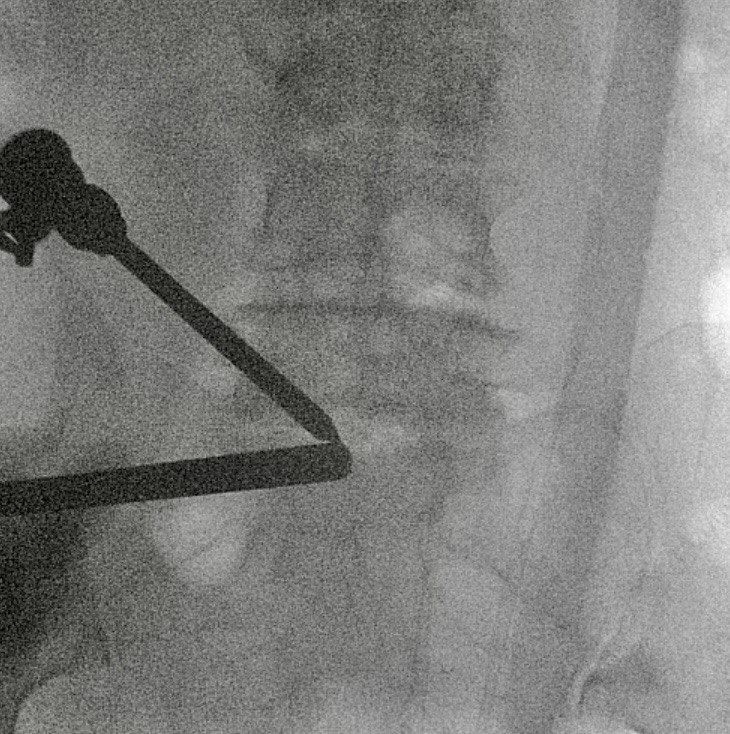
Using a pointed scalpel, we incise the skin, subcutaneous fat, and outer layer of the longissimus fascia. Through the resulting opening, we insert the first and second dilators until they contact the vertebral lamina. We detach the muscles from the lamina with dilators or dedicated muscle dissectors. We identify the bony landmarks by touch: the lamina, inferior articular process, and slope into the interlaminar space. We palpate them carefully without dropping into the interlaminar space. We remove the dilators and insert the trocar into the established portal tract, again identifying contact with bone.
Working portal
Using a pointed scalpel, we incise the skin, subcutaneous fat, and outer layer of the thoracolumbar fascia (fascia thoracolumbalis). We rotate the scalpel by 90° and make a transverse fascial incision. This creates a cruciate fascial incision to allow free outflow of irrigation fluid. We insert three dilators of progressively increasing diameter. By touch, we identify bone and bring the dilators into contact with the trocar passed through the endoscopic portal, establishing “metal-to-metal” contact. If there is doubt about instrument position or depth, we obtain a lateral radiological check.
Creating the working space
We replace the trocar stylet with the endoscope and camera. Through the working portal, we insert an RF electrode with a 5 mm working tip and identify its tip on the vertebral lamina. Bony structures must be clearly recognized. Further advancement is performed under direct endoscopic visualization. If the bony landmark or tissue plane cannot be identified, we stop and restore visualization. We do not advance instruments blindly or force them beneath the ligamentum flavum.
Next, using the RF electrode in ablation mode, we expose the cranial and caudal laminae and the inferior articular process. After identifying the bony landmarks, we remove the remaining soft tissues over the ligamentum flavum with a shaver fitted with a Tomcat or Aggressive Plus blade, or continue using the RF electrode in ablation mode. The working part of the instrument must remain in view at all times; we maintain free outflow of irrigation fluid. At this stage, we clearly visualize:
- the base of the spinous process;
- the lamina and inferior articular process of the cranial vertebra;
- the lamina and base of the spinous process of the caudal vertebra.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral Biportal Endoscopy for Lumbar Spinal Stenosis and Lumbar Disc Herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. doi:10.2106/JBJS.ST.22.00020.
2. Choi CM, Chung JT, Lee SJ, Choi DJ. How I do it? Biportal endoscopic spinal surgery (BESS) for treatment of lumbar spinal stenosis. Acta Neurochir (Wien). 2016;158(3):459–463. doi:10.1007/s00701-015-2670-7.
3. Choi DJ, Jung JT, Lee SJ, Kim YS, Jang HJ, Yoo B. Biportal Endoscopic Spinal Surgery for Recurrent Lumbar Disc Herniations. Clin Orthop Surg. 2016;8(3):325–329. doi:10.4055/cios.2016.8.3.325.
4. Saugel B, Fletcher N, Gan TJ, et al; POQI XI Workgroup. PeriOperative Quality Initiative (POQI) international consensus statement on perioperative arterial pressure management. Br J Anaesth. 2024;133(2):264–276. doi:10.1016/j.bja.2024.04.046.
5. American Society of Anesthesiologists Task Force on Perioperative Visual Loss; North American Neuro-Ophthalmology Society; Society for Neuroscience in Anesthesiology and Critical Care. Practice Advisory for Perioperative Visual Loss Associated with Spine Surgery 2019. Anesthesiology. 2019;130(1):12–30. doi:10.1097/ALN.0000000000002503.
Previous section: 4.2. Equipment and instruments
Next section: 4.4. Bone resection