4.10. Features of operating from the right side
@ProfFishchenkoMost surgeons are right-handed: they hold the endoscope in the left hand and operate with the right. Working from the right side therefore presents substantial ergonomic difficulties for most surgeons. The right-sided technique has specific features of access, anatomical orientation, and bone resection.
The radiological landmark is the interlaminar space at the target level. I mark the intervertebral disc level on the skin. I plan the endoscopic portal immediately lateral to the spinous process at the level of the caudal vertebral lamina. I position the working (cranial) portal 2 cm cranial to the endoscopic portal in slender patients and patients of average build, or 3–4 cm cranial in patients with obesity.
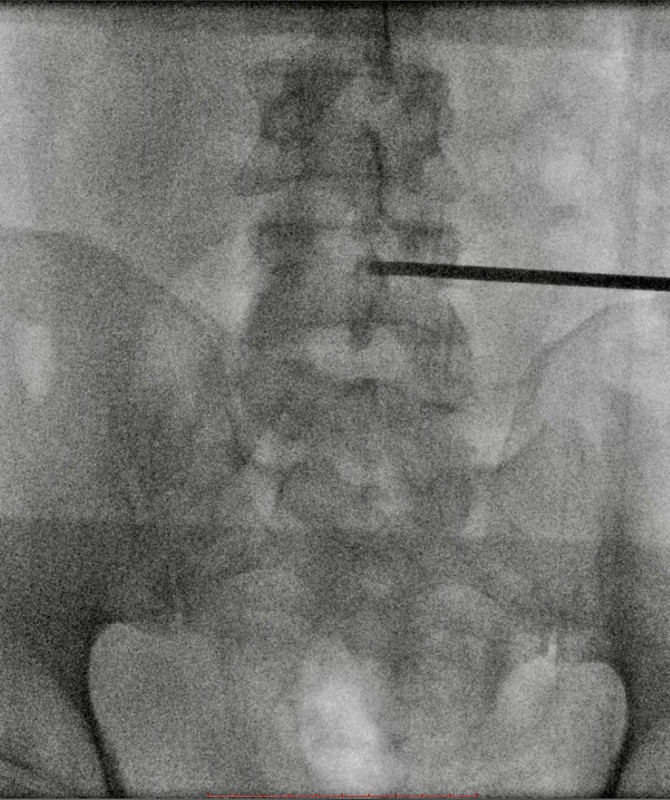
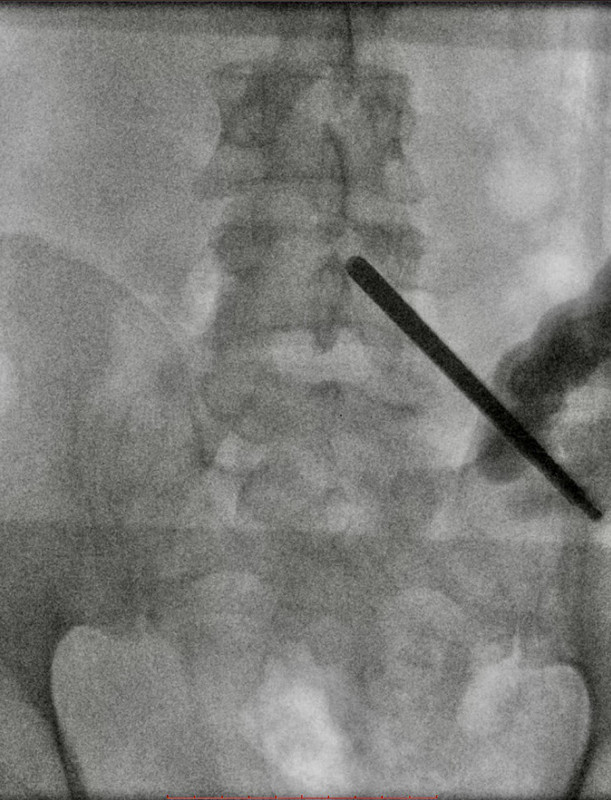
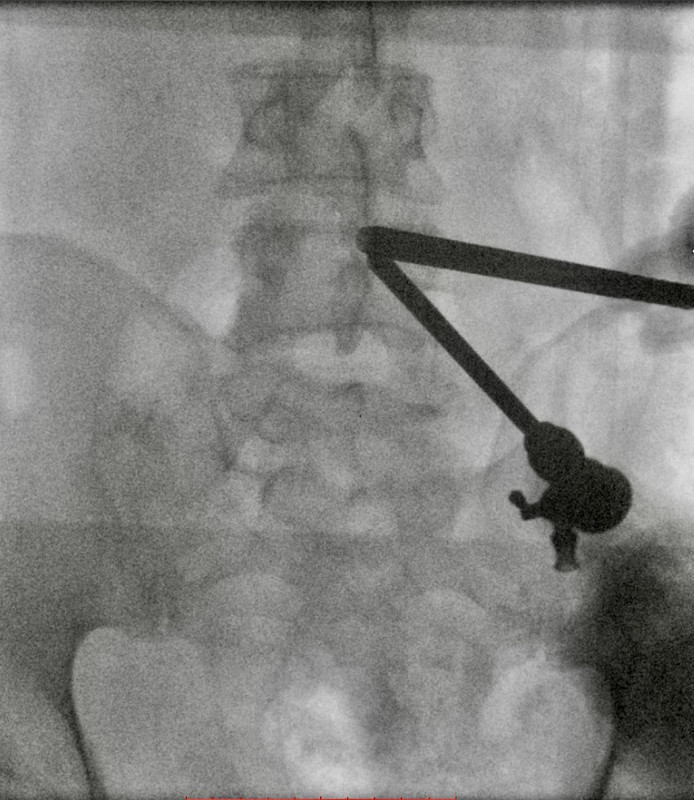
In this case, the primary landmark is the distal lamina of the lower vertebra. With the coagulator in ablation mode, I clearly expose the distal lamina and, laterally, the inferior articular process (IAP) of the upper vertebra and its lamina. In my practice, I remove excess soft tissue with a 5 mm shaver. I continue only when these bony landmarks are clearly visualized.
Bone resection
The extent of bone resection depends on the level of the herniation. At L5–S1, partial resection of the inferior and superior articular processes may be sufficient. Higher levels require more extensive cranial laminar resection, which is ergonomically more difficult on the right: the protective sheath of the cutting burr restricts the view at this angle. In this situation, I may use a high-speed diamond burr without a protective sheath, allowing work laterally and in depth.
I begin by resecting 3–4 mm of the medial IAP until the superior articular process (SAP) of the lower vertebra is visualized. I then move to the lamina of the upper, cranial vertebra. The lamina is usually quite broad, so I remove it in layers: the superficial and middle layers with a burr, and the deep layer with reverse 3–4 mm, 90° Kerrison punches. I can estimate the required extent of resection during fluoroscopic imaging. To provide adequate working space within the spinal canal, I resect the cranial lamina to the level of the inferior endplate of the cranial vertebra.
After cranial laminar resection, I must clearly see the distal lamina transitioning to the superior articular process (3–4 mm), its tip, and the cranial lamina. I then partially resect the medial SAP: using 3–4 mm, 45° Kerrison punches, I create a notch 3–4 mm deep near its base. I continue resection toward the SAP tip with Kerrison punches when experience is limited, or an osteotome when sufficiently proficient in this technique. At this stage, I preserve the ligamentum flavum intact — it protects the contents of the spinal canal.
Resection of the ligamentum flavum and entry into the spinal canal
Next, I partially resect the ligamentum flavum and enter the spinal canal. Its distal edge attaches near the proximal edge of the distal lamina. With 3–4 mm, 45° Kerrison punches, I resect 3–4 mm of the distal lamina to expose the caudal portion of the ligamentum flavum. This window is usually sufficient to insert reverse 3–4 mm, 90° Kerrison punches, with which I carefully remove 4–5 mm of the lateral portion of the ligamentum flavum.
At this stage, I identify the corresponding traversing nerve root. If its lateral edge is not clearly visible enough, I perform additional SAP resection. With limited experience, there is a risk of injuring the nerve root with the elevator at this stage. I aim to visualize the lateral edge of the nerve root and insert the elevator lateral to it.
I then carefully mobilize the nerve root along its length. At this stage, I should already feel or see the herniation. I ensure adequate nerve root mobilization, as inflammation may cause adherence to the disc or ventral structures of the spinal canal.
I place the elevator on the clearly visualized posterior bony surface or disc surface and carefully mobilize the nerve root and dural sac, using only the minimum necessary force and duration. The aim of adhesiolysis is safe mobilization of neural structures and access to the herniated fragment; I avoid unnecessary dissection of adherent neural tissues.
Subsequent stages
I perform the subsequent stages in the same way as for left-sided disc herniation removal.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral biportal endoscopy for lumbar spinal stenosis and lumbar disc herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. doi:10.2106/JBJS.ST.22.00020.
2. Choi CM, Chung JT, Lee SJ, Choi DJ. How I do it? Biportal endoscopic spinal surgery (BESS) for treatment of lumbar spinal stenosis. Acta Neurochir (Wien). 2016;158(3):459–463. doi:10.1007/s00701-015-2670-7.
3. Kim SK, Kang SS, Hong YH, Park SW, Lee SC. Clinical comparison of unilateral biportal endoscopic technique versus open microdiscectomy for single-level lumbar discectomy: a multicenter, retrospective analysis. J Orthop Surg Res. 2018;13(1):22. doi:10.1186/s13018-018-0725-1.
Previous section: 4.9. Features of caudally migrated herniations
Next section: 4.11. Features of herniation removal through a contralateral approach