4. Intracanal lumbar disc herniations
@ProfFishchenkoClinical significance and choice of treatment
Lumbar intervertebral disc herniation is a common cause of radicular leg pain, which may be accompanied by low back pain. The clinical significance of the herniation is determined by concordance between symptoms, neurological examination, and MRI findings; the presence of a herniation on imaging alone is not an indication for surgery.
Discectomy is considered for persistent, clinically significant radicular pain despite appropriate nonsurgical treatment, or for a neurological deficit that warrants surgery. Severe or progressive motor deficit requires urgent assessment of the indications. Suspected cauda equina syndrome requires emergency diagnostic evaluation and MRI and, when compression is confirmed, decompression as soon as possible.
BESS/UBE in my practice
I use BESS/UBE to remove intracanal disc herniations. I select the approach according to the location and migration of the herniation, the anatomy, and the required extent of decompression.
Independent viewing and working portals allow separate control of the endoscope and instruments, adjustment of the viewing angle, and decompression under direct video visualization. BESS/UBE combines minimally invasive soft tissue access with the use of familiar surgical instruments. The anatomical landmarks and principles of decompression are familiar to the surgeon from microsurgical practice, but the endoscopic technique has its own requirements for orientation, irrigation, and instrument control.
In a multicenter randomized study in 2025, biportal endoscopic discectomy for single-level lumbar herniation provided a functional outcome at 12 months comparable to microdiscectomy. The BESS/UBE group had less early pain at the surgical site and better skin scar quality scores.
Illustrations
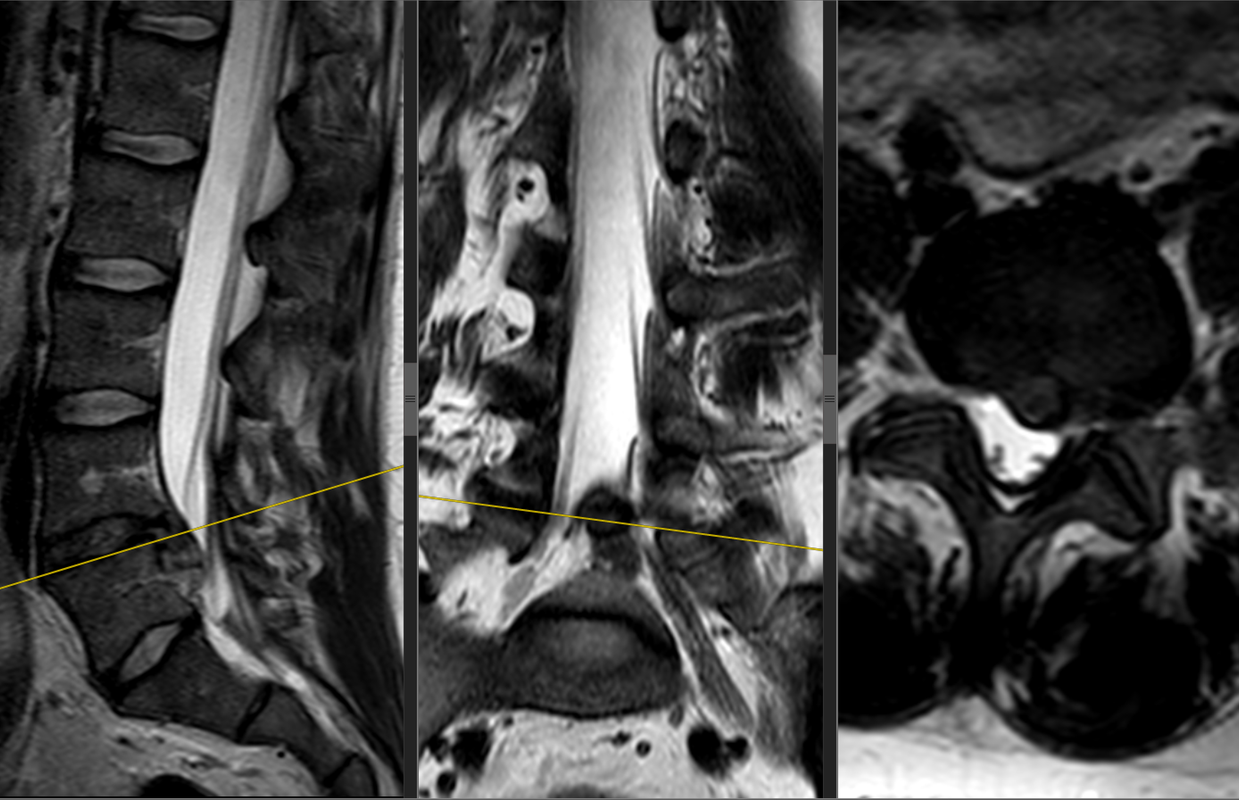
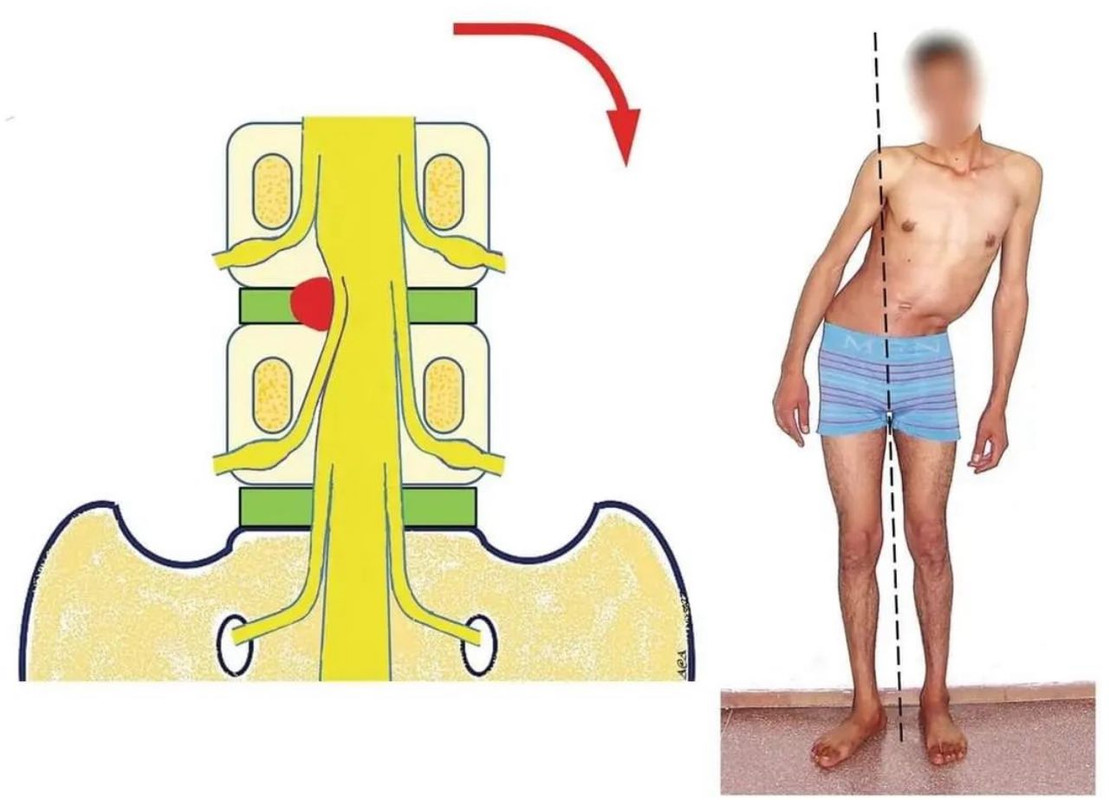
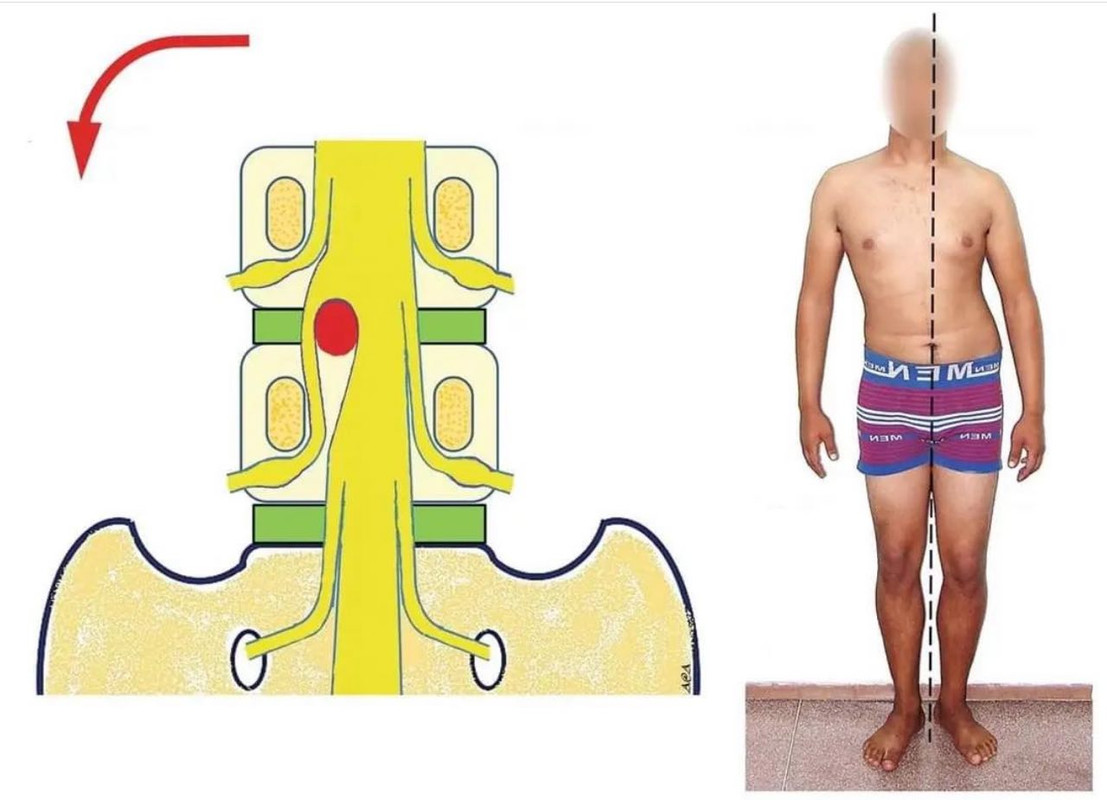
The direction of the antalgic lean may vary and does not, by itself, reliably identify the location of the herniation relative to the nerve root.
References
1. Costa F, Oertel J, Zileli M, Restelli F, Zygourakis CC, Sharif S. Role of surgery in primary lumbar disk herniation: WFNS spine committee recommendations. World Neurosurg X. 2024;22:100276. doi:10.1016/j.wnsx.2024.100276.
2. Vaishya S, Pojskic M, Bedi MS, Oertel J, Sippl C, Robertson S, Zygourakis C. Cauda equina, conus medullaris and syndromes mimicking sciatic pain: WFNS spine committee recommendations. World Neurosurg X. 2024;22:100274. doi:10.1016/j.wnsx.2024.100274.
3. Park SM, Song KS, Ham DW, Kang MS, You KH, Park CK, Kim JS, Park HJ. Comparing the efficacy and safety of biportal endoscopic discectomy with microscopic discectomy for lumbar herniated intervertebral disc: a multicentre, prospective, assessor-blinded, randomized controlled trial. Bone Joint J. 2025;107-B(5):529–539. doi:10.1302/0301-620X.107B5.BJJ-2024-1560.R1.
4. Fardon DF, Williams AL, Dohring EJ, Murtagh FR, Rothman SLG, Sze GK. Lumbar disc nomenclature: version 2.0: recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology and the American Society of Neuroradiology. Spine J. 2014;14(11):2525–2545. doi:10.1016/j.spinee.2014.04.022.
5. Suk KS, Lee HM, Moon SH, Kim NH. Lumbosacral scoliotic list by lumbar disc herniation. Spine (Phila Pa 1976). 2001;26(6):667–671. doi:10.1097/00007632-200103150-00023.
Previous section: 3.2. Spinal anesthesia
Next section: 4.1. Indications and contraindications