2.9. Bone Resection
@ProfFishchenkoPrevious section: 2.8. Clouding of the Operative Field
In my BESS/UBE practice, I determine the extent of bone resection according to the location of compression and the access needed to reach it. My aim is to achieve sufficient decompression while preserving the supporting structures of the spinal segment as much as possible.
Extent of resection for intervertebral disc herniation
The scheme below applies to the interlaminar approach. I determine the size and direction of enlargement of the bony window according to the anatomy of the interlaminar space, the position of the herniation, and the area of neural compression.
For a herniation without substantial migration, a limited laminar window is usually sufficient. If needed, I supplement it with a small resection of the medial edge of the inferior articular process of the upper vertebra and/or the superior articular process of the lower vertebra. I do not consider resection of both articular processes a mandatory step in every discectomy. [1, 2]
For cranial migration of a fragment, I enlarge the window cranially as needed by resecting the caudal edge of the lamina of the upper vertebra. For caudal migration, I direct the enlargement caudally, resecting the necessary portion of the cranial edge of the lamina of the lower vertebra. I tailor the extent of resection to the position of the sequestered fragment and the ability to reach it under direct visualization. These landmarks describe enlargement of the interlaminar window; with substantial migration, the choice of approach and extent of bone resection require a separate assessment. [2, 3]
Extent of resection for central stenosis
For central stenosis, I plan the bone work according to the location of compression in the central canal and lateral recesses. Depending on the anatomy and the required decompression, resection may include the following areas:
- The medial edges of the ipsilateral articular processes: the inferior process of the upper vertebra and the superior process of the lower vertebra.
- The caudal edge of the lamina of the upper vertebra and the cranial edge of the lamina of the lower vertebra.
- The inner portions of the bases of the spinous processes, if needed for access to the opposite side.
- The contralateral portion of the lamina of the upper vertebra and the medial portion of its inferior articular process.
- The contralateral portion of the lamina of the lower vertebra and the medial portion of its superior articular process.
I choose the areas and extent of bone resection according to the decompression required. I aim to preserve the facet joints, pars interarticularis, and other supporting structures of the segment as much as possible. [1, 4]
Instruments and control during bone work
I perform bone resection using a burr, an osteotome, or a combination of the two. Instrument choice depends on the area to be resected, the available working space, and proficiency with the technique. When learning BESS/UBE, I recommend starting with an arthroscopic cutting burr, barrel-shaped or round, 4–5 mm in diameter.
I work under clear endoscopic visualization, maintaining a view of the working part of the instrument and the anatomical landmarks. During the relevant bone work, I preserve the deep layer of the ligamentum flavum as a protective barrier for the neural structures when the anatomy and sequence of decompression allow. If the conditions of the approach change, I reassess protection of the neural structures and instrument choice; if visibility is lost, I stop resection until visual control is restored. [1, 5]
When using the burr, the position of the free edge of the ligamentum flavum should be monitored. The rotating burr head can catch the detached ligament and wind it together with the adjacent dura mater, causing a dural tear. In the foraminal region, the exiting nerve root and adjacent vessels are kept clear of the rotating part of the instrument [6, 7].
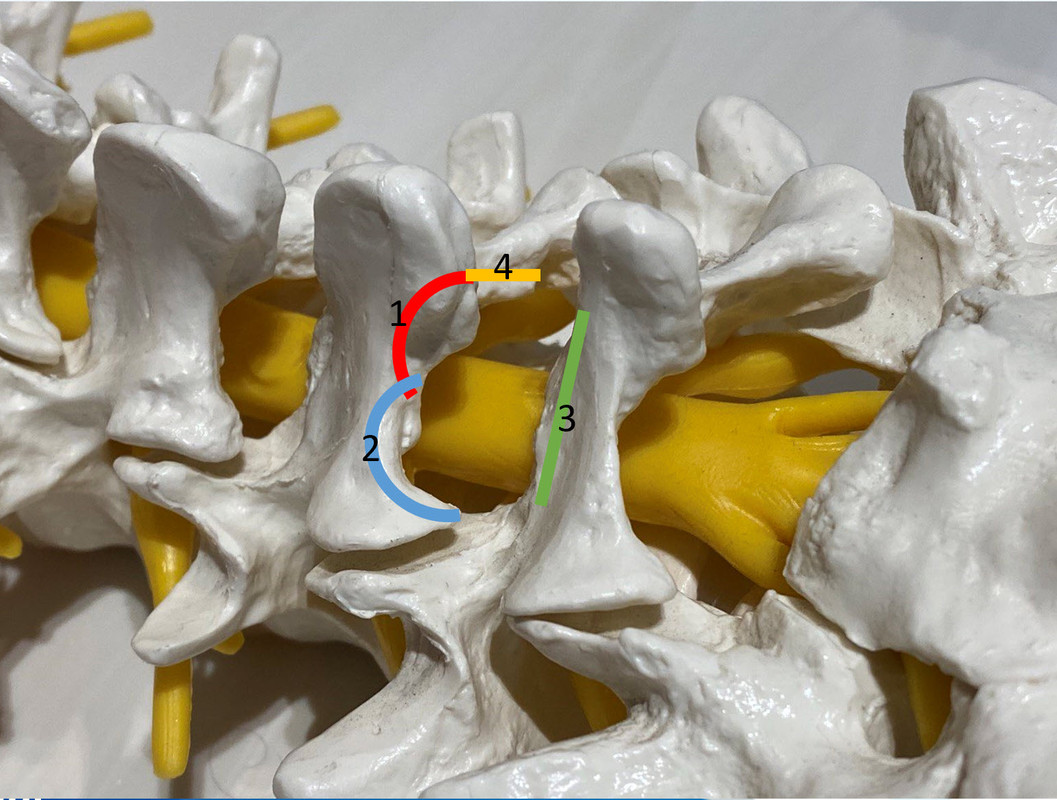
1 (red)—base of the cranial spinous process.
2 (blue)—cranial lamina and inferior articular process.
3 (green)—distal lamina and base of the distal spinous process.
4 (yellow)—contralateral lamina and inferior articular process.
References
1. Park J, Ahn DK, Choi DJ. Treatment Concept and Technical Considerations of Biportal Endoscopic Spine Surgery for Lumbar Spinal Stenosis. Asian Spine J. 2024;18(2):301–323. doi:10.31616/asj.2023.0409.
2. Chen WC, Wang WT, Pao JL. Unilateral biportal endoscopic discectomy via translaminar approach for highly upward-migrated lumbar disc herniation: a technical note and preliminary treatment outcomes. BMC Musculoskelet Disord. 2024;25:722. doi:10.1186/s12891-024-07819-x.
3. Cheng W, Gao W, Zhu C, Shao R, Wang D, Pan H, Zhang W. Contralateral translaminar endoscopic approach for highly down-migrated lumbar disc herniation using percutaneous biportal endoscopic surgery. BMC Surg. 2024;24:58. doi:10.1186/s12893-024-02348-9.
4. Ahuja S, Moideen AN, Dudhniwala AG, Karatsis E, Papadakis L, Varitis E. Lumbar stability following graded unilateral and bilateral facetectomy: A finite element model study. Clin Biomech (Bristol, Avon). 2020;75:105011. doi:10.1016/j.clinbiomech.2020.105011.
5. Pao JL, Chang CC. A Comparative Study of the No-Punch Technique in Reducing Surgical Complications Associated with Unilateral Biportal Endoscopic Spine Surgery. J Clin Med. 2025;14(20):7295. doi:10.3390/jcm14207295.
6. Kim J.Y., Eum J.H., Park C.K. Unilateral Biportal Endoscopy for Cervical Decompressive Laminectomy. In: Unilateral Biportal Endoscopic Spine Surgery: Basic and Advanced Technique. Springer; 2022. P. 201–212; relevant passage: p. 210. Book chapter.
7. Kim J.Y., Heo D.H., Hong H.J., Park C.W. Unilateral Biportal Endoscopy for Decompression of Foraminal (Extraforaminal) Stenosis Through the Contralateral Sublaminar Approach. In: Unilateral Biportal Endoscopic Spine Surgery: Basic and Advanced Technique. Springer; 2022. P. 101–120; relevant passage: p. 102. Book chapter.
Previous section: 2.8. Clouding of the Operative Field
Next section: 2.10. Disc Curettage