2.6. Hemostasis
@ProfFishchenkoPrevious section: 2.5. Spatial Orientation (Clock Face)
In BESS/UBE, I choose the method of hemostasis according to the source of bleeding: soft tissues, a bone surface, or epidural vessels.
Radiofrequency generator
I use a radiofrequency (RF) generator to coagulate soft tissue vessels in coagulation mode and remove fragments of loosened soft tissue in ablation mode.
Before surgery, I always familiarize myself with the modes and settings of my radiofrequency generator.
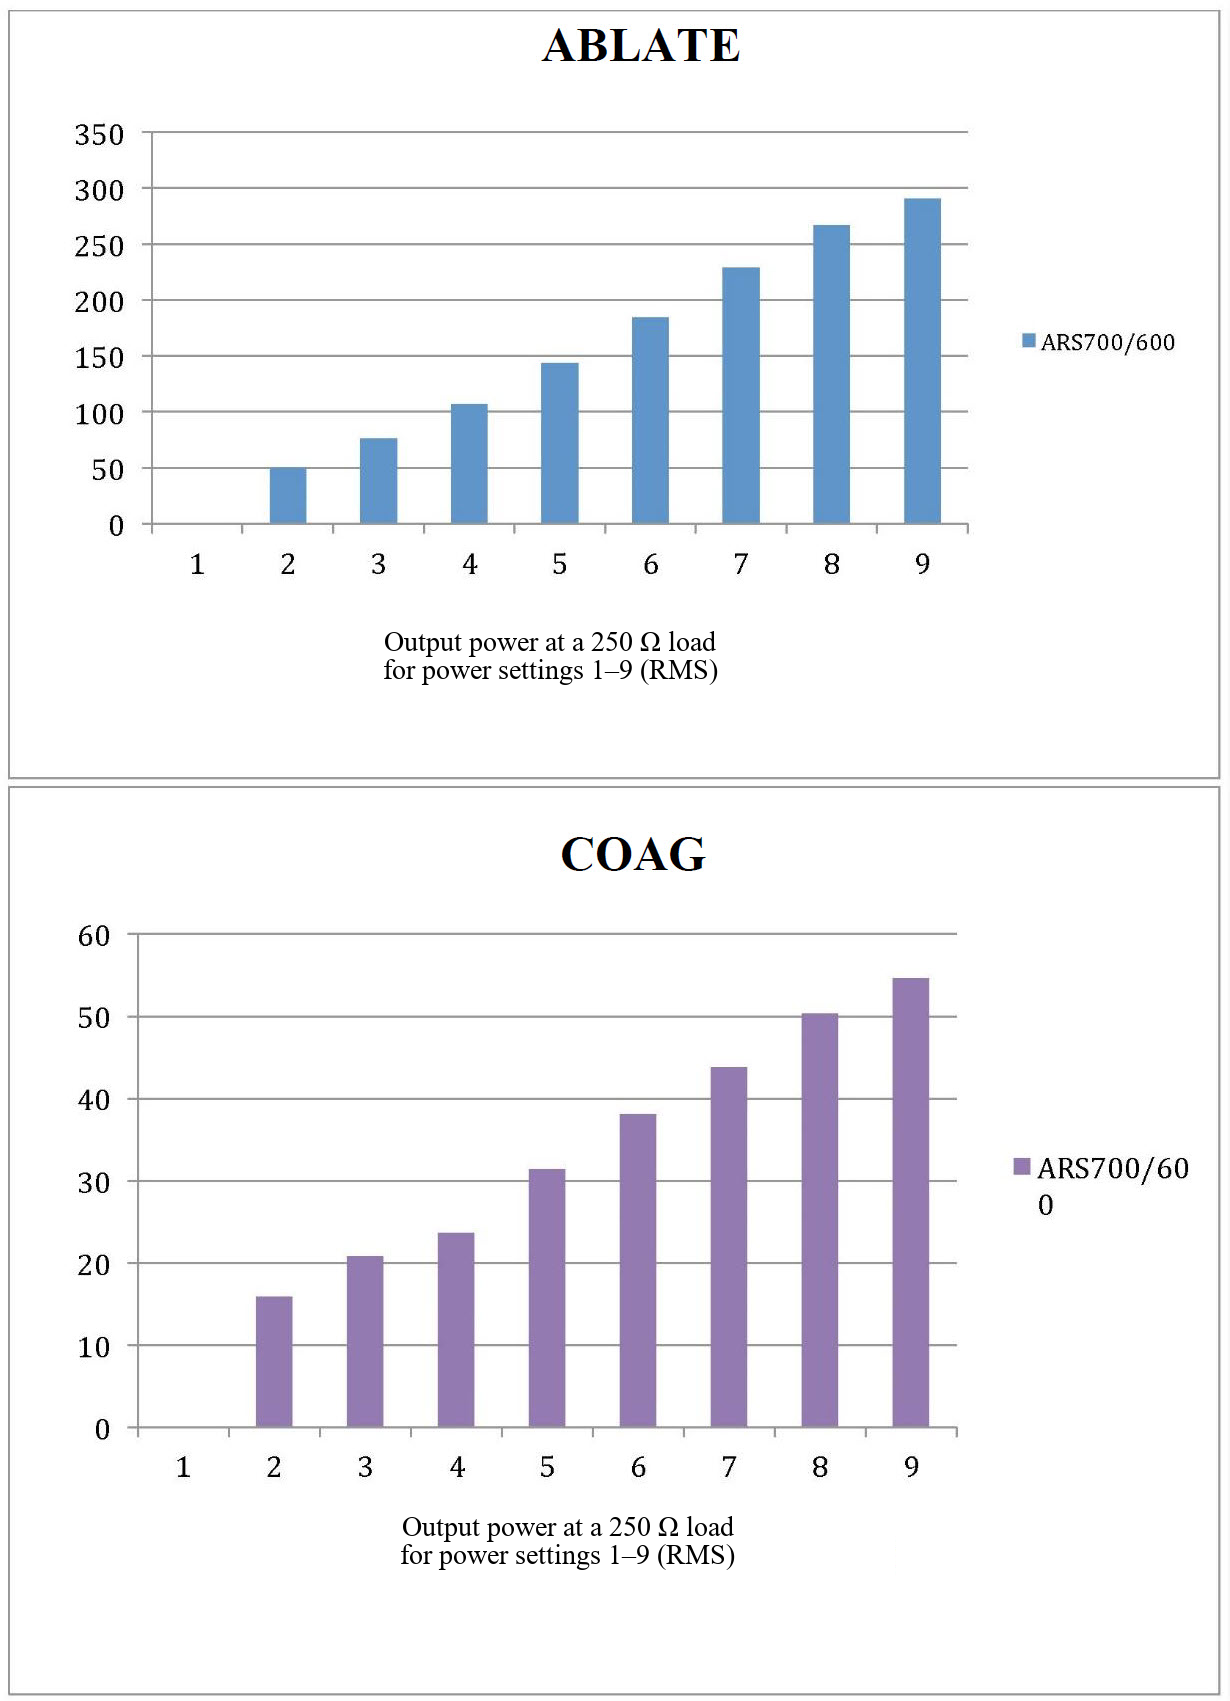
In my practice, I use a BONSS ARS600 radiofrequency generator with a disposable RF electrode. My usual working settings are ABLATE 7 and COAG 3. When working near the dura mater or a nerve root, I do not activate ABLATE mode; I perform coagulation at COAG 2. I always orient the back of the electrode toward the neural structures. These are setting levels on the ARS600 scale, not power values in watts.
I activate the electrode only under direct endoscopic visualization with continuous irrigation and free outflow. If coagulation beneath a nerve root is required, I use a separate inactive instrument to protect and gently mobilize it. The activated RF electrode must contact only the tissue to be coagulated.
Coagulation electrodes


I use RF electrodes with a 5 mm working tip for debridement and coagulation outside the spinal canal.

I use a curved RF electrode with a 1.5 mm working tip to coagulate small vessels in the spinal canal near the dural sac.
Bone wax
I control bleeding from cancellous bone using surgical wax. After warming the wax in my hands, I place a small piece on the tip of an elevator. I bring the elevator with the wax to the site of bone bleeding and apply the wax to the bone. I rub the wax into the bone using the elevator or the back of the coagulation electrode.
Hemostatic sponge
After removal of the ligamentum flavum, bleeding from epidural vessels may impair visibility in the spinal canal. In addition to visible vessels, which I coagulate using an RF electrode with a 5 mm working tip (COAG 2 near the dura mater or a nerve root), bleeding may arise from beneath the cranial or caudal lamina. To control it, I may place a small piece of Surgicel hemostatic material beneath the lamina and wait a few minutes.
Coordination with the anesthesiologist
I assess blood pressure and the degree of muscle relaxation together with the anesthesiologist. If visibility suddenly deteriorates, I stop active manipulation, check the source of bleeding, and verify free saline outflow. I do not compensate for impaired outflow by increasing irrigation pressure.
Final hemostasis check
Before completing the operation, I reinspect the epidural vessels and the edges of the resected bone with hydrostatic tamponade reduced. The absence of bleeding at the working irrigation pressure does not yet indicate definitive hemostasis.
References
1. Park DK, Weng C, Zakko P, Choi DJ. Unilateral Biportal Endoscopy for Lumbar Spinal Stenosis and Lumbar Disc Herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020. DOI: 10.2106/JBJS.ST.22.00020.
2. Choi CM, Chung JT, Lee SJ, Choi DJ. How I do it? Biportal endoscopic spinal surgery (BESS) for treatment of lumbar spinal stenosis. Acta Neurochir (Wien). 2016;158(3):459–463. DOI: 10.1007/s00701-015-2670-7.
3. Ahn DK, Lee JS, Shin WS, Kim S, Jung J. Postoperative spinal epidural hematoma in a biportal endoscopic spine surgery. Medicine (Baltimore). 2021;100(6):e24685. DOI: 10.1097/MD.0000000000024685.
4. Choi CM. Biportal endoscopic spine surgery (BESS): considering merits and pitfalls. J Spine Surg. 2020;6(2):457–465. DOI: 10.21037/jss.2019.09.29.
5. Heo DH, Park DY, Hong YH, Kim D, Kim JS. Temperature change of epidural space by radiofrequency use in biportal endoscopic lumbar surgery: safety evaluation of radiofrequency. Eur Spine J. 2023;32(8):2769–2775. DOI: 10.1007/s00586-023-07719-z.
6. Ham DW, Lee J, Kwon BT, Yoo Y, Park SM, Song KS. Comparison of Postoperative Epidural Hematoma Formation Between Biportal Endoscopic Spine Surgery and Conventional Microscopic Surgery: A Randomized Controlled Trial. Int J Spine Surg. 2024;18(5):533–539. DOI: 10.14444/8578.
Previous section: 2.5. Spatial Orientation (Clock Face)
Next section: 2.7. Creating the Working Space