2.11. Drainage
@ProfFishchenkoPrevious section: 2.10. Disc Curettage
After lumbar BESS/UBE decompression or discectomy, I use drainage to evacuate residual irrigation fluid and wound discharge.
A drain does not replace meticulous hemostasis and postoperative observation. A hematoma seen on MRI and a clinically significant hematoma compressing neural structures are not the same.
Drain placement
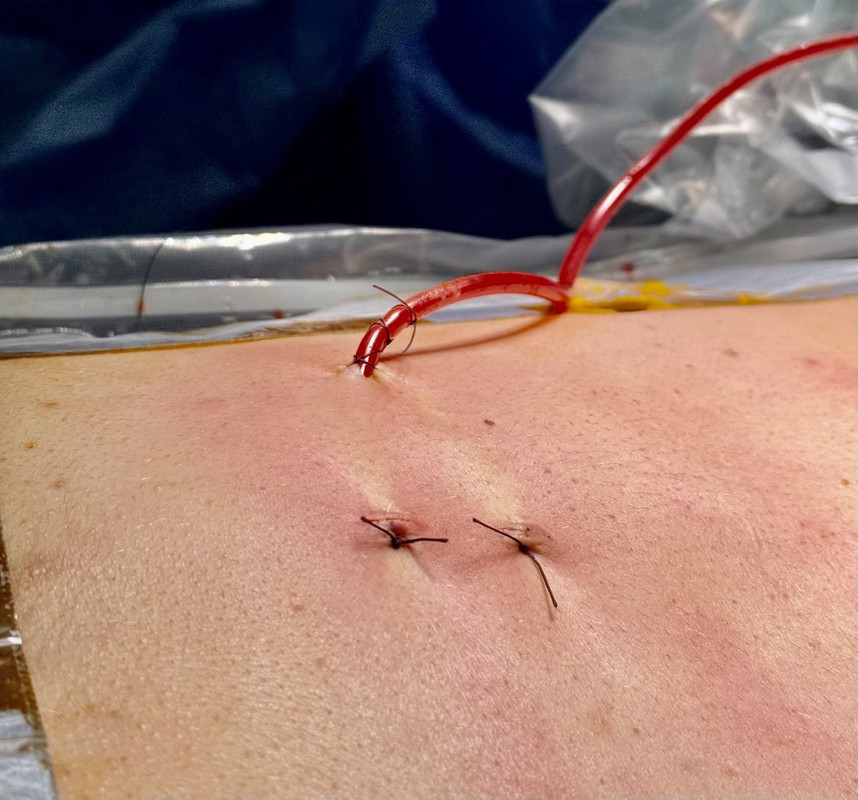
I place a No. 15 drain tube in the operative cavity created and bring it out through the working portal or a separate stab incision. I secure the drain to the skin with Vicryl 2-0 suture.
Observation and drain removal
In my practice, I remove the drain the day after surgery. If there are signs of drain-related irritation of neural structures, I remove it immediately, without waiting for the scheduled time.
Irritation of neural structures may be related both to direct contact with the drain tube and to the negative pressure generated by the drainage system.
If new severe pain develops, I also assess neurological status. Increasing pain, leg weakness, or bladder or bowel dysfunction require urgent exclusion of a compressive hematoma; removing the drain does not replace diagnostic evaluation and the necessary treatment.
When I do not leave a drain
In my practice, I do not leave a wound drain after cervical BESS procedures or BELIF/UBE-LIF.
I also do not leave a wound drain if an intraoperative dural injury occurs. I assess the defect, ensure secure closure using an appropriate method, and carefully close the wound. Tight skin closure alone does not replace management of cerebrospinal fluid leakage. I determine the strategy according to the nature of the injury and the reliability of defect closure.
References
1. Zhong Z, Ying J, Zhang S, Cai K, Jing X, Xu Z, Jiang L, Wu T, Wei G, Hu Q. Does the number of drain tubes influence the formation of postoperative spinal epidural hematoma following biportal endoscopic unilateral laminotomy for bilateral decompression (BE-ULBD) in patients with two-level adjacent lumbar spinal stenosis? a prospective randomized study. J Orthop Surg Res. 2025;20(1):615. doi:10.1186/s13018-025-06042-1.
2. Ham DW, Lee J, Kwon BT, Yoo Y, Park SM, Song KS. Comparison of Postoperative Epidural Hematoma Formation Between Biportal Endoscopic Spine Surgery and Conventional Microscopic Surgery: A Randomized Controlled Trial. Int J Spine Surg. 2024;18(5):533–539. doi:10.14444/8578.
3. Verghese NP, Altunbi B, Ashaolu O. Suction-induced intradural nerve root kinking following lumbar decompression: A rare mechanical complication with radiographic resolution. Surg Neurol Int. 2025;16:456. Case report. doi:10.25259/SNI_1022_2025.
4. Kim JE, Choi DJ, Park EJ. Risk Factors and Options of Management for an Incidental Dural Tear in Biportal Endoscopic Spine Surgery. Asian Spine J. 2020;14(6):790–800. doi:10.31616/asj.2019.0297.
5. Lee HG, Kang MS, Kim SY, Cho KC, Na YC, Cho JM, Jin BH. Dural Injury in Unilateral Biportal Endoscopic Spinal Surgery. Global Spine J. 2021;11(6):845–851. doi:10.1177/2192568220941446.
Previous section: 2.10. Disc Curettage
Next chapter: 3. Anesthetic Management