17.4. Postoperative Imaging: Correlation with the Clinical Presentation
@ProfFishchenkoPostoperative imaging supplements but does not replace clinical examination. We assess images in the context of the procedure performed, intraoperative features, the time since surgery, and the evolution of symptoms. It is important to establish both the presence of a particular change and whether it explains the patient's condition.
Routine monitoring in our practice
The day after surgery, we routinely perform:
• after BESS/UBE decompression or discectomy—follow-up MRI;
• after BELIF/UBE-LIF—follow-up CT.
This is our routine postoperative monitoring protocol, which we apply even in the absence of symptoms. The study allows assessment of postoperative anatomy and provides baseline images for subsequent comparison.
If new neurological symptoms develop, we perform imaging urgently.
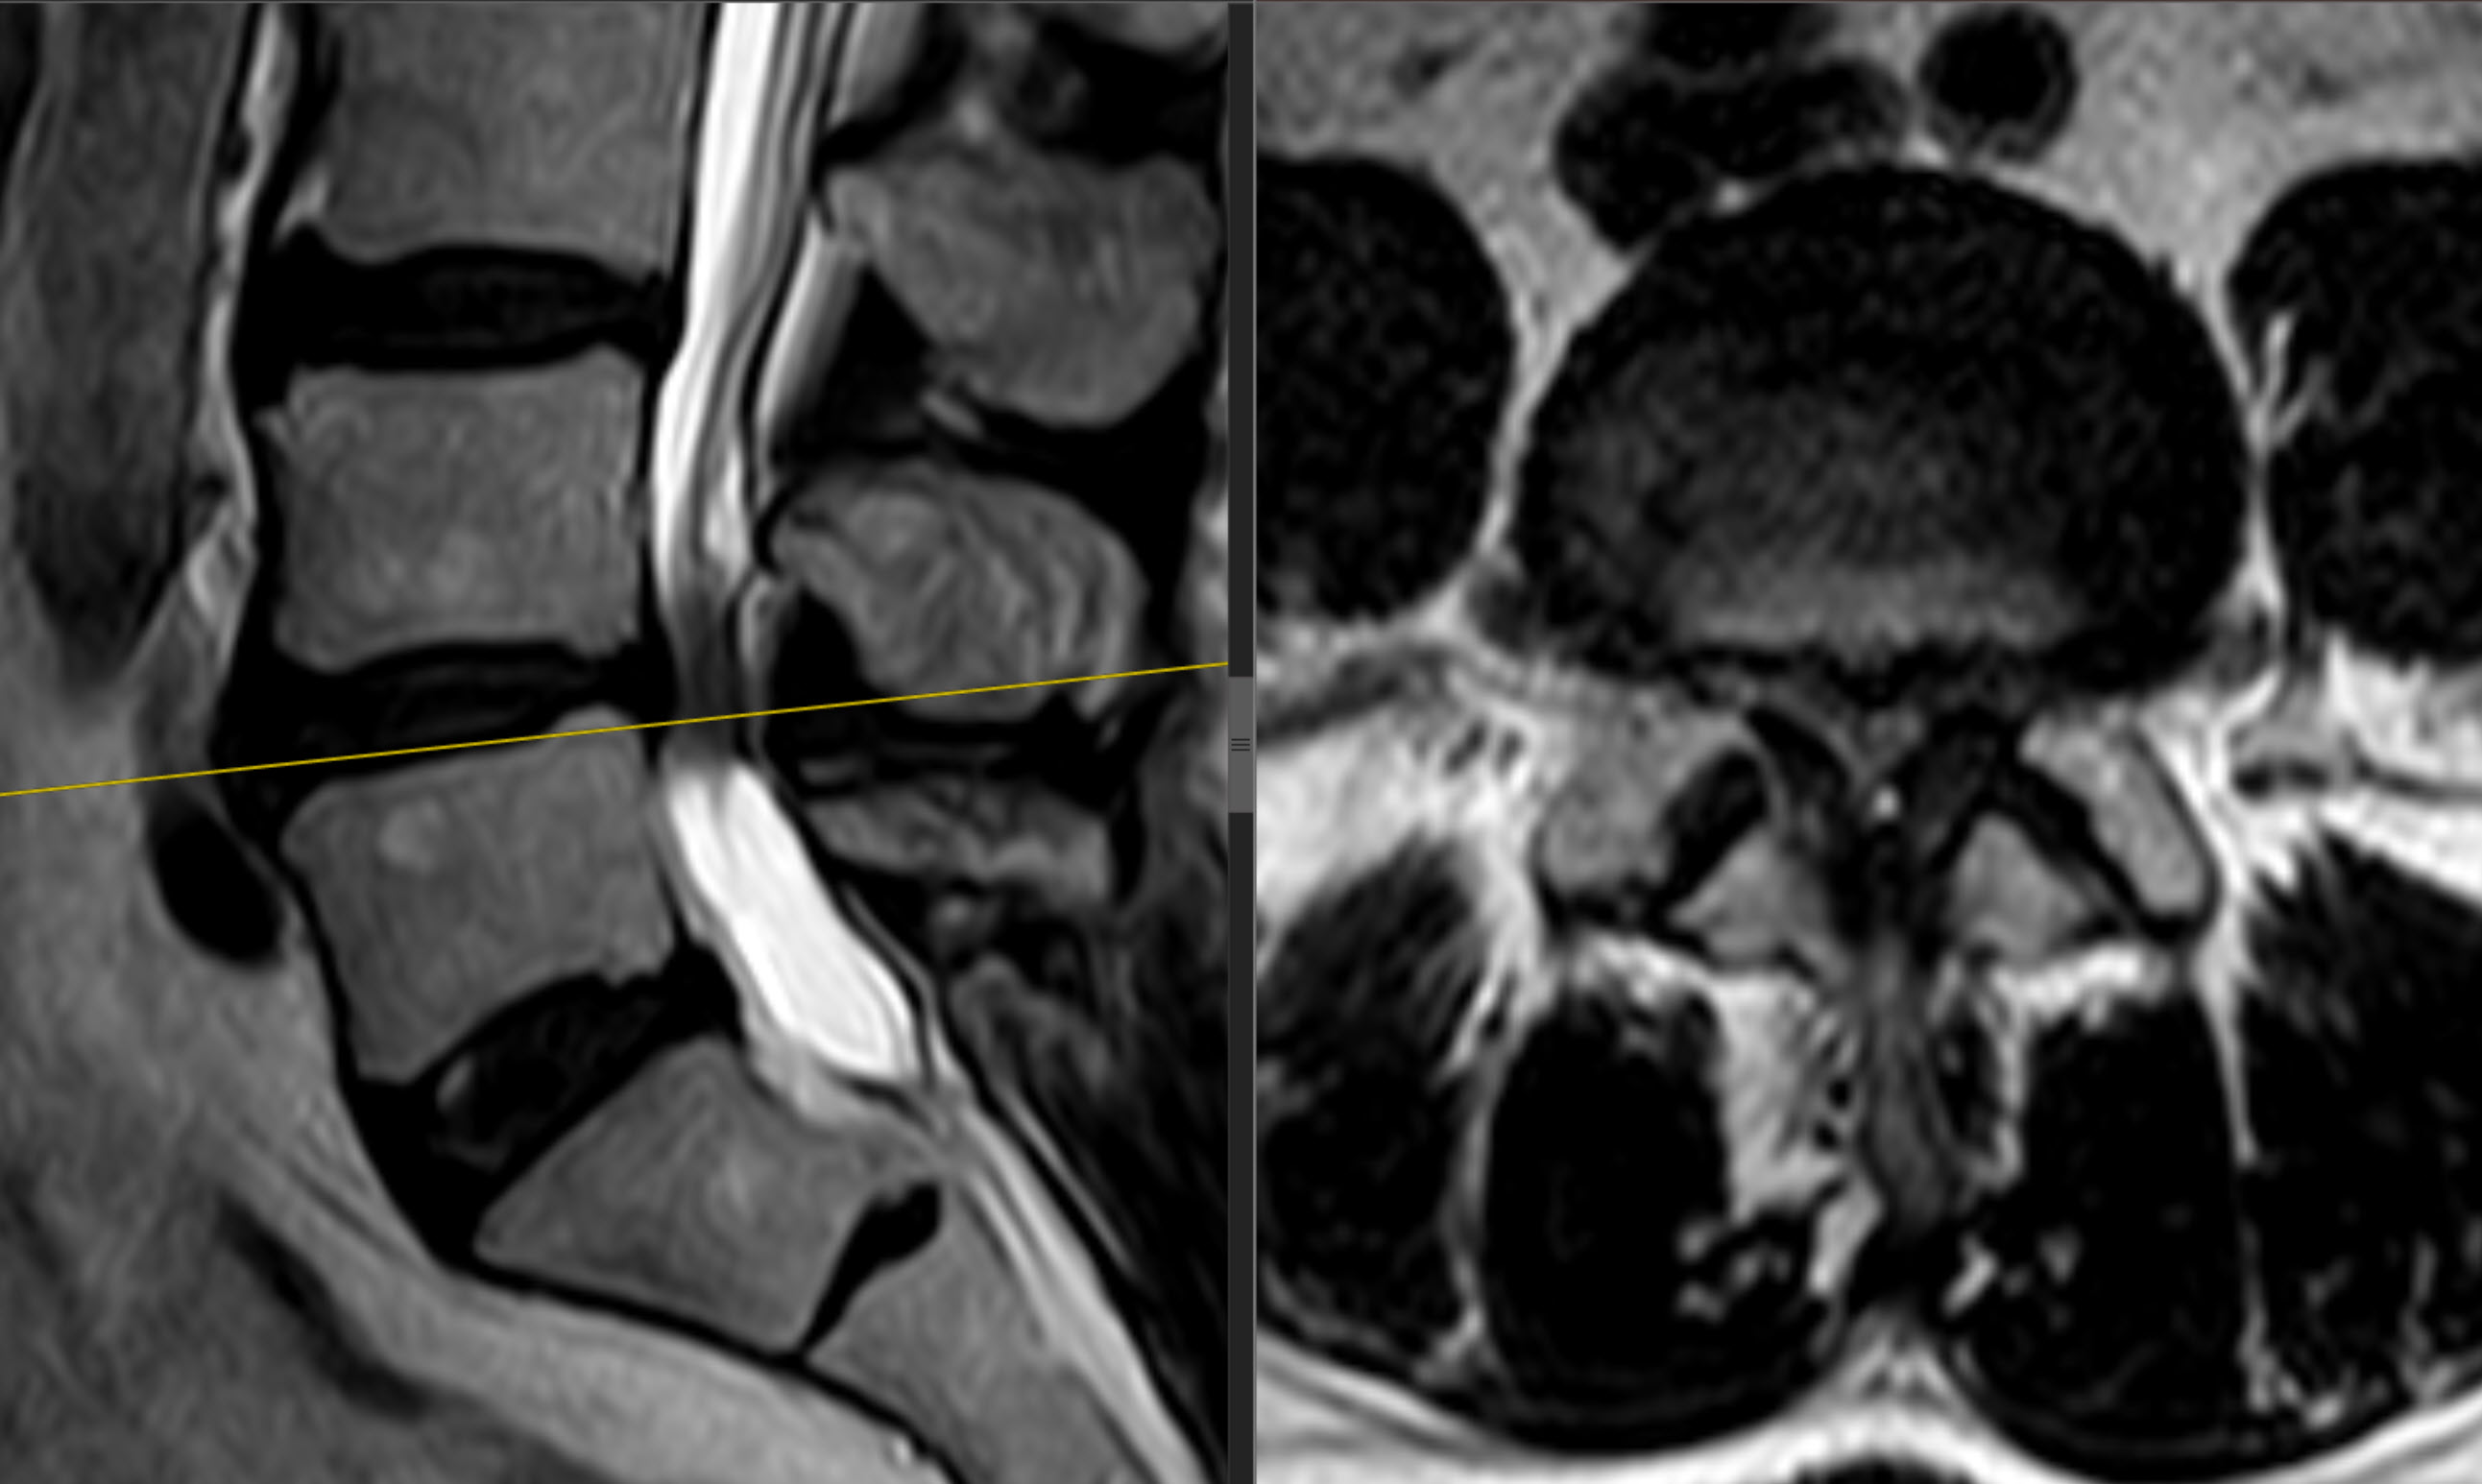
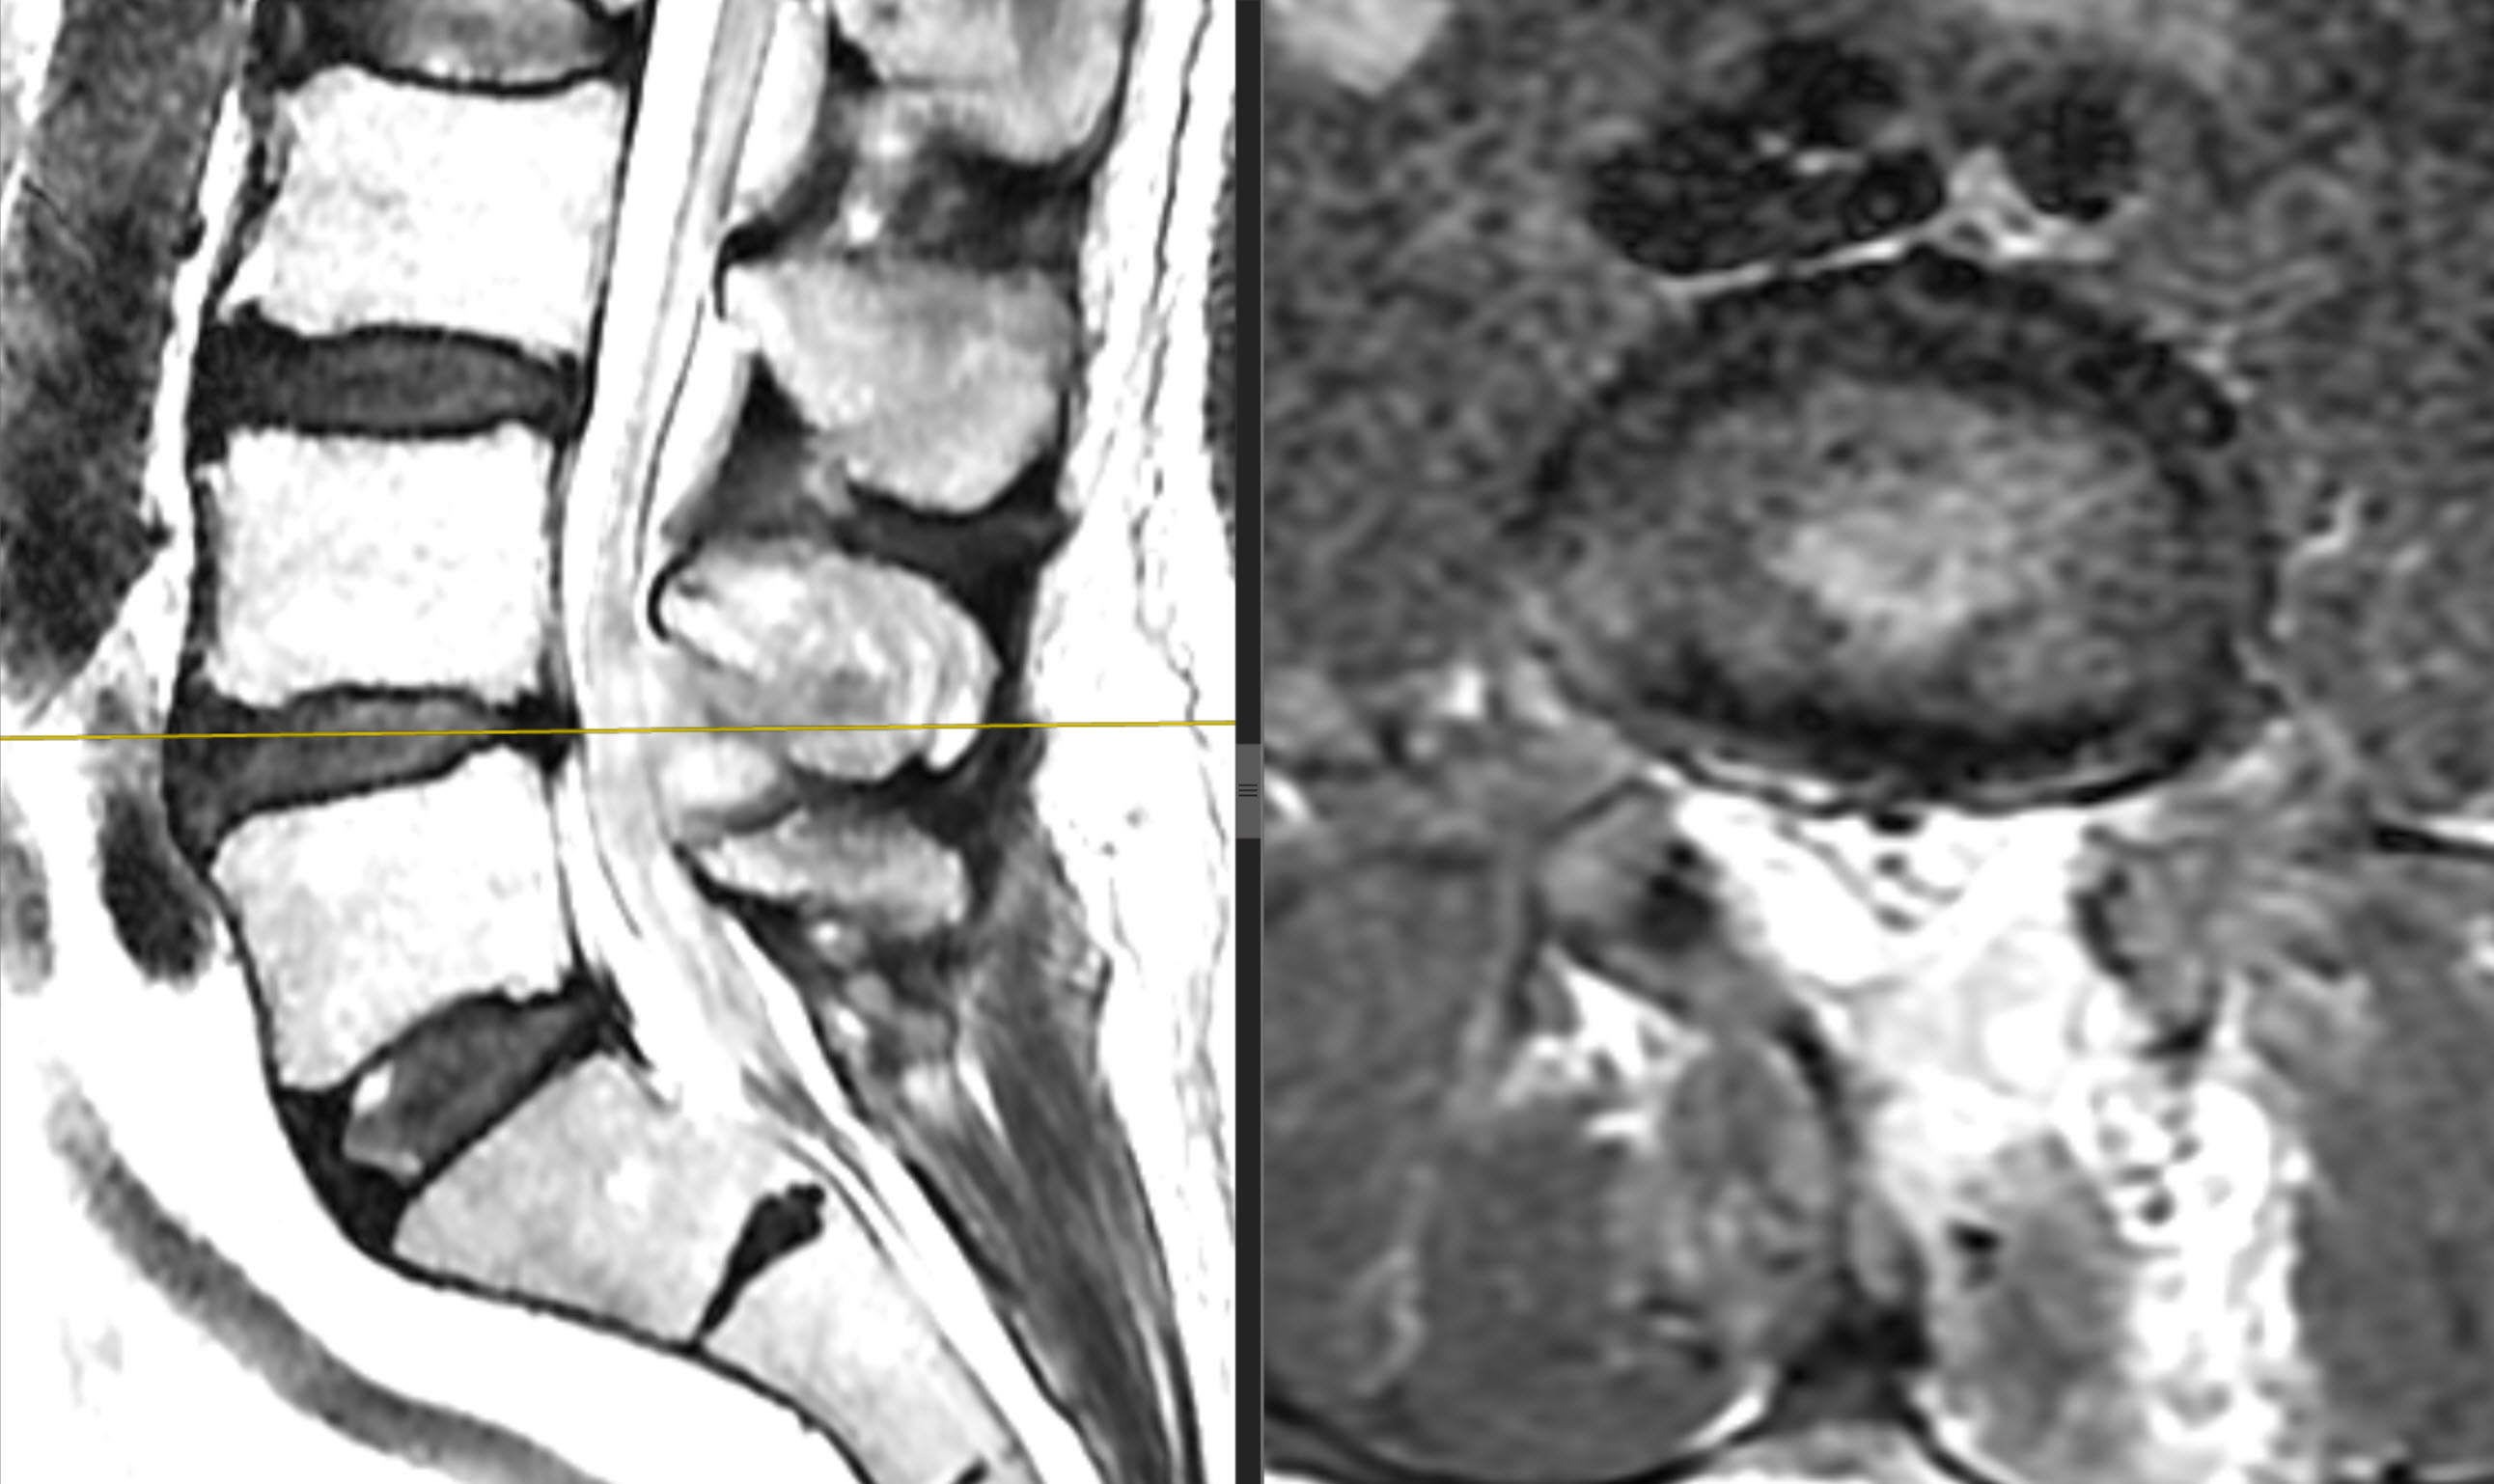
MRI after decompression and discectomy
Our postoperative MRI protocol
The lumbar spine magnetic resonance imaging protocol included localizer scanning in three mutually perpendicular planes, acquisition of T2-weighted fast spin-echo images in the sagittal and coronal planes, and fat-suppressed images using the STIR sequence in the sagittal and oblique axial planes. Additional volumetric scanning was performed using a three-dimensional T2-weighted fast spin-echo sequence with axial orientation of the acquisition block. Slice thickness was 4 mm for the coronal T2-weighted series, 3.5 mm for the sagittal T2-weighted and STIR series and the axial STIR series, and 1.29 mm for the three-dimensional T2-weighted series.
We compare postoperative and preoperative images, considering the level, side, and planned decompression area. The main questions are:
• has compression of neural structures in the operative area been relieved;
• does a component remain that may explain persistent or new symptoms;
• is there an epidural blood collection or another lesion exerting a compressive effect;
• do the location and side of the changes identified correspond to the clinical manifestations?
Early postoperative MRI does not always resemble a “normal spine.” Tissue changes in the operative area may create a mass effect and complicate interpretation.
In a prospective study by Weber et al. after clinically successful microdiscectomy, early postoperative changes producing a mass effect, sometimes with nerve root displacement or compression, were common and subsequently diminished. These changes are assessed together with the symptoms and their evolution. A new neurological deficit requires urgent assessment. Weber et al., 2016.
It is likewise necessary to distinguish a hematoma identified on MRI from a symptomatic compressive hematoma. In a study of 158 patients after single-level BESS decompression, hematoma was identified in 39, and two underwent revision for associated symptoms. Decisions about further management depend on symptoms, their evolution, and the nature of compression. Kim et al., 2019.
CT after BELIF/UBE-LIF
Our CT scanning protocol
Lumbar spine computed tomography was performed in helical mode after obtaining scout images in two orthogonal projections. The X-ray tube voltage was 140 kV, helical pitch was 0.6, and rotation time was 1 s. Axial images were reconstructed with a slice thickness of 1 mm and a reconstruction interval of 0.5 mm, with separate series for assessment of bone and soft tissues. A metal artifact correction algorithm was used to reduce metal artifacts. Images were displayed in bone and soft tissue windows.
On follow-up CT, we assess the position of the cage and fixation components and their relationship to bony structures, the spinal canal, and intervertebral foramina. We pay particular attention to possible screw malposition beyond the pedicles, cage positioning, and endplate integrity.

CT depicts bony structures and the instrumentation well, but it does not replace MRI when the main question concerns a postoperative blood collection or neural compression. The modality is selected according to the diagnostic question. ACR Appropriateness Criteria.
CT on the day after surgery assesses the result of instrumentation placement. Assessment of spinal fusion belongs to later follow-up at 12+ months. For example, in Pao's study of biportal endoscopic interbody fusion, the degree of fusion was determined by CT one year after surgery. Pao, 2023.
Radiography may supplement assessment of changes in the relative positioning of vertebrae and instrumentation over time, but it does not replace MRI when neural compression is suspected.
When imaging is required before routine monitoring
New or increasing muscle weakness, bladder or bowel dysfunction, or other signs of acute neurological deterioration require immediate examination by the surgeon and determination of further actions.
When postoperative epidural hematoma is suspected, urgent MRI is the modality of choice for assessing neural structures and the degree of compression. In severe, rapidly progressing deterioration, waiting for imaging must not delay necessary surgical revision; the surgical team makes the decision according to the clinical situation. Consensus of the Belgian Society of Neurosurgery, 2024.
This rule also applies to patients after BELIF/UBE-LIF: scheduled CT does not exclude the need for urgent MRI when relevant symptoms are present. Detailed management is discussed in the section “Epidural Hematoma”.
How we correlate images with the clinical outcome
When jointly analyzing clinical data and images, we answer three questions:
1. Does the finding correspond to the symptoms? We consider the level, side, area of sensory disturbance, and nature of the motor deficit.
2. How is the condition evolving? We distinguish persistent preoperative manifestations from new or progressive ones.
3. Does the finding change management? We determine the need for observation, additional imaging, or urgent intervention.
If the images do not explain deterioration, we reassess neurological status and review the study with the radiologist.
In the documentation, we record both the MRI or CT description and its clinical significance and the decision made.
Practical principle: we determine treatment from the combined clinical and imaging findings, rather than an isolated phrase in the radiology report.
References
1. Weber C, Kvistad KA, Moholdt VA, Nygaard ØP, Solheim O. Repeated 3.0 Tesla Magnetic Resonance Imaging After Clinically Successful Lumbar Disc Surgery. Spine. 2016;41(3):239–245. DOI: 10.1097/BRS.0000000000001189.
2. Kim JE, Choi DJ, Park EJ. Evaluation of Postoperative Spinal Epidural Hematoma After Biportal Endoscopic Spine Surgery for Single-Level Lumbar Spinal Stenosis: Clinical and Magnetic Resonance Imaging Study. World Neurosurgery. 2019;126–e792. DOI: 10.1016/j.wneu.2019.02.150.
3. Pao JL. Biportal Endoscopic Transforaminal Lumbar Interbody Fusion Using Double Cages: Surgical Techniques and Treatment Outcomes. Neurospine. 2023;20(1):80–91. Full text.
4. Hutchins TA, et al. ACR Appropriateness Criteria® Low Back Pain: 2021 Update. Journal of the American College of Radiology. 2021;18(11S)–S379. ACR recommendations.
5. Smeijers S, et al. Consensus statement by the Belgian Society of Neurosurgery and literature review on the diagnosis and management of postoperative spinal epidural hematoma. Brain and Spine. 2024;4:103904. Full text.
Previous subsection: 17.3. Wound Examination and Drain Monitoring
Next subsection: 17.5. Further Follow-up and Outcome Assessment
Chapter 17. Postoperative Period