13.3. Planning
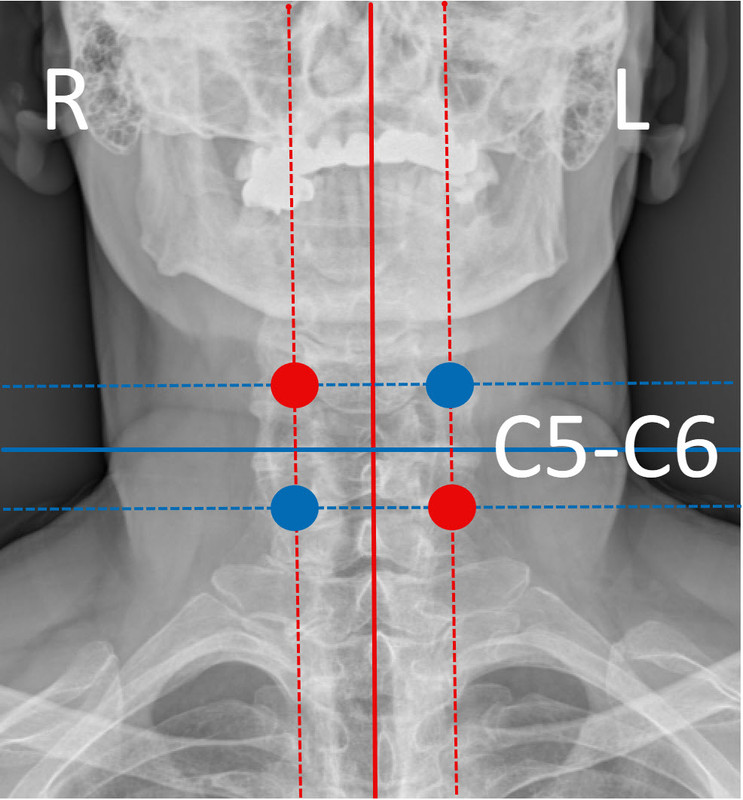
@ProfFishchenkoPlanning the approach using C5–C6 as an example
To plan the approach, we mark the landmarks:
• the midline — red;
• a parallel line 1–1.5 cm lateral to it — dashed red;
• a perpendicular line at the target intervertebral level — blue;
• a line parallel to the latter, 1–1.5 cm away — dashed blue.
We plan the incisions at the intersections of the corresponding lines.
For a left-sided approach, we use the cranial portal for the endoscope and the caudal portal as the working portal.
For a right-sided approach, the arrangement is reversed: the endoscopic portal is caudal and the working portal is cranial.
References
1. Kim JY, Kim DH, Lee YJ, Jeon JB, Choi SY, Kim HS, et al. Anatomical importance between neural structure and bony landmark: clinical importance for posterior endoscopic cervical foraminotomy. Neurospine. 2021;18(1):139–146. DOI: 10.14245/ns.2040440.220.
2. Heo DH. Biportal endoscopic posterior cervical foraminotomy with discectomy for unilateral radicular arm pain due to cervical herniated disc. Neurosurg Focus Video. 2024;10(2):V12. DOI: 10.3171/2024.1.FOCVID23225.
3. Heo DH, Ha JS, Jang JW. Biportal endoscopic posterior cervical foraminotomy for adjacent 2-level foraminal lesions using a single approach (sliding technique). Neurospine. 2023;20(1):92–98. DOI: 10.14245/ns.2346144.072.
Previous section: 13.2. Equipment and instruments