10.3. Surgical Approach
@ProfFishchenkoDuring planning, we obtain CT in addition to MRI and identify the structures compressing the L5 spinal nerve. We plan the extent of their resection in advance.
We position the patient prone on a Wilson frame to provide lumbar flexion. We coordinate head and trunk positioning with the anesthesiologist to maintain ventilation and venous outflow. We keep the neck neutral and avoid pressure on the eyes and abdomen. The anesthesiologist determines the target blood pressure individually; in our practice, we use a systolic pressure of approximately 100 mmHg only when clinically appropriate. We place soft pads beneath the knees and lower legs.
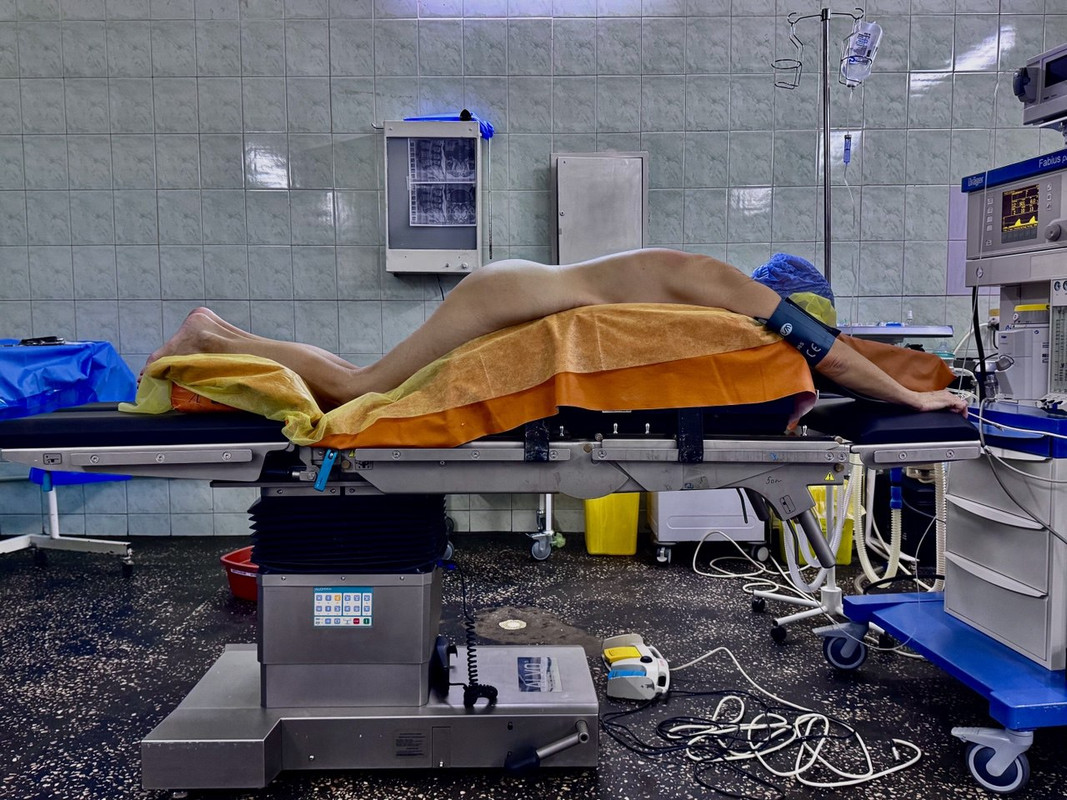
We confirm the operative level using the C-arm before making the incision, correlating vertebral numbering with the preoperative images. We obtain a lateral view whenever there is uncertainty about the level or instrument depth, particularly in lumbarization, sacralization, or hyperlordosis. We perform an additional lateral check while placing the trocar and dilators into the working portal if necessary.
Left-Sided Approach
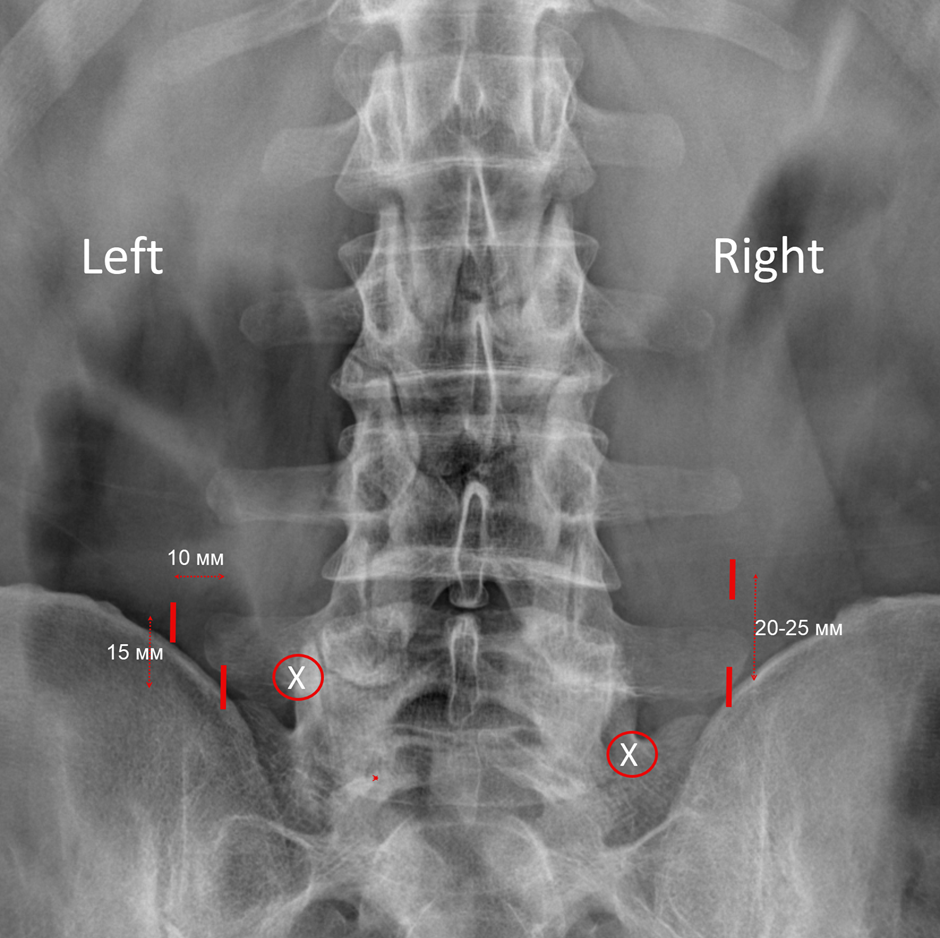
For a right-handed surgeon, the left-sided approach is technically the most difficult. The iliac crest limits lateral displacement from the lateral pedicle line and instrument manipulation. We therefore carefully plan the incisions and the endoscopic and working portals from the outset.
We project the endoscopic portal incision onto the edge of the slope of the iliac crest, at the level of the proximal border of the L5 transverse process. From the center of the incision, we move 15 mm distally and 10 mm medially — this is the center of the working portal incision.
The instrument convergence point is the distal portion of the junction between the base of the transverse process and the lamina of L5.
Right-Sided Approach
In a right-sided L5–S1 approach, the iliac crest may also limit the lateral trajectory and instrument movement. Accurate initial positioning of the endoscopic and working portals is essential.
We project the endoscopic portal incision onto the edge of the slope of the iliac crest, at the level of the distal border of the L5 transverse process. We move 20–25 mm cranially from the center of the planned endoscopic portal and mark the working portal. The instrument convergence point is the junction of the lateral mass and the S1 superior articular process.
References
1. Heo DH, Sharma S, Park CK. Endoscopic treatment of extraforaminal entrapment of L5 nerve root (far out syndrome) by unilateral biportal endoscopic approach: technical report and preliminary clinical results. Neurospine. 2019;16(1):130-137. doi:10.14245/ns.1938026.013.
2. Park MK, Son SK, Park WW, Choi SH, Jung DY, Kim DH. Unilateral biportal endoscopy for decompression of extraforaminal stenosis at the lumbosacral junction: surgical techniques and clinical outcomes. Neurospine. 2021;18(4):871-879. doi:10.14245/ns.2142146.073.
3. Saugel B, Fletcher N, Gan TJ, et al; POQI XI Workgroup. PeriOperative Quality Initiative (POQI) international consensus statement on perioperative arterial pressure management. Br J Anaesth. 2024;133(2):264-276. doi:10.1016/j.bja.2024.04.046.
4. American Society of Anesthesiologists Task Force on Perioperative Visual Loss, North American Neuro-Ophthalmology Society, Society for Neuroscience in Anesthesiology and Critical Care. Practice advisory for perioperative visual loss associated with spine surgery 2019. Anesthesiology. 2019;130(1):12-30. doi:10.1097/ALN.0000000000002503.
Previous section: 10.2. Equipment and Instruments