How to Understand Output from an Anion Gap Calculator
What This the Anion Gap Shows
The anion gap is a calculated value derived from common electrolytes in a routine chemistry panel. It assists clinicians identify hidden acids in the blood and assess whether a patient may have an acid-base disorder. The most common inputs are serum sodium, serum chloride, and serum bicarbonate, which are measured as part of routine serum chemistry testing.
At its core, the anion gap reflects the difference between positively charged and negatively charged particles in the bloodstream. Because routine lab tests do not measure every ion, the result gives an estimate of the “missing” or unmeasured substances, often described as an anion difference or anion deficit. This makes it a helpful diagnostic tool when reviewing a possible metabolic derangement.
The buffer system in blood works steadily to keep pH stable. When acids accumulate, the anion gap can go up, especially when there are more unmeasured anions present. Interpreting the number correctly requires more than recalling a formula. It requires understanding the surrounding clinical picture, the patient’s symptoms, and the broader laboratory correlation.
The way the Anion Gap Calculator WorksAn anion gap calculator uses a straightforward calculation formula using standard lab values. Most commonly, it subtracts chloride and bicarbonate from sodium. Several calculators also allow adjustment for albumin, since albumin is a major unmeasured anion and can strongly influence the result.
The usual calculation is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Since different laboratories may use slightly different methods and instruments, the reference range may vary. For this reason an anion gap calculator should be used as a guide rather than a stand-alone diagnosis. A similar result may be interpreted differently depending on the lab’s assay, the patient’s albumin level, and whether the clinical concern is metabolic acidosis or another acid-base condition.
When albumin is low, the calculator may also provide a corrected value. This serves to help compensate for a lower baseline anion gap caused by reduced protein concentration. In practice, the calculator supports interpretation by turning raw lab values into a more clinically meaningful estimate.
Typical Anion Gap vs. Increased Anion GapA standard anion gap often implies that bicarbonate loss is being replaced by chloride, creating a non-gap or hyperchloremic pattern. A elevated anion gap, on the other hand, implies the presence of excess acids or other unmeasured substances in the blood. This distinction is central to the evaluation of metabolic acidosis.
The exact normal range depends on the laboratory and whether the calculation includes potassium. Many clinicians think of a typical normal range as roughly within the low-to-mid teens, but the key point is to compare the value with the patient’s own lab standard rather than rely on a single universal cutoff.
A normal result does not always mean the patient is well, and a high result does not automatically mean a dangerous illness is present. The pattern should be interpreted alongside the bicarbonate level, pH if available, and the patient’s symptoms. That is where careful clinical judgment matters. In short:
Normal anion gap: often suggests bicarbonate loss or chloride gain. High anion gap: frequently points to acid accumulation from an underlying disease process.Both patterns can appear in the same patient over time, especially when treatment changes the underlying acid base balance.
How to Interpret a Low Anion GapA decreased anion gap is not as common than a high one, but it should not be ignored. The primary explanation is hypoalbuminemia, since albumin accounts heavily to the unmeasured anions that affect the result. When albumin decreases, the reported anion gap may also decrease, even if no new acid-base problem exists.
Another key cause is laboratory error, sometimes written as lab error. Because the anion gap is determined from multiple lab values, any issue with sodium, chloride, or bicarbonate measurement can create a false result. If the number is unexpectedly low, repeating the panel is often the first practical step.
Paraproteinemia is another classic cause. In some protein disorders, abnormal positively charged proteins can reduce the anion gap. This does not mean paraproteinemia is the primary cause, but it is important when the low value is ongoing and unexplained. Other contributors may include unusual medications or analytical interference, but albumin, error, and paraprotein disorders are the core categories to keep in mind.
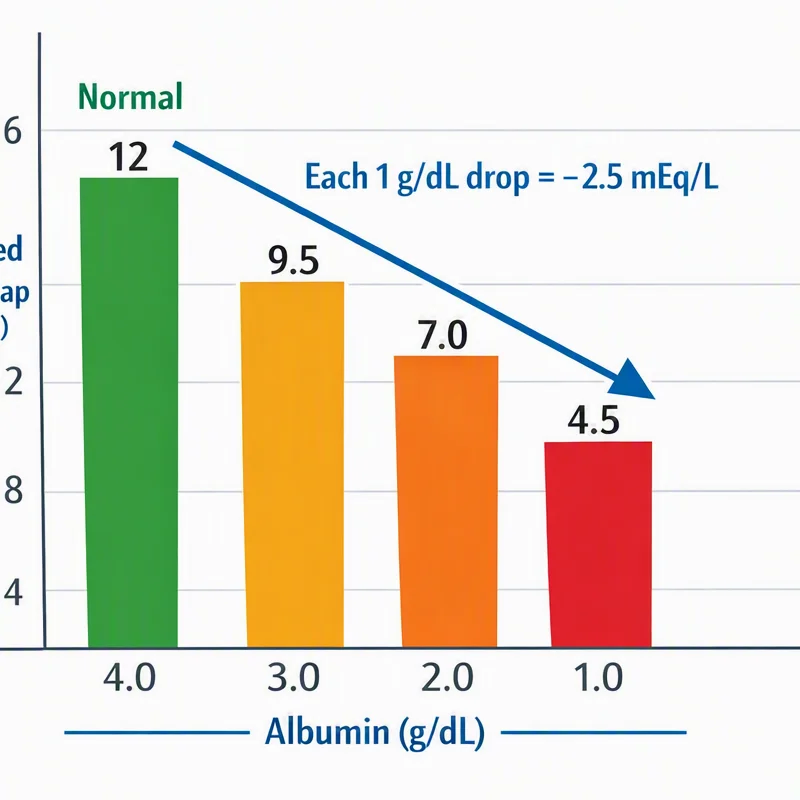
In a patient with a low anion gap, ask whether the finding is true, whether the serum albumin level is low, and whether the rest of the chemistry panel supports a true metabolic issue.
Causes of High Anion Gap Metabolic AcidosisA high anion gap is often a marker for metabolic acidosis from too much acid formation or impaired acid clearance. The major etiologies are often classified by mechanism, and the most clinically important include lactate buildup, ketone-driven acidosis, impaired kidney function, and poisons.
Elevated lactate occurs when lactate builds up, usually because of poor tissue oxygen delivery, shock, severe illness, or impaired metabolism. Ketone-related acidosis may be related to diabetes, fasting, alcohol use, or other states that increase ketone production. Kidney failure can lead to retention of organic acids that the kidneys would normally clear. Toxins and drug exposures can also generate a high anion gap pattern by adding unmeasured acids or interfering with metabolism.
Knowing the underlying physiology helps narrow the differential diagnosis. The number itself does not tell you the cause; it only signals that unmeasured acids are likely present. That is why the anion gap is best used as part of diagnostic evaluation rather than in isolation.
Key groups to consider include:
Elevated lactate from reduced blood flow, sepsis, or severe physiologic stress. Ketone-driven acidosis from diabetes, starvation, or alcohol-related states. Impaired kidney function with retention of acid load. Poisoning agents or medications that produce or mimic a metabolic acidosis.A high result should lead to a careful review of symptoms, vital signs, medication exposures, and other lab values that reflect severity and urgency.
Modified Anion Gap and Albumin AdjustmentThe corrected anion gap modifies the measured value for the influence of albumin. This is important because albumin compensation can reveal a concealed acid-base problem that a plain result might miss. Since serum albumin is a key unmeasured anion, low albumin can make the anion gap appear unchanged even when excess acids are present.
Albumin compensation improves acid-base balance interpretation by estimating what the anion gap would be if albumin were typical. Many calculators apply this automatically. When they do not, clinicians may use a correction formula based on the patient’s albumin level. The result is a more reliable refined value that more accurately reflects the actual metabolic state.
This matters particularly when the patient is critically ill, nutritionally depleted, has chronic inflammation, or otherwise has a low albumin concentration. In those settings, a normal-appearing uncorrected gap may be misleading. If the clinical picture suggests acidosis, the corrected result can uncover a hidden problem and support quicker decision-making.
Albumin correction does not replace the rest of the workup. It is a refinement that improves analysis and helps connect the chemistry panel to the broader pathophysiology.
Step-by-Step Analysis ApproachAssessing an anion gap result is best handled as a step-by-step process rather than a brief review at the number. The goal is to link the calculator output with the patient’s actual condition and determine whether the result fits an acid-base disorder.
A clinical approach includes these steps:
Check the serum sodium, serum chloride, and serum bicarbonate values used by the calculator. Assess the result with the lab’s reference range. Evaluate the bicarbonate level for evidence of metabolic acidosis. Assess the albumin value and consider albumin correction if needed. Use the arterial blood gas when available to confirm pH and respiratory compensation. Combine the result with clinical assessment, including symptoms, medications, and medical history.An arterial blood gas can help determine whether the chemistry panel reflects true acidemia, compensation, or a mixed disorder. The blood gas also helps differentiate isolated chemistry abnormalities from a clinically important acid-base disturbance. In many cases, the best interpretation comes from using together the calculator with the blood gas, exam findings, and serial lab values.
Remember that the anion gap is a screening test, not a final diagnosis. It suggests a problem, but the surrounding data determine what that problem is.
When to Repeat Labs or Seek Urgent EvaluationNot every abnormal result requires instant treatment, but some situations call for retesting or prompt intervention. If the result seems not aligned with the patient’s condition, if there is concern for dangerous values, or if the calculation may have been affected by a pre-analytical issue, rechecking the chemistry panel is appropriate.
Look closely at the overall clinical picture. Concerning symptoms may include altered mental status, increased breathing rate, severe weakness, ongoing vomiting, chest discomfort, or signs of shock. These findings can indicate significant metabolic disturbance and should lead to quick assessment. When symptoms are severe, or when the patient appears unstable, immediate emergency assessment is warranted.
Repeat testing is also helpful when a low anion gap may reflect lab error, or when a corrected calculation is needed because albumin was not included. If the abnormality persists, the next step is usually a more detailed diagnostic evaluation rather than simple observation.
In short, repeat the labs when the number is unexpected, the sample may be unreliable, or the clinical picture does not match the result. Get urgent care when symptoms or associated findings suggest a potentially dangerous acid-base problem.
Common Questions What is considered a normal anion gap?The normal range depends on the laboratory method and the way the calculation is performed. Many labs use a reference range in the low-to-mid teens, but the most accurate answer is the one listed by the testing facility. Always interpret the result in context with serum albumin, bicarbonate, and the rest of the chemistry panel.
How is the anion gap calculated?The standard formula for calculation is serum sodium minus the sum of serum chloride and serum bicarbonate. An Anion Gap Calculator performs this automatically and may also provide a corrected value when albumin is low.
What causes reduced albumin affect the anion gap?Albumin is a important unmeasured anion. When albumin falls, the measured anion gap can also drop, which may obscure an underlying acid-base problem. That is why albumin correction is important when reading results in patients with hypoalbuminemia.
What leads to a high anion gap?The typical causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, renal failure, and certain toxins. anion gap in chronic kidney disease The appropriate next step is to correlate the chemistry findings with the symptoms, arterial blood gas, and the rest of the laboratory evaluation.
When is it time to an abnormal anion gap be rechecked?Recheck the result when it does not fit the clinical picture, when lab error is possible, or when the patient has worrisome symptoms. Repeat testing is also appropriate if the result is near a decision threshold or if albumin was not measured and a corrected value is needed. If the patient is clinically unstable or has critical findings, seek urgent causes of normal anion gap acidosis assessment without delay.