@Endocrine_ATM
@DR_ATMCorrect Answer:
E) TSH level and thyroid ultrasound
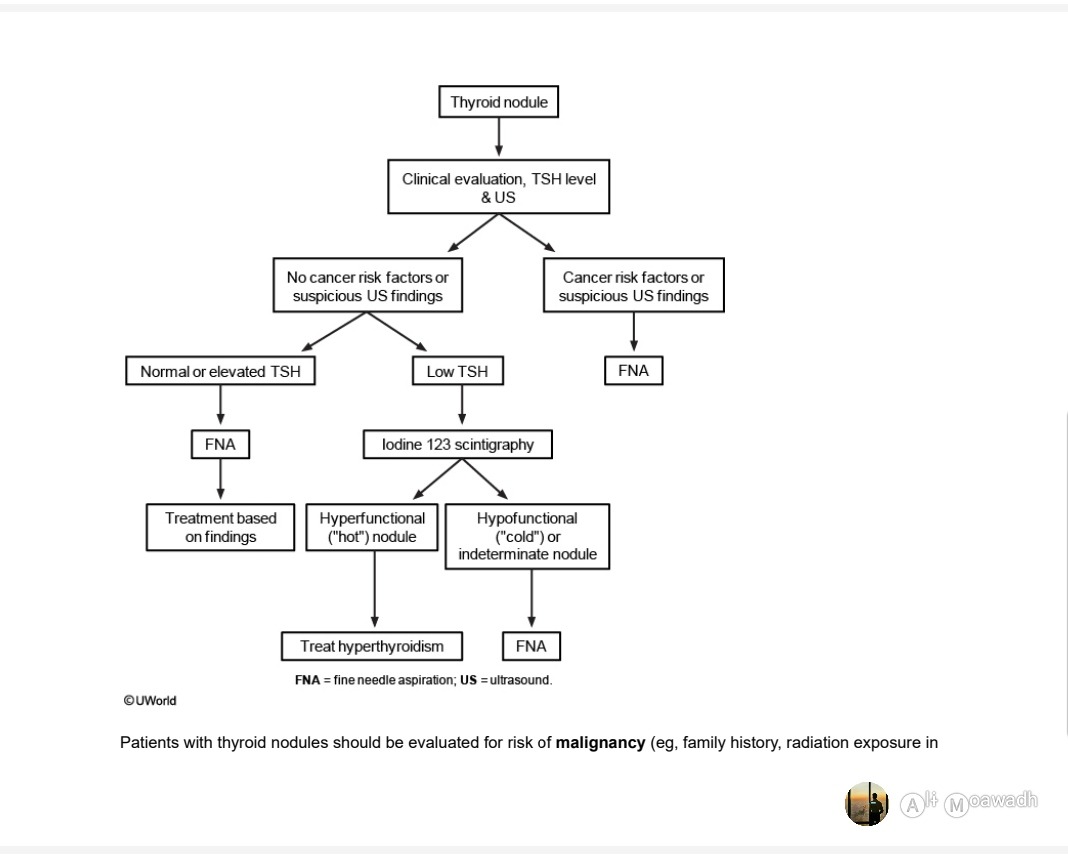
childhood, cervical lymphadenopathy), compressive symptoms (eg, hoarseness, difficulty swallowing), and
functional status (eg, euthyroid, hyperthyroid, hypothyroid). Definitive diagnosis of thyroid cancer can be made
with fine-needle aspiration (FNA), but the goal of the clinical assessment is to determine which patients will require
this invasive procedure.
Initial testing to evaluate a thyroid nodule should include a serum TSH level and thyroid ultrasound. Patients with
suspicious ultrasound findings (eg, large size, hypoechoic, microcalcifications, internal vascularity) or cancer risk
factors should undergo FNA (Choice B). In addition, patients with normal or elevated TSH have a higher risk of
malignancy and should be considered for FNA depending on ultrasound findings. Low TSH levels suggest a
hyperfunctioning nodule, which has a lower risk of malignancy and should be evaluated with thyroid scintigraphy
(Choice C). A "hot" nodule (increased isotope uptake in the nodule with decreased surrounding uptake) is rarely
malignant and may be treated as benign hyperthyroidism.
(Choice A) A CT scan of the neck can diagnose retrosternal goiter in patients with compressive symptoms (eg,
hoarseness, dysphagia), but it is otherwise less sensitive than thyroid ultrasound for evaluation of nodules.
(Choice D) Serum anti-thyroid peroxidase antibody titers are elevated in patients with chronic autoimmune
(Hashimoto) thyroiditis, which usually presents with hypothyroidism and a normal-sized or diffusely enlarged thyroid.
Educational objective:
Thyroid nodules should be evaluated with TSH and thyroid ultrasound. Patients with suspicious findings on
ultrasound should undergo fine-needle aspiration with cytology of the nodule. Patients with low TSH should have a
radionuclide thyroid scan