Anion Gap Calculator for Measuring Electrolyte Disturbance
What the anion gap means and why it matters
The anion gap is a derived value that assists clinicians in interpreting serum electrolytes and refine the differential diagnosis of metabolic acidosis. It represents the difference between measured positively charged and negatively charged particles in blood, offering a helpful snapshot of acid-base balance and overall electrolyte imbalance.
Although the anion gap is not a direct measurement, it has important clinical significance because it can suggest hidden acids in the bloodstream, missed electrolyte shifts, or broader systemic causes of illness. In practice, it is often used as part of a broader evaluation that includes the electrolyte panel, serum chemistry, and additional tests when an abnormal result appears.
An elevated or low anion gap can support the diagnosis of an acid-base disorder, especially when symptoms, history, and laboratory values suggest a metabolic problem. A well-designed anion gap calculator can make easier the calculation and help clinicians focus on interpretation rather than arithmetic.
How to operate an anion gap calculatorAn anion gap calculator takes three core laboratory values: serum sodium, serum chloride, and serum bicarbonate. These results are usually listed on an electrolyte panel and can be entered into a calculator for fast evaluation.
The steps are simple. Input the sodium value, then the chloride and bicarbonate values from the same blood sample. The calculator performs the calculation and returns the anion gap, which can then be compared with the expected reference range. That comparison is the first step in interpretation.
Because laboratory methods can differ slightly, the exact output may vary by institution. That is why the calculator should be used as a tool for screening and patient assessment, not as a standalone diagnosis. If the result is unexpected, review the source numbers for transcription errors, then consider whether other factors such as low albumin or mixed disorders may be influencing the result.
Step 1: Confirm the correct serum sodium, serum chloride, and serum bicarbonate values. Step 2: Use the anion gap calculator. Step 3: Review the result with the local reference range. Step 4: Use the output for evaluation of possible metabolic acidosis or other acid-base patterns. Step 5: If needed, obtain follow-up testing such as an arterial blood gas or lactate level. The anion gap formula and expected rangeThe standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
This straightforward formula helps estimate unmeasured ions in the blood. In most cases, the result is interpreted with NAGMA differential diagnosis the normal anion gap range, which can differ depending on the laboratory assay and whether potassium is included. Many clinicians prefer the sodium-based formula above because it is widely reported and easy to apply.
Albumin matters because it is one of the main unmeasured anions in plasma. If albumin is low, the measured anion gap may appear falsely normal or only mildly elevated even when clinically important acids are present. That is why understanding the patient's full chemistry profile is essential for accurate interpretation.
As a practical matter, the calculator should be viewed as a decision-support tool that helps with clinical significance, not a replacement for reasoning about laboratory values. A result inside the usual range does not always exclude disease, and a result outside the range does not automatically confirm a single cause.
Elevated anion gap versus typical anion gap disordersThe result, whether high or normal, can separate two major groups of electrolyte disturbance. High anion gap metabolic acidosis develops when unmeasured acids accumulate, while normal anion gap metabolic acidosis usually reflects bicarbonate loss or chloride gain with retention of the overall gap.
This distinction is central to the differential diagnosis of metabolic acidosis. In cases of high anion gap acidosis, the blood contains additional acid anions that are not directly measured in the basic electrolyte panel. In cases of normal anion gap acidosis, the problem is often more about replacement of bicarbonate with chloride, leading to hyperchloremia rather than a widened gap.
Both types represent an acid-base disorder, but they point toward different systemic causes and separate next steps in evaluation. The calculator can therefore be used as an early starting point in clinical reasoning.
High anion gap metabolic acidosis: indicates unmeasured acids are present. Normal anion gap metabolic acidosis: implies bicarbonate loss or chloride retention. Mixed disorders: can mask the expected pattern and require broader interpretation. Typical causes of elevated anion gapA number of key conditions can elevate the anion gap. Of the most common are lactic acidosis, ketoacidosis, and kidney failure. These disorders increase unmeasured acids in the bloodstream and are often associated with clinically significant acid-base acidosis.
Lactate buildup happens when lactate increases due to poor tissue oxygen delivery, shock states, severe infection, or other causes of impaired metabolism. It is a key consideration when a patient has an elevated anion gap and appears acutely ill.
Ketone-related acidosis can occur in diabetes, prolonged fasting, alcoholism, or other catabolic states. Ketone bodies are unmeasured anions that increase the gap and often produce a distinct acid-base disturbance on the electrolyte panel.
Kidney failure can also cause accumulation of organic acids and impaired acid excretion. As kidney function declines, the body loses the ability to maintain normal acid-base balance, and the anion gap may increase.
Other possible causes can include severe intoxications, but the main clinical approach is to ask whether the elevated gap reflects excess acid production, impaired acid clearance, or both. That is where the calculator becomes especially helpful for fast screening and structured interpretation.
Frequent causes of normal anion gap acidosisNormal anion gap metabolic acidosis frequently results from bicarbonate loss or inability to reclaim bicarbonate in the kidney. A common cause is diarrhea, where bicarbonate is depleted via the gastrointestinal tract. This may cause a low bicarbonate level with a relatively unchanged anion gap.
Renal tubular acidosis is also an important cause. In this condition, the kidneys cannot properly acidify the urine or reabsorb bicarbonate, leading to a persistent acid-base disorder. The anion gap may still be normal even when the patient has clear metabolic acidosis.
Hyperchloremia often accompanies these disorders because chloride rises to maintain electrical neutrality as bicarbonate falls. That is why normal gap acidosis is sometimes called hyperchloremic metabolic acidosis.
From a clinical standpoint, this pattern matters because the causes and the workup differ from those of high gap acidosis. The result from the calculator should prompt careful assessment of volume status, medication exposure, kidney function, and gastrointestinal losses.
How serum albumin changes the anion gapAlbumin is a major unmeasured anion, so decreased levels can greatly affect the observed anion gap. In hypoalbuminemia, the anion gap may look lower than expected even when the patient has a substantial acid-base problem. This can lead to missed recognition of high gap states if the result is interpreted without adjustment.
That is why albumin correction is often recommended when albumin is abnormal. The goal is to estimate a more precise corrected anion gap that more closely reflects the true acid burden. The corrected value can turn a borderline result into a more clinically relevant range.
Using an albumin-corrected anion gap is especially helpful when the patient has a suspicious presentation but only a mildly elevated or even normal measured gap. In that setting, the corrected value may uncover a hidden high anion gap process.
Because hypoalbuminemia is common in acute and chronic illness, albumin adjustment improves interpretation and enhances the overall evaluation. It helps clinicians not overlook important disease when the measured chemistry picture appears misleadingly normal.
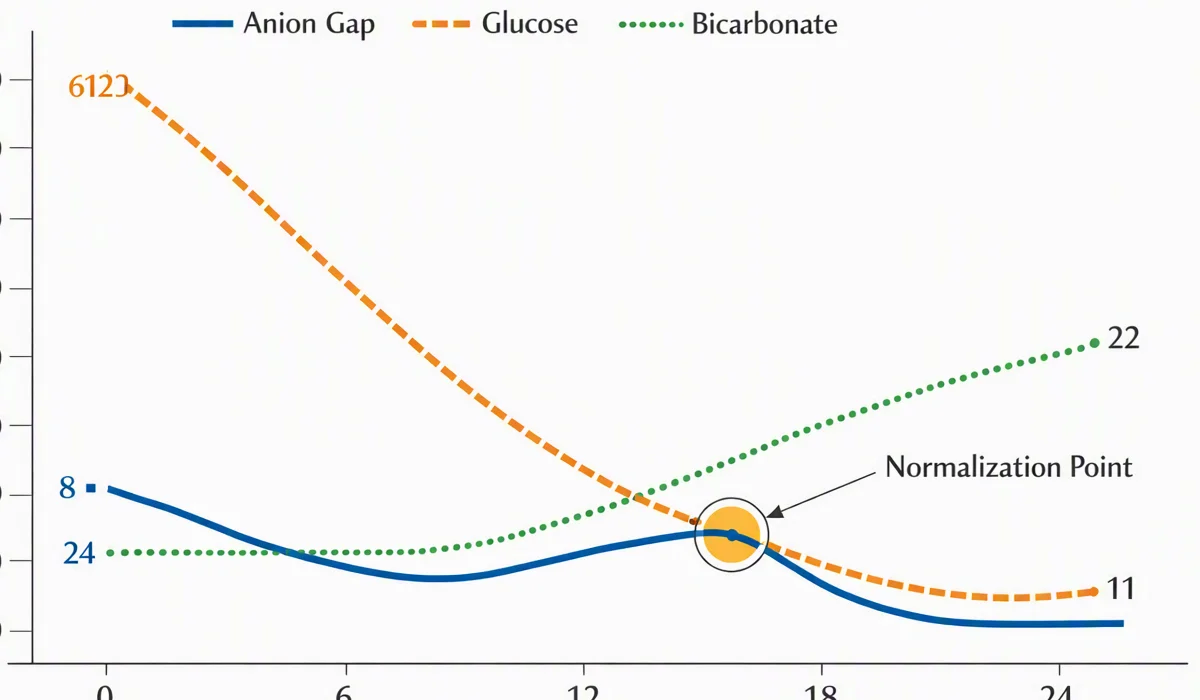
Clinical interpretation and next stepsThe anion gap is most valuable when used as part of a broader approach to acid-base disorder. If the gap is elevated, the next steps often include reviewing an arterial blood gas, measuring lactate, reviewing ketones, and assessing kidney function. If the gap is normal but bicarbonate is low, clinicians should think about bicarbonate loss, kidney tubular problems, or chloride gain.
In many cases, the best interpretation also includes the osmolar gap. A raised osmolar gap together with an elevated anion gap can suggest ingestion of toxic alcohols, especially when the history is unclear. This combination is important because it can indicate a critical toxicologic emergency.
When the clinical picture is unclear, the anion gap calculator serves as a starting point for diagnosis and follow-up testing. It helps prioritize whether the case is more consistent with lactic acidosis, ketoacidosis, renal failure, diarrhea, renal tubular acidosis, or another cause of electrolyte imbalance.
Useful next steps may include:
Repeat the results of the electrolyte panel if results do not match the clinical picture. Obtain an arterial blood gas to confirm the acid-base status. Check albumin for albumin-corrected anion gap interpretation. Measure lactate or ketones when metabolic acidosis is suspected. Consider the osmolar gap if exposure to toxic alcohols is possible.Overall, the calculator is most effective when used as part of thoughtful patient assessment rather than as a stand-alone number. The goal is not only to identify whether the result is abnormal, but also to understand what pattern of illness it suggests and what should happen next.
Frequently asked questions What is an anion gap calculator used for?An anion gap calculator is used to quickly perform the calculation from serum sodium, chloride, and bicarbonate values. It helps with screening and interpretation of an electrolyte panel, especially when evaluating metabolic acidosis and other forms of electrolyte disturbance.
What is the meaning of a elevated anion gap mean?A raised anion gap usually points to an accumulation of unmeasured acids in the blood. Frequent causes include lactic acidosis, ketoacidosis, and renal failure. It is a key clue in the diagnosis of high anion gap metabolic acidosis.
What is the normal anion gap range?The normal anion gap range depends on the laboratory method and if potassium is included in the formula. Because reference ranges vary, the result should always be checked against the local laboratory's reference range for accurate interpretation.
What effect does low albumin affect the anion gap?Low albumin reduces the measured anion gap because albumin is a major unmeasured anion. In hypoalbuminemia, the result may appear artifactually normal or only mildly elevated. An albumin correction can produce a more accurate corrected anion gap and enhance clinical interpretation.
When should an elevated anion gap be investigated further?An elevated anion gap should be investigated further whenever it is not anticipated, persistent, or accompanied by signs of illness such as suspected metabolic acidosis, altered mental status, kidney dysfunction, or shock. Further workup may include an arterial blood gas, lactate, ketones, albumin, and assessment of the osmolar gap for possible toxic alcohols.