Anion Gap Calculator Using Sodium, Chloride, and CO2
An Anion Gap Calculator is a practical method to estimate the anion gap from everyday lab data. By using sodium, chloride, and carbon dioxide values from a standard electrolyte panel, it assists clinicians and students quickly check acid-base balance and look for patterns that may point to an underlying metabolic acidosis or other acid-base disorder. Because the calculation comes directly from common serum chemistry results, it is one of the most useful tools in basic laboratory interpretation.
The value is not a diagnosis by itself. Rather than that, it is a initial and interpretation aid that reflects the relationship between measured serum electrolytes and the unmeasured ions in the blood. In practice, this makes the anion gap a useful diagnostic tool for evaluating a result in the context of the patient’s symptoms, history, and other laboratory values.
Explaining the Anion Gap MeasuresThe anion gap reflects the balance between the major measured positive ions and negative ions in the blood. It is based on the principle of electroneutrality, which means the body keeps positive and minus charges in equilibrium. Since regular chemistry tests do not measure every ion, the gap calculates the amount of unmeasured anions present in the sample.
In daily clinical use, the anion gap is a quick way to assess whether an abnormality in the blood chemistry may suggest an acid-base disorder. A shift in the gap can point to accumulation of acids, loss of bicarbonate, or changes in other charged particles. That is why it is often discussed alongside serum electrolytes and other markers of acid-base balance.
For many patients, the anion gap is most helpful when interpreting a basic metabolic profile or an electrolyte panel. The calculation can provide a quick sense of whether the laboratory pattern is within range or whether further evaluation is needed. It is especially important in evaluating a possible metabolic disorder that changes the equilibrium of acids and bases.
How to Work Out Anion Gap from Sodium, Cl, and Carbon DioxideThe standard Anion Gap Calculator process uses three values: sodium, chloride, and carbon dioxide. In many lab panels, the reported carbon dioxide value is used as a stand-in for bicarbonate. Because bicarbonate is the main measured base in this calculation, the carbon dioxide result is critical to the final number.
The simple calculation is:
Anion gap = sodium − (chloride + bicarbonate)
When using a typical lab report, the formula is often written as:
Anion gap = sodium − (chloride + CO2)
That means the calculator deducts the sum of chloride and carbon dioxide from sodium. For example, if sodium is 140, chloride is 104, and CO2 is 24, the calculation is 140 − (104 + 24) = 12. This is a direct calculation that can be performed by hand or through an web-based calculator.
The advantage of this method is its efficiency. Because sodium, chloride, and CO2 are part of a common electrolyte panel, the anion gap can be obtained without additional testing. This makes it useful as a quick evaluation step during interpretation of routine laboratory values.
Formula, Measurement Units, and Normal RangeThe anion gap equation is commonly expressed in mEq/L. This unit reflects the charge concentration of the measured ions in serum electrolytes. Most calculators report the answer in the same units because the result is derived from concentrations of charged particles rather than mass or volume.
The exact reference range can vary depending on the laboratory method used. Different instruments, instruments, and reporting conventions can shift the expected value slightly. Most labs consider a typical anion gap to fall within a range that centers around the low teens, but the important point is to use the local normal range that matches the testing method.
This is why the same numerical value may be interpreted differently depending on the clinical setting. An anion gap that appears normal on one report might be borderline or mildly abnormal on another if the lab uses a different calibration or calculation approach. A careful review of the report is part of sound medical judgment.
In most cases, the formula is best used as a practical guide rather than an absolute threshold. The calculator provides a numerical value, but the meaning of that value depends on the patient’s medical context, the rest of the chemistry panel, and whether the reported carbon dioxide reflects true bicarbonate status.
How to Read a Low or High Anion GapA increased anion gap often indicates the existence of extra acids in the blood. This is a typical clue in metabolic acid buildup, where acid accumulation or reduced acid clearance shifts the balance between measured cations and anions. In practical terms, a high value can signal a more serious underlying issue that needs additional workup.
A standard anion gap does not always rule out an acid-base problem. Some forms of acidosis can occur with a gap that remains within the expected reference range. For that reason, the anion gap should be interpreted in combination with pH, bicarbonate, chloride, and other findings rather than used alone.
A low anion gap is less common, but it can be clinically meaningful. One major reason is a low level of serum albumin, because albumin contributes negatively charged proteins that affect the balance of measured ions. When albumin is reduced, the observed gap may appear lower even if other processes are present.
Interpreting a gap also depends on whether the patient has a mixed disorder. For example, a person may have metabolic acidosis with a gap that seems only mildly elevated if another process is lowering the bicarbonate or if the electrolyte pattern is altered by treatment or fluid shifts. This is where careful assessment matters more than the number alone.
Typical Causes of Abnormal ResultsSeveral conditions can lead to a high anion gap. A classic cause is lactic acidosis, where lactate accumulates due to poor oxygen delivery, shock, severe illness, or other metabolic stress. Another common cause is ketoacidosis, which occurs when ketone bodies rise in diabetes, starvation, or other states of impaired carbohydrate use.
Renal failure can also increase the gap because the kidneys are not as able to clear acid load and other unmeasured anions. As kidney function worsens, acids accumulate and the measured electrolyte pattern may alter. In this situation, the anion gap becomes one part of a broader evaluation of metabolic waste retention and acid handling.
Poison ingestion is another important category. Certain ingestions can create a high gap by introducing acids or toxic metabolites into the blood. In the right clinical scenario, the anion gap may provide an early clue that prompts urgent investigation. The calculation itself does not identify the toxin, but it can support timely recognition of an abnormal pattern.
On the other hand, a low anion gap may be associated with low albumin, laboratory artifact, or uncommon changes in serum proteins and ions. While less frequent than high values, a low result should not be ignored if it is unexpected or inconsistent with the patient’s condition. It may require repeat testing or broader evaluation of the chemistry panel.
Correcting the Anion Gap for AlbuminAlbumin adjustment is an essential step when reading the anion gap, especially in patients with hypoalbuminemia. Since albumin is a primary unmeasured anion, a low albumin level can make the anion gap look falsely normal or low. In these cases, the unadjusted result may downplay the true acid burden.
An adjusted anion gap takes into account this effect by changing the calculated value based on the albumin concentration. The exact adjustment method can differ, but the purpose is the same: to improve accuracy in interpretation when albumin is below normal. This is particularly helpful when evaluating suspected metabolic acidosis in hospitalized or chronically ill patients.
The need for compensation becomes more obvious when the laboratory pattern seems discordant with the clinical picture. For example, a patient may have signs of acid-base disturbance, but the uncorrected gap is not elevated. In that setting, checking albumin and applying correction can help reveal an abnormality that would otherwise be missed.
Albumin correction does not substitute for the original calculation. Instead, it adds another layer of information to the same formula-based assessment. The adjusted number should still be interpreted with patient context, especially if there are mixed disorders, fluid changes, or multiple abnormal laboratory values.
Limits of an Anion Gap CalculatorAlthough an Anion Gap Calculator is valuable, it has a number of restrictions. One major is lab variation. Different analyzers and methods can yield mildly different sodium, chloride, or carbon dioxide values, which changes the final result. So the same patient could get a somewhat different number depending on where the sample is processed.
Measurement error can also impact the outcome. Minor inaccuracies in any one of the input values can alter the final calculation. Since the anion gap is derived from a subtraction-based formula, minor differences in chloride or CO2 may have a notable effect on the result, especially if the gap is near the edge of the reference range.
One more limitation is that the calculator reflects only part of the acid-base picture. It does not directly measure blood pH, lactate, ketones, renal function, or toxic substances. For that reason, the number should be treated as https://telegra.ph/How-to-Interpret-an-Anion-Gap-Calculator-When-Albumin-Is-Low-08-29 one part of overall blood test interpretation, not as a stand-alone answer.
The best use of the tool is as a fast screening aid. It can flag a possible abnormality and guide further evaluation, but it cannot determine the cause on its own. The same numerical value can have varying meaning depending on the patient’s symptoms, medications, hydration status, and underlying illness. Good medical decision-making always combines the calculation with the rest of the clinical picture.
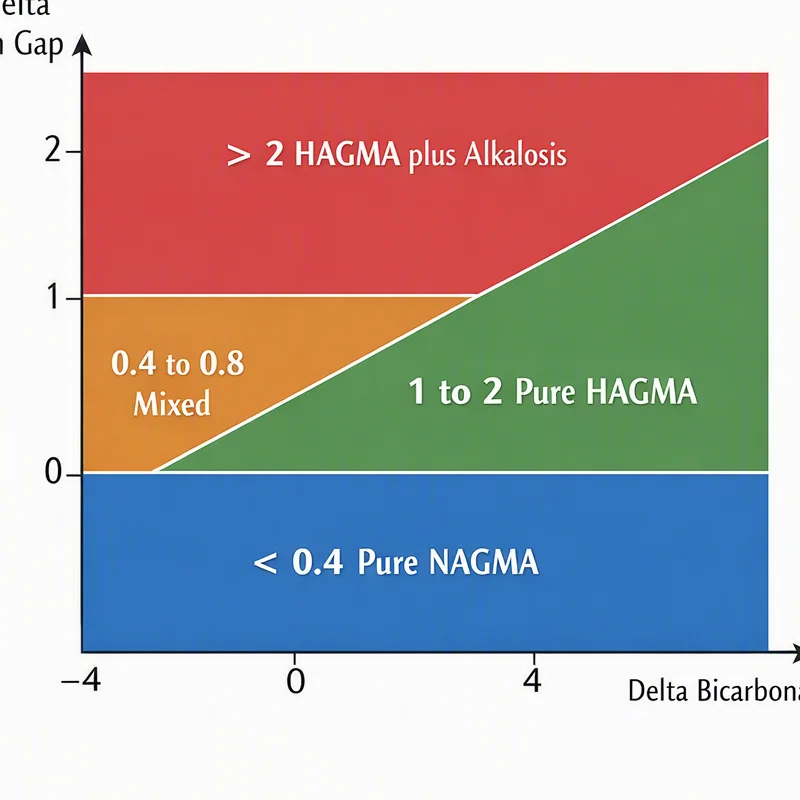
Apply the formula sodium − (chloride + CO2). In this calculator workflow, carbon dioxide is used as a useful substitute for bicarbonate. The result is the anion gap, usually reported in mEq/L.
What is the normal range for an anion gap?The normal anion gap depends on the laboratory and method used. This is why you NAGMA causes should always compare the result to the report’s reference range. Different serum chemistry analyzers can generate slightly different expected values.
What does a elevated anion gap mean?A raised anion gap often indicates metabolic acidosis due to extra unmeasured acids in the blood. Frequent causes include lactic acidosis, ketoacidosis, renal failure, and some types of toxin ingestion.
Why might the anion gap be low?A decreased anion gap is commonly linked to low albumin, especially in hypoalbuminemia. It can also stem from lab-related issues or less common changes in serum proteins and electrolytes. If this finding is unexpected, repeat testing and broader evaluation may be appropriate.
Should albumin be considered when interpreting the anion gap?Yes. Albumin correction is important because albumin is a major unmeasured anion. When albumin is low, the measured gap may underestimate the true abnormality. An adjusted anion gap can improve interpretation and make the result more useful for assessing acid-base balance.