Anion Gap Calculator: A Reference for Future Clinicians
How to define the Anion Gap?
The anion gap is a simple way to approximate whether there are unmeasured ions in the blood. It is based on common values on the electrolyte panel and helps one interpret an acid-base disorder, especially metabolic acidosis. For students in medicine, the anion gap is one of the fastest ways to move from raw serum electrolytes to a meaningful clinical interpretation.
In practice, the anion gap reflects the balance between measured sodium, chloride, and bicarbonate. Since the body must maintain electrical neutrality, a change in one of these values often indicates an accompanying electrolyte imbalance or a hidden metabolic derangement. That is why the anion gap is so valuable diagnostic tool in patient evaluation.
Students often think of it as a memorized number, but it is better understood as a clue. A high anion gap suggests that acid is accumulating or that unmeasured anions are present. A normal anion gap implies a different set of causes, often involving bicarbonate loss with compensatory chloride retention. Understanding this distinction is crucial for building a strong differential diagnosis.

An anion gap calculator is a convenient way to carry out the gap calculation quickly during study time, clinical rounds, or exam review. Most calculators ask for serum sodium, serum chloride, and serum bicarbonate. After inputting those laboratory values, the calculator provides the anion gap, at times with a corrected result if albumin is low.
The process is straightforward:
Add the patient’s sodium value. Enter the chloride value. Enter the bicarbonate value. Inspect the calculated anion gap and contrast it to the reference range.Clinically, the calculator helps you focus on the bigger question: does the acid-base picture fit metabolic acidosis, and if so, what is the underlying cause? A calculator is valuable because it removes arithmetic errors and speeds up recognition of patterns in the electrolyte panel.
For exam settings, always pair the calculator output with the full context of the patient’s acid-base status. A single number does not make the diagnosis. Instead, it leads the next step in the patient evaluation, whether that means checking lactate, ketones, kidney function, or medication exposure.
Anion Gap Formula and Reference RangeThe standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
This formula uses the main measured cations and anions on a standard panel. As sodium is generally the dominant cation, the result estimates the difference between measured positive and negative charges. The precise formula may vary slightly depending on the lab or calculator, but this version is the best known for medical students.

The normal anion gap depends on the lab method and whether potassium is included. Many teaching resources use a reference range about 8 to 12 mEq/L without potassium, but you should always rely on the specific reference range when available. The important point is not memorizing one universal number, but recognizing whether the value is elevated relative to the expected range.
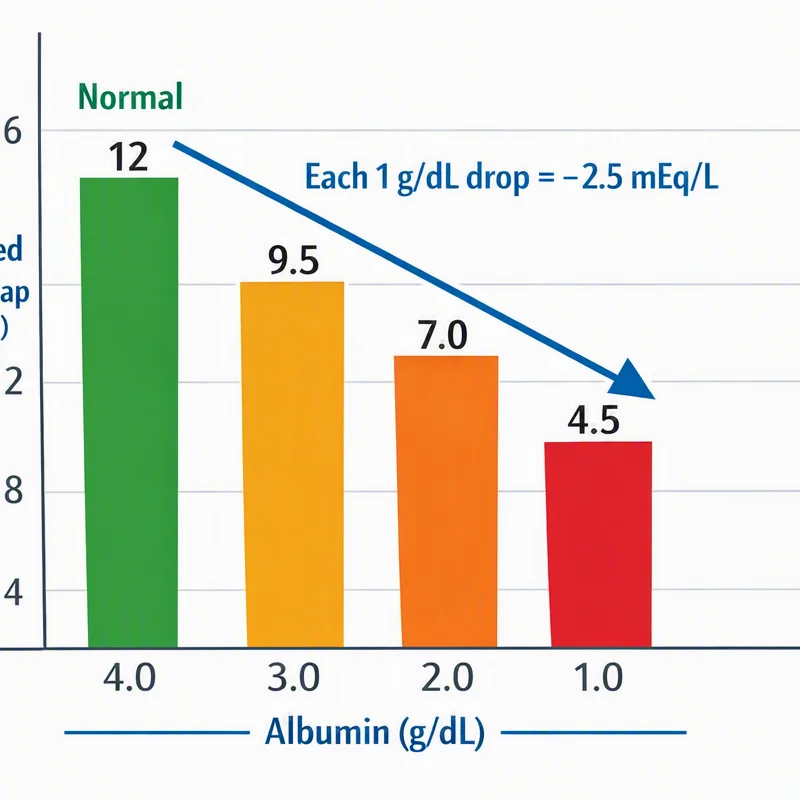
Albumin matters because it is a major unmeasured anion. When albumin is normal, the gap better reflects the expected balance of measured and unmeasured ions. When albumin is low, the gap may appear falsely reassuring. That is why albumin correction is an important part of interpretation, especially when you suspect metabolic acidosis but the raw number looks normal.
A helpful exam habit is to think in layers: first calculate the gap, then decide whether it is normal or elevated, and then use the pattern to narrow the differential diagnosis. This structured approach improves confidence and reduces missed diagnoses.
Adjusted Anion Gap for Low AlbuminHypoalbuminemia decreases the reported anion gap because albumin provides negative charge to the https://anion-gap-estimator947.timeforchangecounselling.com/anion-gap-calculator-used-for-metabolic-acidosis-evaluation plasma. If albumin is reduced, the patient may still have a clinically significant acidosis even though the uncorrected gap appears normal. That is why the corrected anion gap is so important in everyday medicine.
The idea behind the correction is straightforward: if albumin is low, the gap should be adjusted upward to account for the missing unmeasured anions. This albumin correction helps prevent missing a hidden high anion gap process. For students, this is a common test pitfall and a regular source of error during clinical interpretation.
A practical way to think about it is this: the more reduced the albumin, the more likely the uncorrected value will minimize acid burden. In critically ill patients, patients with malnutrition, liver disease, or inflammation, checking for hypoalbuminemia should be part of the normal evaluation. If the calculator includes corrected output, use it. If not, calculate it manually or read carefully.
Remember that the corrected result does not replace the rest of the evaluation. It simply improves sensitivity for detecting hidden acid-base status changes. In other words, the corrected number helps you think more clearly about the patient’s metabolic state rather than relying at the first result.
High Anion Gap Metabolic Acidosis: Frequent CausesA high anion gap usually means there are excess acids in the blood or an build-up of unmeasured anions. This pattern is key to diagnosing high anion gap acidosis and is one of the most commonly examined topics in acid-base review. The leading causes medical students should know include lactic acidosis, ketoacidosis, and uremia.
Lactic acidosis develops when lactate builds up due to tissue hypoperfusion, hypoxia, sepsis, seizures, or severe metabolic stress. It is a classic cause of elevated gap and should be considered whenever the patient appears ill. In practice, lactate is often one of the earliest follow-up labs when a gap is high.
Ketoacidosis is another major cause. This includes diabetic ketoacidosis, alcoholic ketoacidosis, and starvation ketosis. The common theme is ketone body accumulation, which contributes unmeasured anions and raises the gap. Look for hyperglycemia, dehydration, abdominal pain, or a compatible history, depending on the scenario.
Uremia from advanced kidney dysfunction can also produce a high anion gap because retained acids are not adequately excreted. In this setting, kidney function testing and the overall clinical picture are essential. A student should always connect the laboratory result to the patient’s symptoms, renal history, and broader metabolic picture.
Other causes may appear on exams, but these three are the essential starting points. A useful strategy is to ask: is the body producing extra acid, failing to clear acid, or both? That question quickly organizes the differential diagnosis and prevents random memorization.
Normal Anion Gap Metabolic Acidosis: Frequent CausesA normal-gap anion gap metabolic acidosis is also called chloride-responsive acidosis. In this pattern, bicarbonate is depleted, and chloride rises to maintain electrical neutrality. The result is a normal computed gap even though the patient is clearly acidotic. This is a classic example of why looking only at the gap can be misleading.
Gastrointestinal fluid loss is one of the most common causes. The gastrointestinal tract loses bicarbonate-rich fluid, and the serum chloride climbs in compensation. If a patient has significant GI losses and a low bicarbonate, a normal gap should make this diagnosis move higher on the list.
RTA is another important cause. Here, the kidneys do not manage to acidify the urine or conserve bicarbonate properly. It is a key consideration when the patient has persistent metabolic acidosis without obvious GI losses, especially when kidney function seems otherwise preserved.
These patterns matter because the treatment depends on the mechanism. If the cause is hyperchloremic metabolic acidosis, the approach may focus on fluid loss, renal evaluation, or replacing bicarbonate in selected cases. The gap itself does not determine the treatment; it guides the workup and sharpens the diagnostic differential.
For students, the most important takeaway is that a normal gap does not mean “no problem.” It often means the acid-base disorder is caused by bicarbonate loss rather than unmeasured acid accumulation. That distinction is essential for accurate interpretation.
Clinical Assessment Guidelines for Students of MedicineStrong clinical interpretation begins with the complete electrolyte panel, not only the number from the tool. The first step is to confirm there is an acid-base disorder by looking at pH and bicarbonate. Next, work out the gap. Then, judge whether the pattern matches a high anion gap or a normal anion gap state. Finally, connect the result to the most likely cause.
One helpful mental framework is to think about the leading underlying cause before chasing rare diagnoses. If the patient is unstable, think about lactic acidosis. If there is diabetes, poor intake, or alcohol use, suspect ketoacidosis. If kidney function is poor, think about uremia. If there is diarrhea or chronic GI loss, consider diarrhea and renal tubular acidosis.
Another common exam pitfall is ignoring hypoalbuminemia. If albumin is low, the raw gap may underestimate the degree of acidosis. That is why corrected values are part of good practice and why many acid-base disorders questions include albumin for a reason.
Below are a few quick habits that help in patient evaluation:
Make sure to review the entire electrolyte panel, not just the anion gap. Verify whether the result matches the patient’s acid-base status. Apply albumin correction when albumin is abnormal. Apply the gap to sharpen the differential diagnosis, not to finish it. Consider whether the pattern suggests a metabolic derangement or compensation for another disorder.For exams, practice turning a raw number into a story. Example: “This patient has metabolic acidosis with an elevated gap, which raises concern for lactic acidosis, ketoacidosis, or uremia.” This kind of reasoning is exactly what faculty expect when they assess understanding of the anion gap calculator and its clinical use.
FAQ About the Anion Gap Calculator What is an anion gap calculator used for?An anion gap calculator is used to rapidly determine the anion gap from sodium, chloride, and bicarbonate. It helps determine whether a patient’s metabolic acidosis is more consistent with a high anion gap process or a normal anion gap condition. For medical students, it is a useful diagnostic tool for structuring the differential diagnosis.
What is the normal anion gap range?The normal anion gap differs by lab and method, so the exact reference range may be different. Many educational settings use a range around 8 to 12 mEq/L without potassium, but you should always read the result in the context of the local laboratory values. The key is whether the result is abnormal for that specific setting and whether the patient’s acid-base status fits the pattern.
Why do you correct the anion gap for albumin?You modify the anion gap for albumin because hypoalbuminemia can make the uncorrected value look lower than it truly is. Since albumin is a major unmeasured anion, low levels can mask a clinically important high anion gap disorder. The corrected anion gap improves interpretation and helps prevent overlooking a significant metabolic problem.
What causes a high anion gap metabolic acidosis?The most common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and uremia. These conditions increase unmeasured acids or impair acid clearance. When the gap is elevated, the next step is to find the underlying cause based on the clinical picture, history, and other laboratory findings.
What causes a normal anion-gap metabolic acidosis?A typical anion gap metabolic acidosis is frequently due to diarrhea, renal tubular acidosis, and other forms of hyperchloremic acidosis. In these cases, bicarbonate is reduced or reduced and chloride rises to maintain balance. This pattern is important because it indicates the absence of excess unmeasured acids and toward bicarbonate loss or renal handling problems.